Related Experiment Video
Updated: Jun 16, 2026


Modeling Brain Metastasis by Internal Carotid Artery Injection of Cancer Cells
Published on: August 2, 2022
Metastases to the craniovertebral junction
Hugh D Moulding1, Mark H Bilsky
1Department of Neurosurgery, Memorial Sloan-Kettering Cancer Center, New York, New York 10021, USA.

Objective:
This study reviews the relevant literature regarding the management of craniovertebral junction (CVJ) metastases. These rare tumors present significant diagnostic and treatment challenges.
Methods:
A PubMed search of cervical spine, cervical spine metastasis, craniovertebral junction, atlantoaxial spine, and metastasis radiation was conducted to define the epidemiology, imaging, and treatment protocols in the management of metastatic CVJ tumors.
Results:
CVJ tumors represent less than 1% of spinal metastases, and the literature is limited to small case series. CVJ tumors present with flexion, extension, and rotational pain, often associated with occipital neuralgia. Magnetic resonance imaging is the most sensitive imaging modality for the detection of spinal metastases, but plain x-rays, computed tomography, and [18F]2-fluoro-2-deoxy-D-glucose play a role in diagnosis and management. Conventional external beam radiation therapy or stereotactic radiosurgery effectively treat the majority of patients with normal spinal alignment or minimal fracture subluxations. Surgery should be considered in patients with fracture subluxations greater than 5 mm, or 3.5 mm subluxation with 11-degree angulation. The palliative goals for surgery favor posterior approaches only including laminectomy for decompression, without the need for anterior approaches with the associated morbidity. Occipitocervical instrumentation using screw-rod systems are effective for irreducible subluxations, but posterior strategies using C1-C2 or C1-C3 can be used for patients with reducible subluxations.
Conclusion:
Effective management of CVJ tumors using radiation and/or surgery results in significant pain and functional improvement in properly selected patients. Advanced surgical techniques and stereotactic radiation may improve outcomes with less morbidity.
More Related Videos


Related Concept Videos
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:28
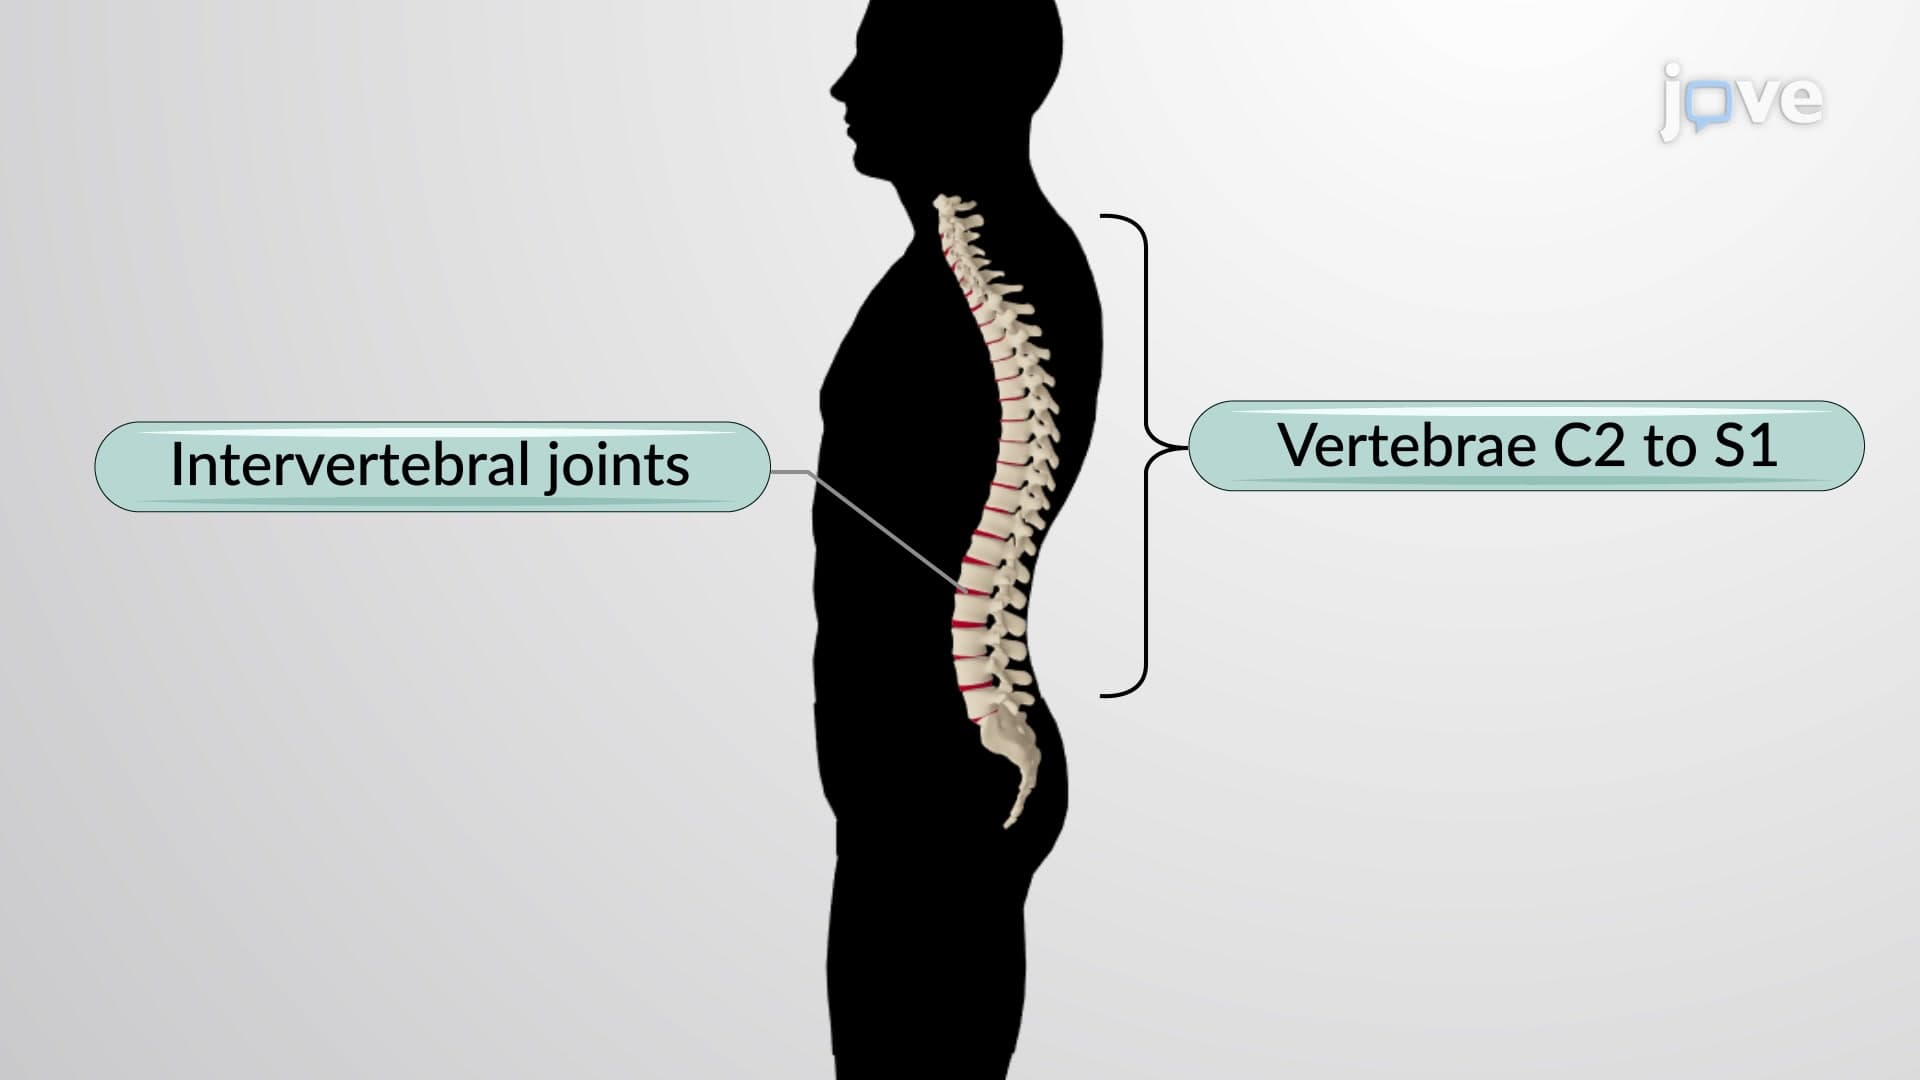
Articulations of the Vertebral Column
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...