Related Experiment Video
Updated: Jun 15, 2026
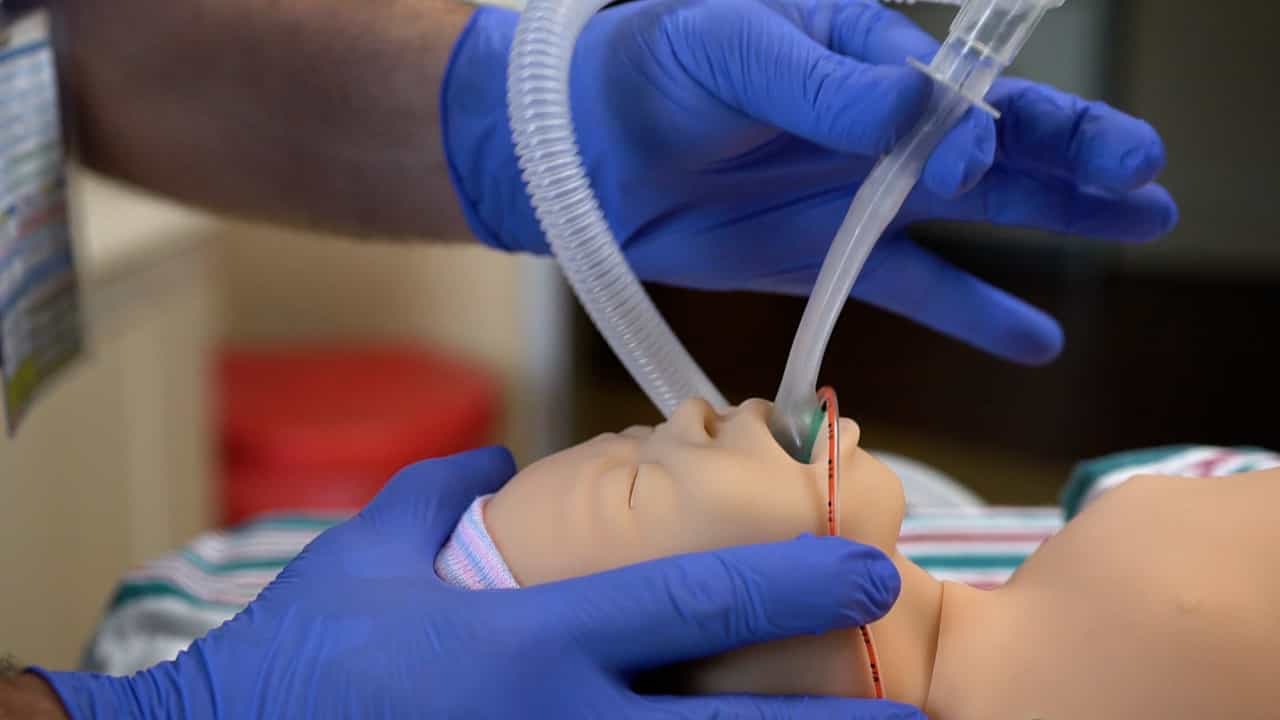
Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Use of manometry for laryngeal mask airway reduces postoperative pharyngolaryngeal adverse events: a prospective,
Edwin Seet1, Farhanah Yousaf, Smita Gupta
1Department of Anesthesia, Toronto Western Hospital, University Health Network, University of Toronto, Toronto, Ontario, Canada.

Background:
Adverse events such as pharyngolaryngeal complications are indicators of quality patient care. Use of manometry to limit the laryngeal mask airway (LMA) intracuff pressure is not currently a routine practice. This double-blind randomized trial compared pharyngolaryngeal complications in patients managed with manometers to limit the LMA intracuff pressure (<44 mmHg) with patients under routine care.
Method:
Two hundred consenting patients who underwent ambulatory surgery were randomly allocated to pressure-limiting and routine care groups. Anesthesia was induced with propofol and fentanyl, and maintained with desflurane in air-oxygen. An LMA was inserted, and the cuff was inflated as per usual practice. The patients breathed spontaneously. Research assistants measured the LMA intracuff pressure. In the pressure-limiting group, LMA intracuff pressure was adjusted to less than 44 mmHg. No intervention was performed in the routine care group. Sore throat, dysphonia, and dysphagia were assessed at 1, 2, and 24 h postoperatively. Composite pharyngolaryngeal complications were compared using chi-square test.
Results:
Baseline demographic data were comparable between groups. Mean LMA intracuff pressure was less in the pressure-limiting group versus the routine care group (40 +/- 6 vs. 114 +/- 57 mmHg, P < 0.001). The incidence of composite pharyngolaryngeal complications was significantly lower in the pressure-limiting group versus the routine care group (13.4 vs. 45.6%, P < 0.001), with a relative risk reduction of 70.6%, and a number needed to treat of three (95% CI 2.2-7.5).
Conclusion:
Reduction of LMA intracuff pressure to less than 44 mmHg lowers the incidence of postoperative pharyngolaryngeal complications. The LMA cuff pressures should be measured routinely using manometry, and deflating the intracuff pressure to less than 44 mmHg should be recommended as anesthetic best practice.
Insights
Using manometry to limit laryngeal mask airway (LMA) intracuff pressure to below 44 mmHg significantly reduces postoperative pharyngolaryngeal complications. This pressure-limiting technique should be standard anesthetic practice.
Area of Science:
- Anesthesiology
- Patient Safety
- Surgical Complications
Background:
- Pharyngolaryngeal complications are key indicators of patient care quality.
- Routine use of manometry to control laryngeal mask airway (LMA) intracuff pressure is not standard practice.
- This study investigated the impact of limiting LMA intracuff pressure on these complications.
Purpose of the Study:
- To compare the incidence of pharyngolaryngeal complications in patients managed with LMA intracuff pressure limited by manometry (<44 mmHg) versus routine care.
- To evaluate the effectiveness of a pressure-limiting strategy in reducing adverse events.
Main Methods:
- A double-blind randomized trial involving 200 ambulatory surgery patients.
- Patients were allocated to either a pressure-limiting group (LMA intracuff pressure <44 mmHg) or a routine care group.
- Pharyngolaryngeal complications (sore throat, dysphonia, dysphagia) were assessed postoperatively.
Main Results:
- Mean LMA intracuff pressure was significantly lower in the pressure-limiting group (40 mmHg) compared to the routine care group (114 mmHg).
- The incidence of composite pharyngolaryngeal complications was substantially reduced in the pressure-limiting group (13.4%) versus the routine care group (45.6%).
- A relative risk reduction of 70.6% was observed, with a number needed to treat of three.
Conclusions:
- Reducing LMA intracuff pressure to below 44 mmHg effectively lowers postoperative pharyngolaryngeal complications.
- Routine measurement of LMA cuff pressures using manometry is recommended.
- Limiting intracuff pressure to <44 mmHg should be adopted as anesthetic best practice.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...