Related Experiment Video
Updated: Jun 15, 2026

Combination of High Ligation and Intraoperative Embolization Using Polidocanol for Treatment of Varicoceles
Published on: December 22, 2023
Hemoperitoneum in pregnancy from a ruptured varix of broad ligament
Simone Giulini1, Renata Zanin, Annibale Volpe
1Mother-Infant Department, University of Modena and Reggio Emilia, via Del Pozzo 71, Modena, Italy. sgiulini@unimore.it

We present a case of a 31-year-old woman, gravida 4 para 1, pregnant at 33 + 2 weeks of gestational age with acute abdomen due to hemoperitoneum. Hemoperitoneum was suspected for non-specific symptoms such as acute abdominal pain, vomit, cardiotocography alterations and maternal acute anaemia. An emergency caesarean section was performed; 3 L of blood was present in abdomen. Careful exploration of the uterus, placenta, abdominal organs and vessels was negative; only a bleeding from a rupture in a varix of the left broad ligament was observed. Hemoperitoneum due to a ruptured uterine varix in pregnancy is a rare condition. The solution to prevent the development of maternal hypovolemic shock is an immediate surgical intervention. A good foetal prognosis principally depends from gestational age and from good hemodynamic maternal conditions.
We present a case of a 31-year-old woman, gravida 4 para 1, pregnant at 33 + 2 weeks of gestational age with acute abdomen due to hemoperitoneum. Hemoperitoneum was suspected for non-specific symptoms such as acute abdominal pain, vomit, cardiotocography alterations and maternal acute anaemia. An emergency caesarean section was performed; 3 L of blood was present in abdomen. Careful exploration of the uterus, placenta, abdominal organs and vessels was negative; only a bleeding from a rupture in a varix of the left broad ligament was observed. Hemoperitoneum due to a ruptured uterine varix in pregnancy is a rare condition. The solution to prevent the development of maternal hypovolemic shock is an immediate surgical intervention. A good foetal prognosis principally depends from gestational age and from good hemodynamic maternal conditions.

Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Varicose Veins I: Introduction
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:19
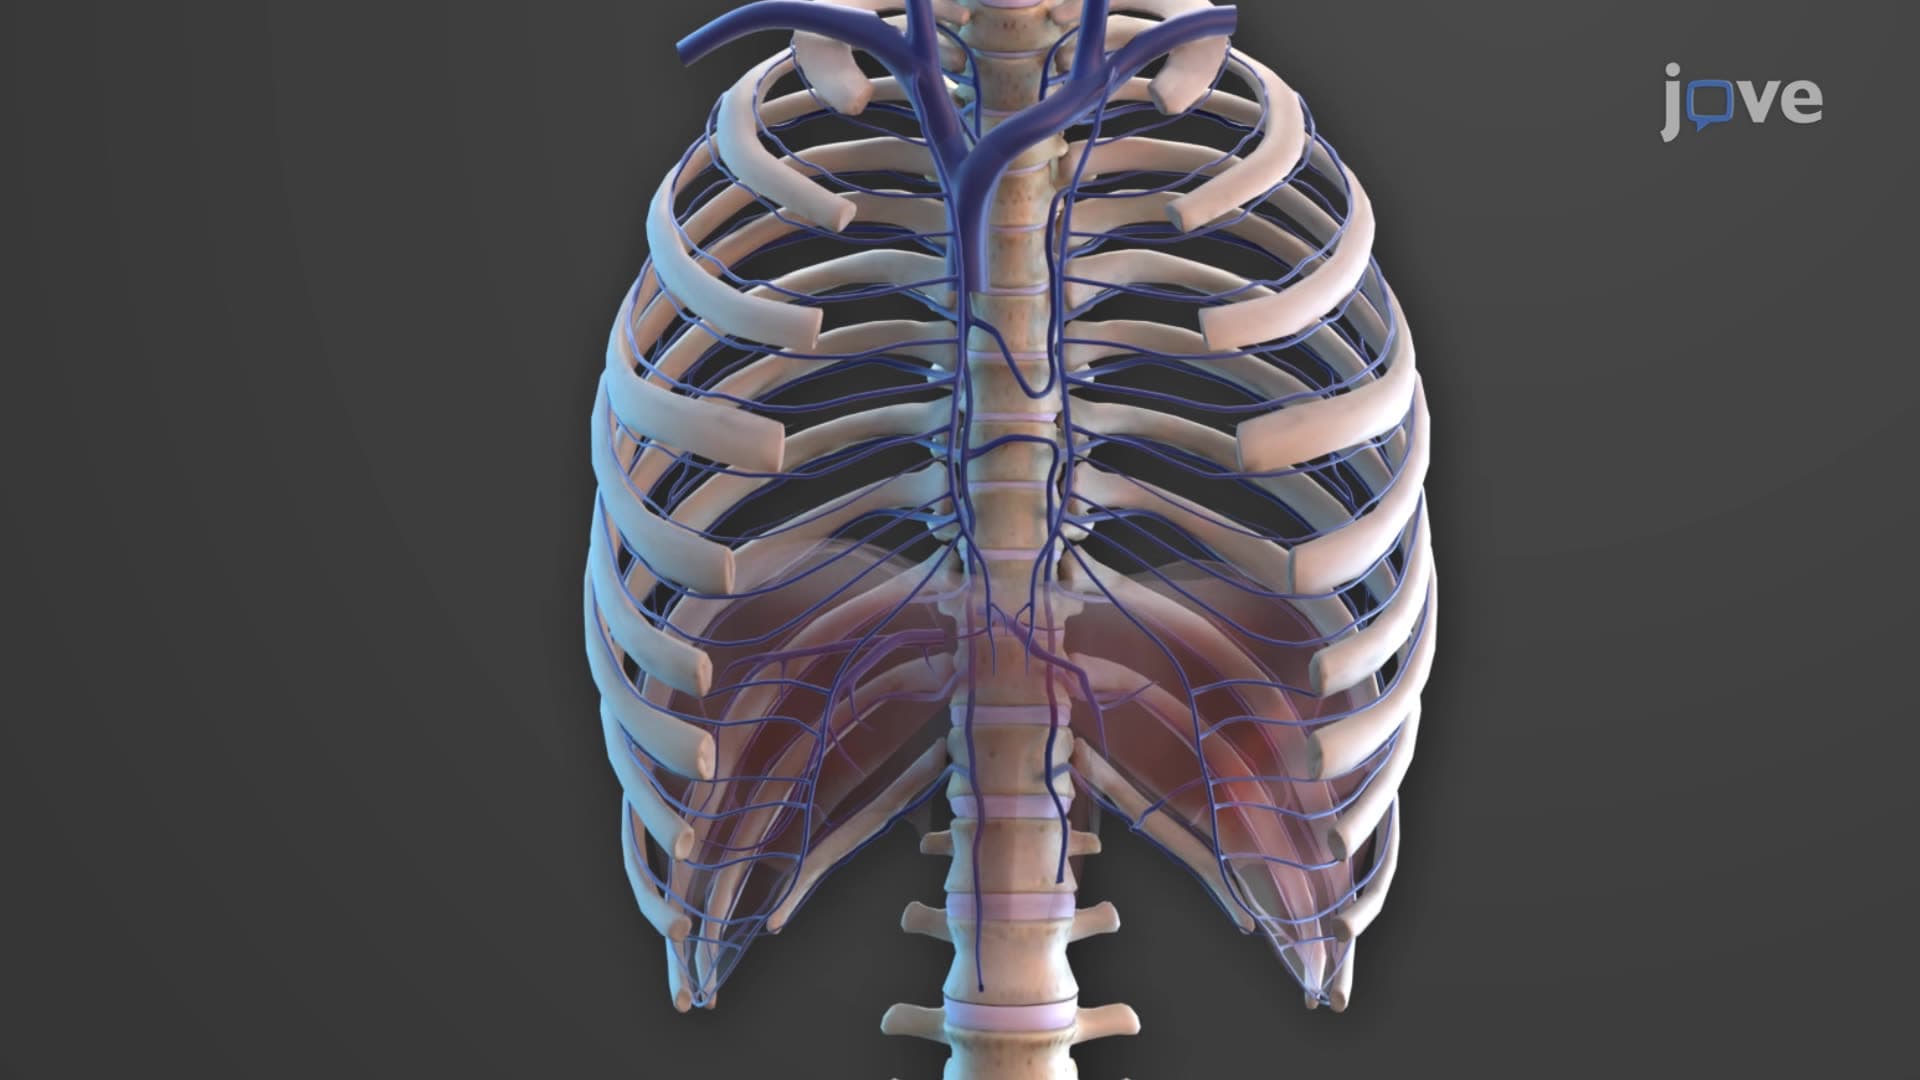
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...