Related Experiment Video
Updated: Jun 15, 2026
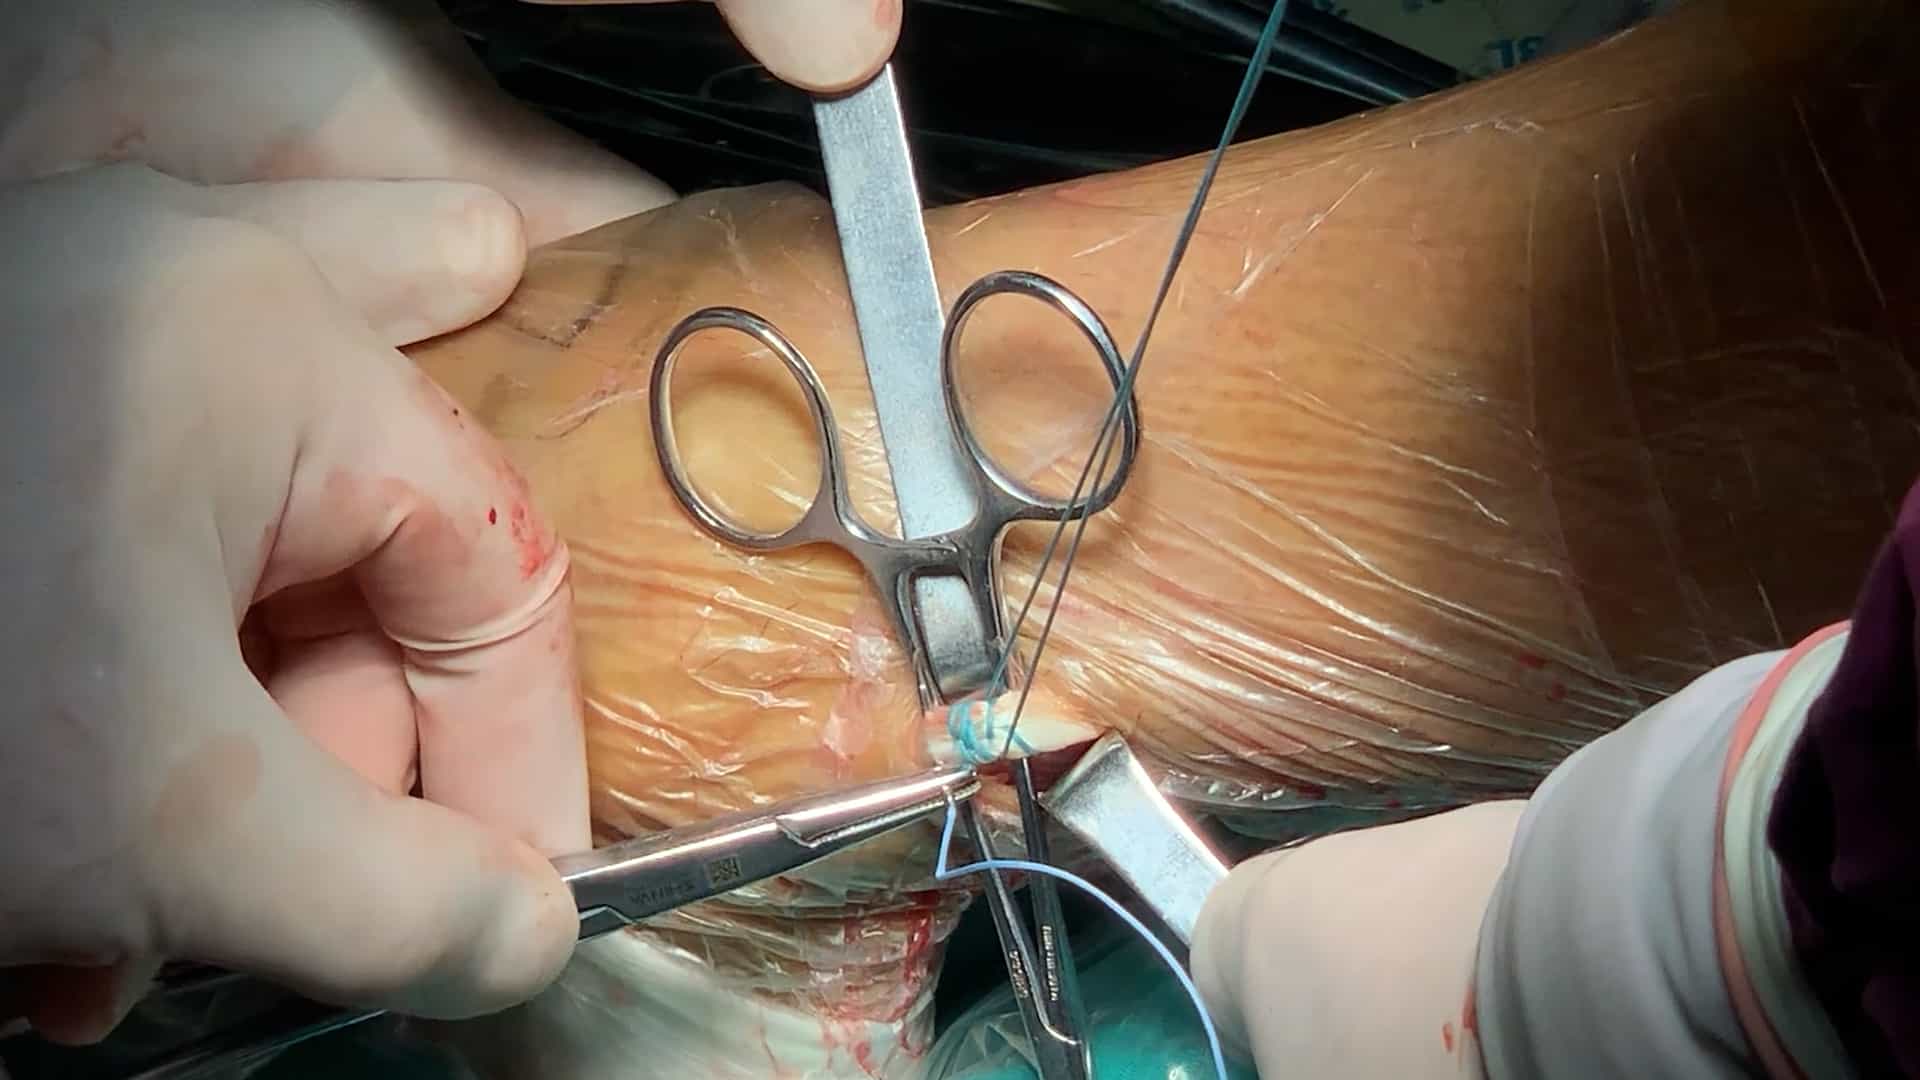

Harvesting of Peroneus Longus Tendon Autograft
Published on: September 2, 2025
The course of the superficial peroneal nerve in relation to the ankle position: anatomical study with ankle
Peter A J de Leeuw1, Pau Golanó, Inger N Sierevelt
1Department of Orthopaedic Surgery, University of Amsterdam, Academic Medical Center, PO Box 22700, 1100 DE Amsterdam, The Netherlands. p.a.deleeuw@amc.uva.nl

Abstract:
Despite the fact that the superficial peroneal nerve is the only nerve in the human body that can be made visible; iatrogenic damage to this nerve is the most frequently reported complication in anterior ankle arthroscopy. One of the methods to visualize the nerve is combined ankle plantar flexion and inversion. In the majority of cases, the superficial peroneal nerve can be made visible. The portals for anterior ankle arthroscopy are however created with the ankle in the neutral or slightly dorsiflexed position and not in combined plantar flexion and inversion. The purpose of this study was to undertake an anatomical study to the course of the superficial peroneal nerve in different positions of the foot and ankle. We hypothesize that the anatomical localization of the superficial peroneal nerve changes with different foot and ankle positions. In ten fresh frozen ankle specimens, a window, only affecting the skin, was made at the level of the anterolateral portal for anterior ankle arthroscopy in order to directly visualize the superficial peroneal nerve, or if divided, its terminal branches. Nerve movement was assessed from combined 10 degrees plantar flexion and inversion to 5 degrees dorsiflexion, standardized by the Telos stress device. Also for the 4th toe flexion, flexion of all the toes and for skin tensioning possible nerve movement was determined. The mean superficial peroneal nerve movement was 2.4 mm to the lateral side when the ankle was moved from 10 degrees plantar flexion and inversion to the neutral ankle position and 3.6 mm to the lateral side from 10 degrees plantar flexion and inversion to 5 degrees dorsiflexion. Both displacements were significant (P < 0.01). The nerve consistently moves lateral when the ankle is manoeuvred from combined plantar flexion and inversion to the neutral or dorsiflexed position. If visible, it is therefore advised to create the anterolateral portal medial from the preoperative marking, in order to prevent iatrogenic damage to the superficial peroneal nerve.
Related Concept Videos
 01:10
Ankle Joint
 01:28
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
 01:11
Pulse Assessment Sites
 01:20
Arteries of Lower Limbs
 01:15
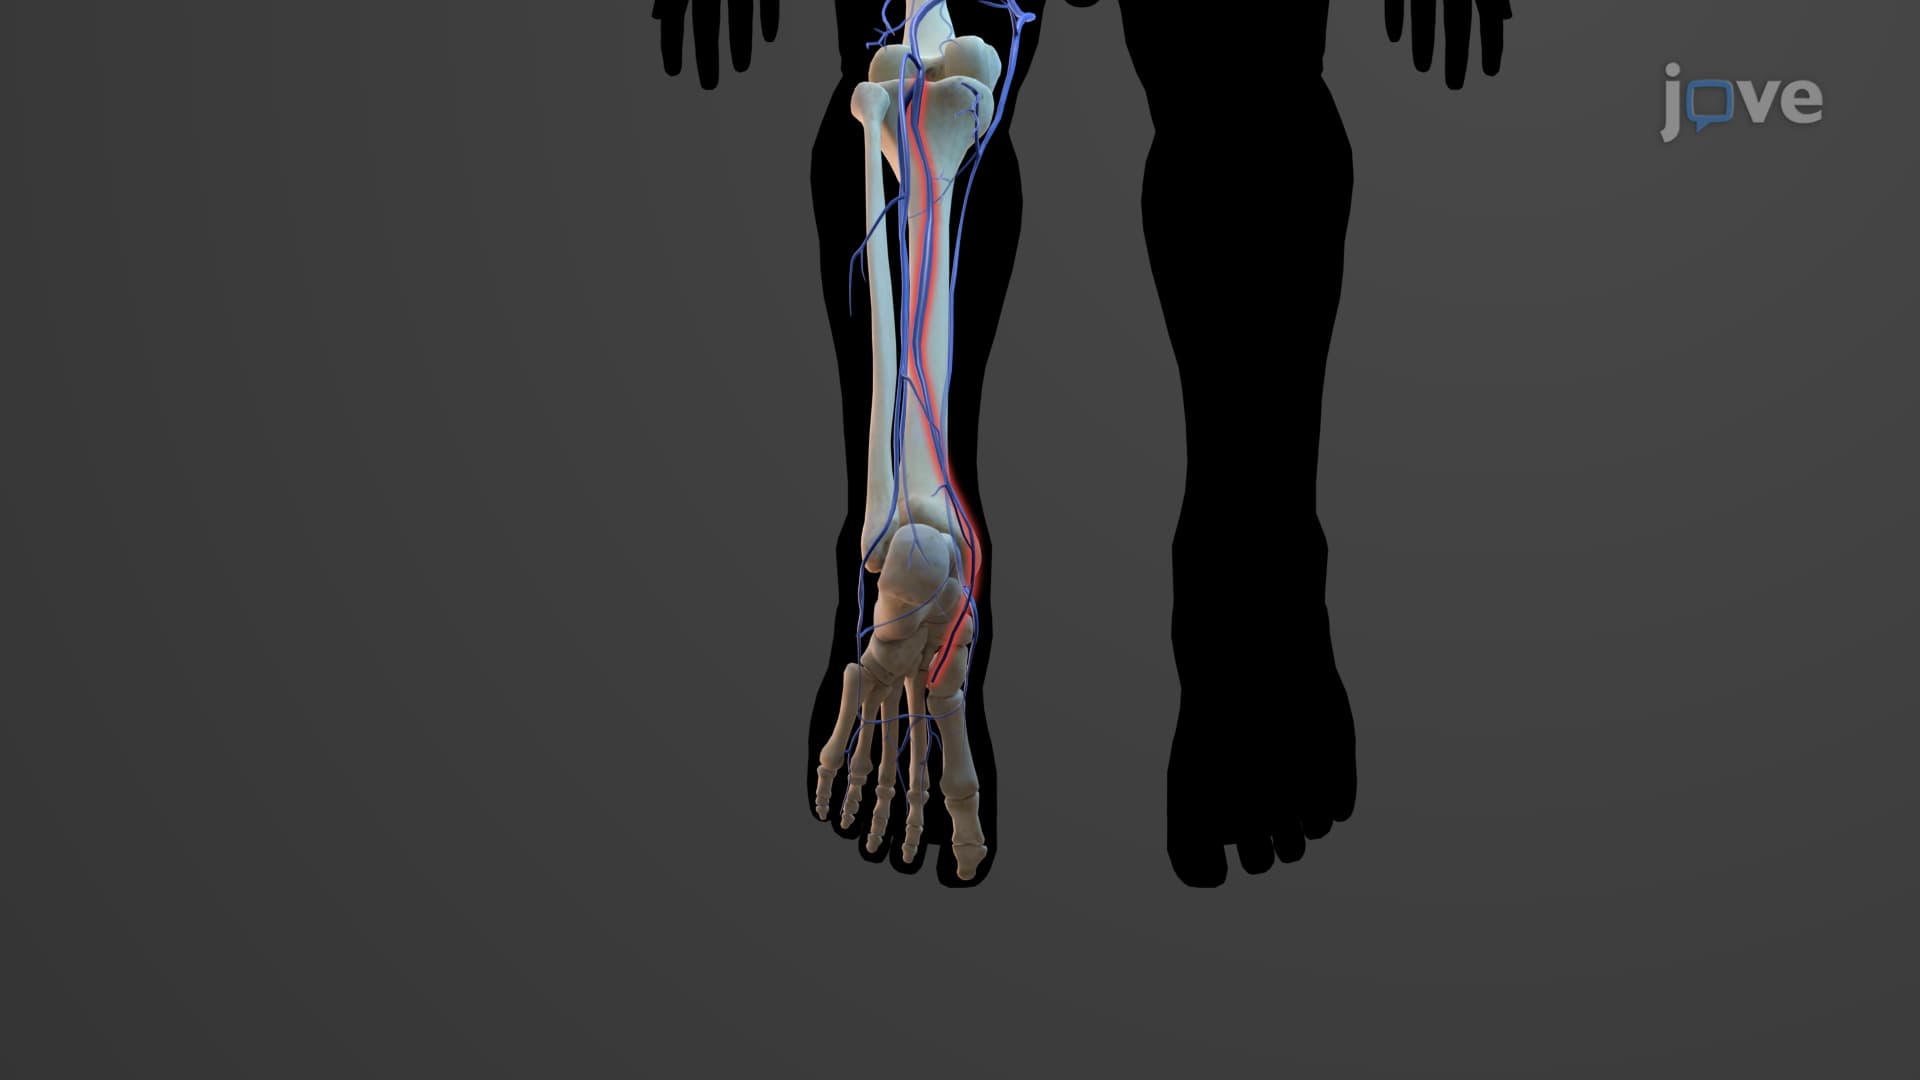
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:10
Bones of the Lower Limb: Tibia and Fibula