Related Experiment Video
Updated: Jun 15, 2026
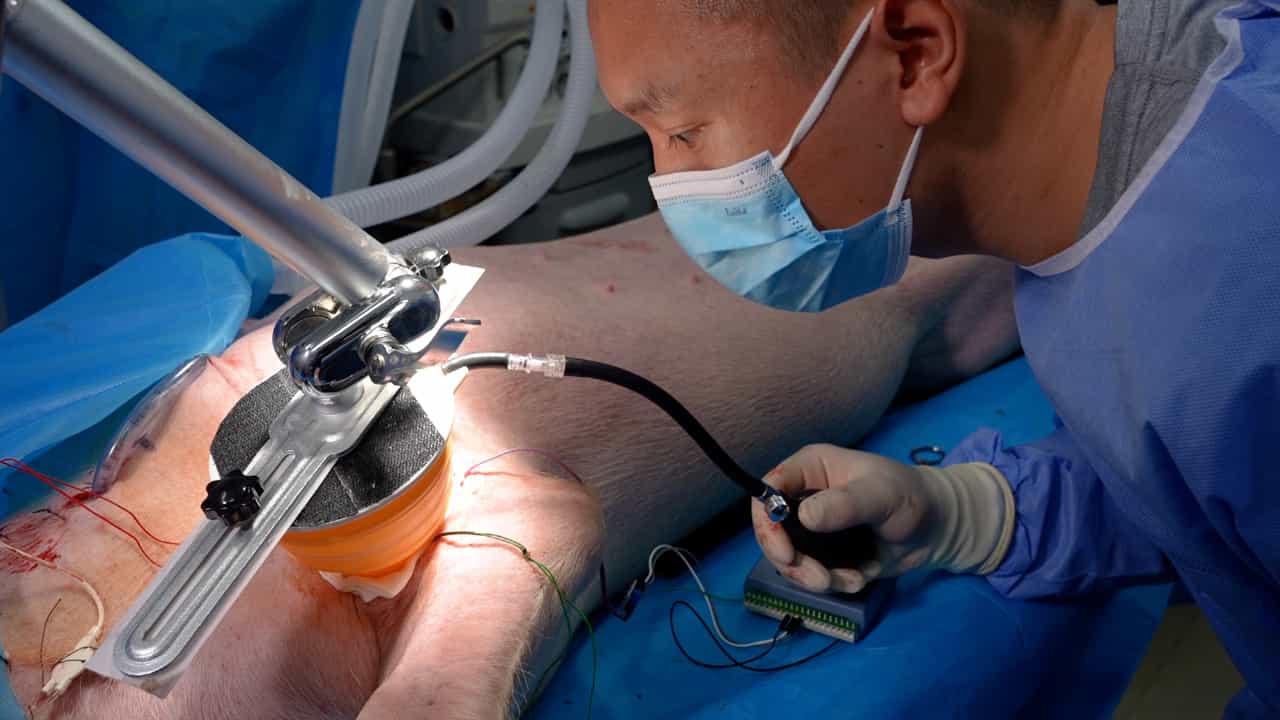

A New Hybrid Quantitative Evaluation Model for Axillary Junctional Hemorrhage in Swine
Published on: December 6, 2024
[Countermeasure for obstetric hemorrhage]
1Department of Obstetrics and Gynecology, Nippon Medical School, Tokyo 113-8603.

Although the number of maternal death in Japan has decreased especially since 1990's and its total number has reached the level of developed countries, obstetric hemorrhage is still equally important as obstetric embolism and hypertension in pregnancy as a cause of maternal death. Intrapartum abnormal bleeding is defined as hemorrhage which amounts to more than 500 ml during intrapartum period by Japan Society of Obstetrics and Gynecology (JSOG). However, according to the official register of peripartum data in Japan, the upper normal limit (mean + 1.5 SD) of the amount of hemorrhage during intrapartum period was 900 g at vaginal singleton delivery, 1600 g at singleton cesarean delivery, 1900 g at multifetal vaginal delivery and 2600 g at multifetal cesarean delivery. Thus, upper normal limit is varied depending on mode of deliveries and fetal number. The character of obstetric DIC is marked consumptive coagulopathy and increased fibrinolytic system. Principal strategy for treatment of obstetric DIC is compensation of expended coagulating factors. Thus, the most important strategy is to administer FFP However, it is necessary to be unfreezed for administration of FFP, and it is time-consuming. Prompt and firm decision for administration of FFP is important. Priority of administration of platelet concentrate is not high. Rather the use of antithrombin should be considered. Guideline of response to obstetric critical hemorrhage has been tentatively constructed by Japanese Society of Anesthesiologists, JSOG and other related academic societies. According to the guideline, recommended medical intervention depends on the shock index. At the extremely severe clinical state like placenta previa with accreta and placental abruption, multidisciplinary and prompt approach fulfills very important role to bring through. Strategy of treatment for obstetric DIC and the guideline of response to obstetric critical hemorrhage are also important at such state. Level 1 and other medical devices for critical care also become strong tools for severe cases. However, the most important is adequate and prompt estimation and direction by workforce.
Although the number of maternal death in Japan has decreased especially since 1990's and its total number has reached the level of developed countries, obstetric hemorrhage is still equally important as obstetric embolism and hypertension in pregnancy as a cause of maternal death. Intrapartum abnormal bleeding is defined as hemorrhage which amounts to more than 500 ml during intrapartum period by Japan Society of Obstetrics and Gynecology (JSOG). However, according to the official register of peripartum data in Japan, the upper normal limit (mean + 1.5 SD) of the amount of hemorrhage during intrapartum period was 900 g at vaginal singleton delivery, 1600 g at singleton cesarean delivery, 1900 g at multifetal vaginal delivery and 2600 g at multifetal cesarean delivery. Thus, upper normal limit is varied depending on mode of deliveries and fetal number. The character of obstetric DIC is marked consumptive coagulopathy and increased fibrinolytic system. Principal strategy for treatment of obstetric DIC is compensation of expended coagulating factors. Thus, the most important strategy is to administer FFP However, it is necessary to be unfreezed for administration of FFP, and it is time-consuming. Prompt and firm decision for administration of FFP is important. Priority of administration of platelet concentrate is not high. Rather the use of antithrombin should be considered. Guideline of response to obstetric critical hemorrhage has been tentatively constructed by Japanese Society of Anesthesiologists, JSOG and other related academic societies. According to the guideline, recommended medical intervention depends on the shock index. At the extremely severe clinical state like placenta previa with accreta and placental abruption, multidisciplinary and prompt approach fulfills very important role to bring through. Strategy of treatment for obstetric DIC and the guideline of response to obstetric critical hemorrhage are also important at such state. Level 1 and other medical devices for critical care also become strong tools for severe cases. However, the most important is adequate and prompt estimation and direction by workforce.

Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...