Related Experiment Video
Updated: Jun 15, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Pulmonary effects of red blood cell transfusion in critically ill, non-bleeding patients
A D Cornet1, E Zwart, S D K Kingma
1Department of Intensive Care and Institute for Cardiovascular Research, Vrije Universiteit Medical Center, 1081 HV Amsterdam, The Netherlands.

Abstract:
The aim of the study is to evaluate the effects of red blood cell (RBC) transfusions on pulmonary parameters in critically ill, non-bleeding patients. Retrospective chart analysis was performed on critically ill patients without overt bleeding in the intensive care unit (ICU) of a university hospital. In 83 patients in a 5-month period, who had received at least 1 RBC unit and stayed at least 24 h in the ICU, 199 transfusions of median 2 RBCs per transfusion (n = 504) were studied. Pulmonary parameters were retrieved during the period between 24 h before the start of transfusion and 24-48 h after transfusion. Outcome was assessed. The P(a)O(2)/F(I)O(2) dose-dependently decreased from 250 +/- 105 at baseline to 240 +/- 102 mmHg at 24 h after RBC transfusion (P = 0.003), irrespective of acute lung injury at baseline and RBC storage time. The lung injury score (LIS) also increased dose-dependently, whereas, at 48 h, oxygenation and LIS largely returned to baseline. For every seven RBCs transfused, the LIS transiently increased by 1 unit. There were no changes in haemodynamics, lung mechanics or chest radiography. The total number of RBCs given in the ICU did not directly contribute to ICU and 1-year mortality prediction. Transfusion of RBCs decreases oxygenation thereby increasing the LIS, dose-dependently and transiently, in a heterogeneous population of critically ill, non-bleeding patients, independent of prior cardiorespiratory status and RBC storage time. The effects are subtle, may go unseen and unreported and may represent subclinical transfusion-related acute lung injury. They do not adversely affect outcome, even at 1-year follow-up.

Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:10
Atelectasis II: Pathophysiology
 01:20
Respiration and Gaseous Exchange
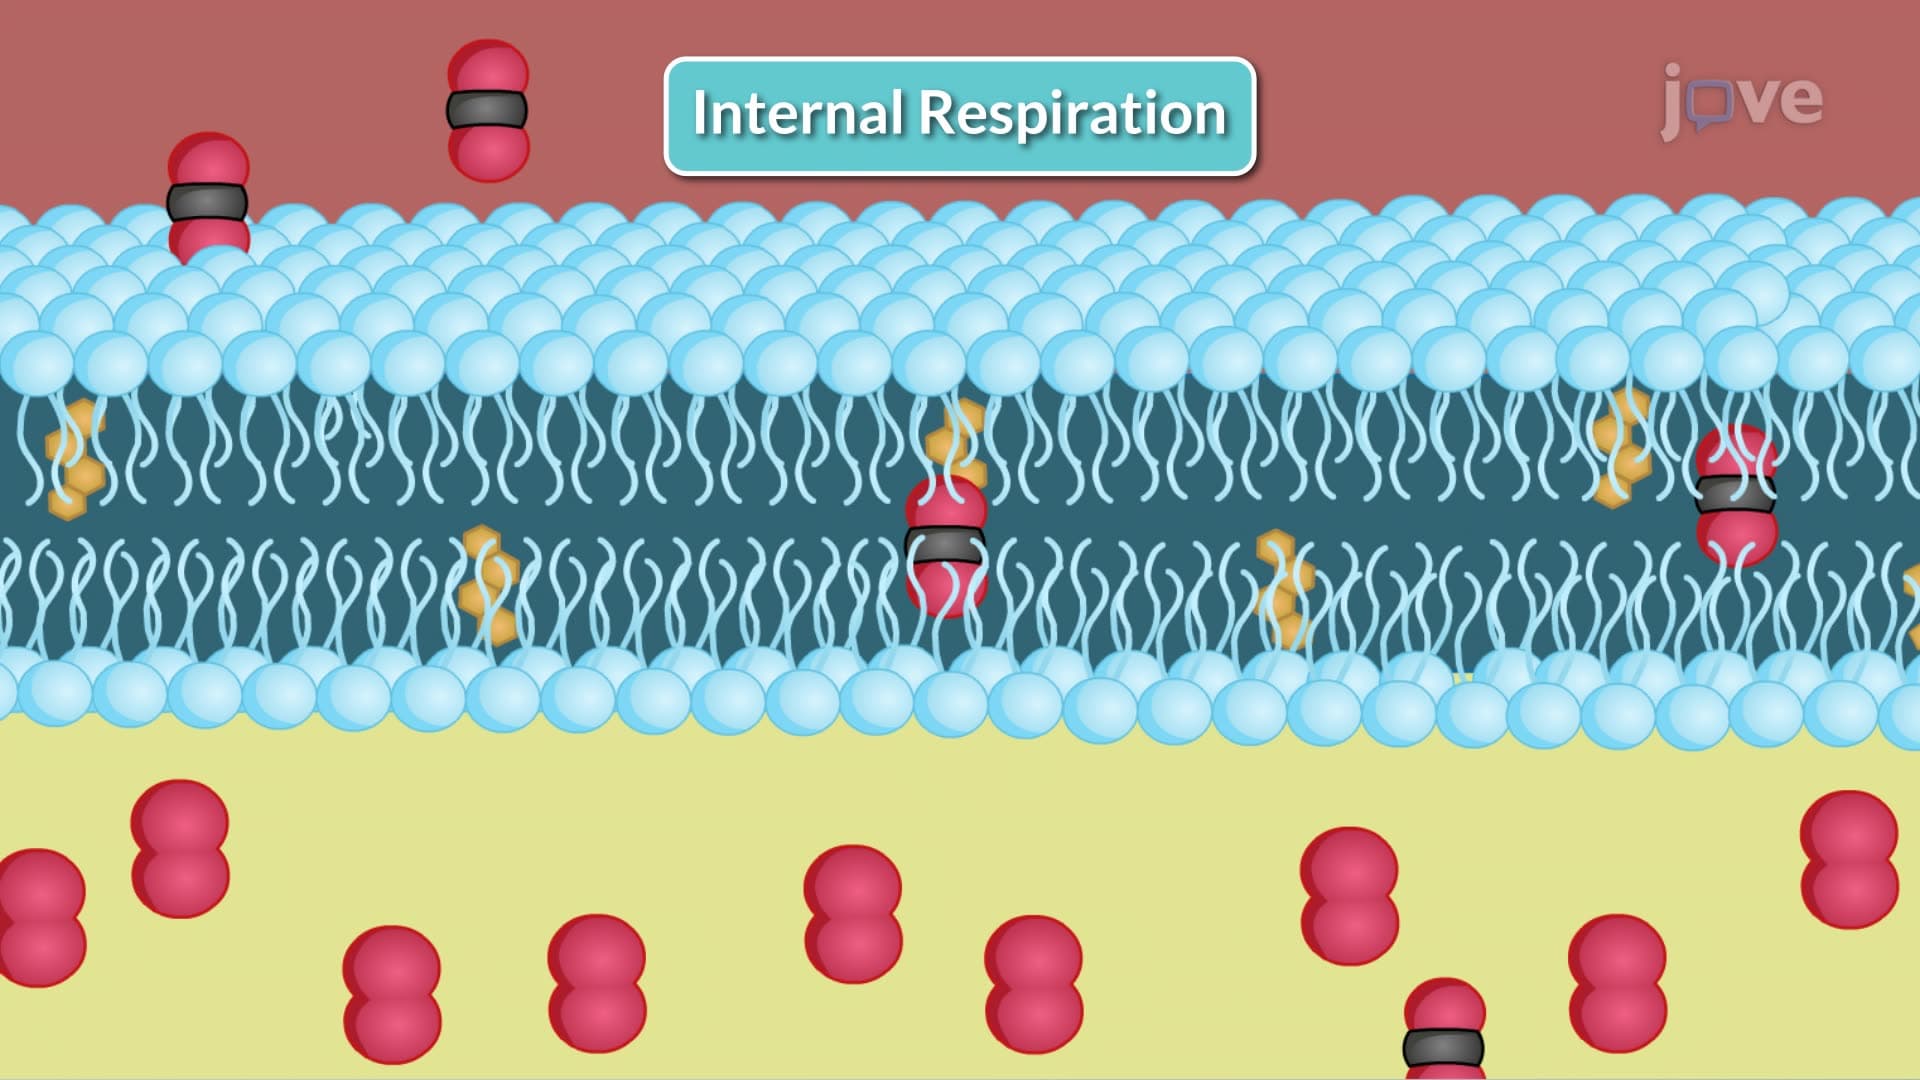
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:29
Pulmonary Embolism I: Introduction
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...