Related Experiment Video
Updated: Jun 15, 2026
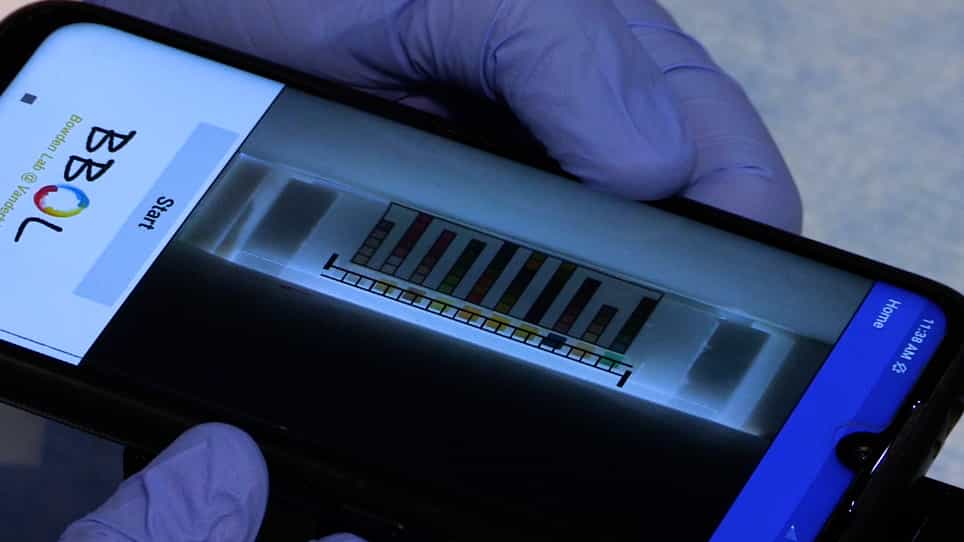

Low-Cost, Volume-Controlled Dipstick Urinalysis for Home-Testing
Published on: May 8, 2021
A cost-effectiveness analysis of screening urine dipsticks in well-child care
Deepa L Sekhar1, Li Wang, Christopher S Hollenbeak
1Penn State Hershey Children's Hospital, Department of Pediatrics, HS83, 500 University Dr, Hershey, PA 17033, USA. dsekhar@hmc.psu.edu

Insights
Routine urine dipstick screening for chronic kidney disease (CKD) in children is not cost-effective. The analysis shows it is a poor screening test, supporting updated pediatric guidelines against its use.
Area of Science:
- Pediatric Nephrology
- Health Economics
- Clinical Practice Guidelines
Background:
- The American Academy of Pediatrics updated guidelines in 2007 recommending against routine urine screening for chronic kidney disease (CKD) in children.
- Pediatricians may not be fully aware of this guideline change, necessitating an evaluation of the current practice.
- Understanding the cost-effectiveness from a primary care perspective is crucial for resource allocation.
Purpose of the Study:
- To evaluate the cost-effectiveness of using urine dipstick urinalysis for detecting chronic kidney disease (CKD) in children.
- To assess the diagnostic yield and economic viability of this screening method for primary care practitioners.
- To provide data supporting the updated American Academy of Pediatrics guidelines.
Main Methods:
- A decision analysis model was employed to compare a screening strategy using dipstick urinalysis against a no-screening strategy.
- Data on the incidence of hematuria and proteinuria in children were sourced from published cohort studies.
- Direct costs were estimated from the primary care provider's viewpoint, with the incremental cost-effectiveness ratio (ICER) as the key metric.
Main Results:
- The no-screening strategy incurred zero costs and diagnosed no cases of CKD.
- The dipstick screening strategy cost an expected $3.47 per patient, including costs for repeat testing due to false positives.
- One case of CKD was diagnosed for every 800 children screened, resulting in an ICER of $2779.50 per diagnosed case.
Conclusions:
- Urine dipstick urinalysis is an inexpensive but ineffective screening tool for pediatric chronic kidney disease (CKD).
- The procedure is not cost-effective for primary care providers, with a high cost per case diagnosed.
- These findings reinforce the American Academy of Pediatrics' revised guidelines and highlight the need for clinicians to consider cost-effectiveness in preventive care.
Objective:
Despite data suggesting that routine urine screening for chronic kidney disease (CKD) has low diagnostic yield and the American Academy of Pediatrics 2007 recommendation to discontinue this screening, pediatricians may not have recognized this change. Because the new recommendation marks a major alteration in the practice guidelines, we sought to evaluate the cost-effectiveness of dipstick urinalysis for detection of CKD from the primary care practitioner's perspective.
Methods:
Decision analysis was used to model a screening dipstick urinalysis strategy relative to a no-screening strategy. Data on the incidence of hematuria and proteinuria in children were derived from published reports of large cohorts of school-aged children. Direct costs were estimated from the perspective of the primary care practitioner. The measure of effectiveness was the rate of diagnoses of CKD. Cost-effectiveness was evaluated by using an incremental cost-effectiveness ratio.
Results:
Expected costs and effectiveness for the no-screening strategy were 0 dollars because no resources were used and no cases of CKD were diagnosed. The screening strategy involved a cost per dipstick of 3.05 dollars. Accounting for both true-positive and false-positive initial screens, 14.2% of the patients required a second dipstick as per typical clinical care, bringing the expected cost of the screening strategy to 3.47 dollars per patient. In the screening strategy, 1 case of CKD was diagnosed per 800 screened, and the incremental cost-effectiveness ratio was 2779.50 dollars per case diagnosed.
Conclusions:
Urine dipstick is inexpensive, but it is a poor screening test for CKD and a cost-ineffective procedure for the primary care provider. These data support the change in the American Academy of Pediatrics guidelines on the use of screening dipstick urinalysis. Clinicians must consider the cost-effectiveness of preventive care procedures to make better use of available resources.
More Related Videos
 13:35
A Convenient Method for Extraction and Analysis with High-Pressure Liquid Chromatography of Catecholamine Neurotransmitters and Their Metabolites
Published on: March 1, 2018
 10:17
High-throughput and Comprehensive Drug Surveillance Using Multisegment Injection-Capillary Electrophoresis-Mass Spectrometry
Published on: April 23, 2019
Related Concept Videos
 01:29
Urine Studies I: Urinalysis
 01:26
Urine Studies II: Urine Culture and Sensitivity Test
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care