Related Experiment Video
Updated: Jun 15, 2026
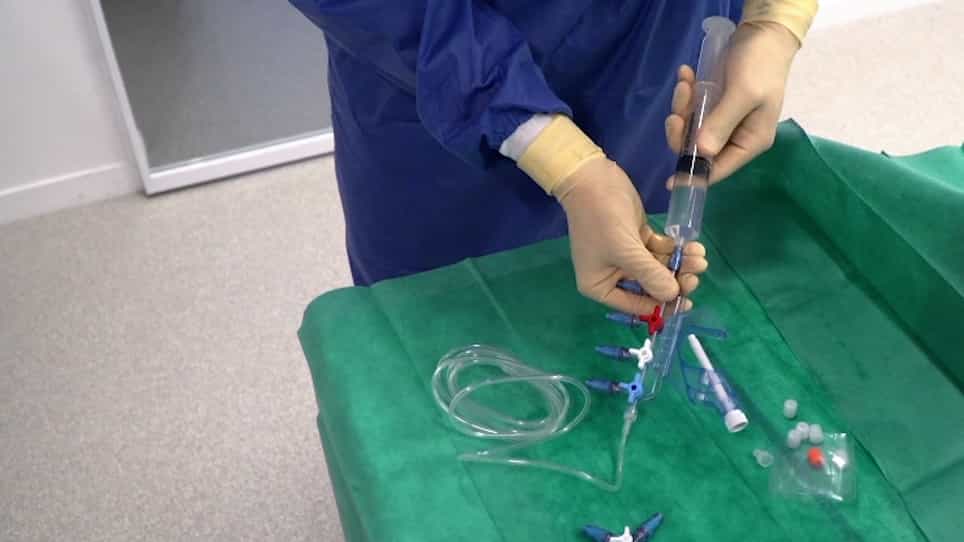

A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Clinically-indicated replacement versus routine replacement of peripheral venous catheters
Joan Webster1, Sonya Osborne, Claire Rickard
1Centre for Clinical Nursing, Royal Brisbane and Women's Hospital, Level 2, Building 34, Butterfield Street, Herston, QLD, Australia, 4029.

Background:
Centers for Disease Control Guidelines recommend replacement of peripheral intravenous (IV) catheters every 72 to 96 hours. Routine replacement is thought to reduce the risk of phlebitis and bacteraemia. Catheter insertion is an unpleasant experience for patients and replacement may be unnecessary if the catheter remains functional and there are no signs of inflammation. Costs associated with routine replacement may be considerable.
Objectives:
To assess the effects of removing peripheral IV catheters when clinically indicated compared with removing and re-siting the catheter routinely.
Search Strategy:
The Cochrane Peripheral Vascular Diseases Group searched their Specialised Register (last searched October 2009) and the Cochrane Central Register of Controlled Trials (CENTRAL) (last searched Issue Issue 4, 2009). We also searched MEDLINE (last searched October 2009).
Selection Criteria:
Randomised controlled trials that compared routine removal of peripheral IV catheters with removal only when clinically indicated in hospitalised or community dwelling patients receiving continuous or intermittent infusions.
Data Collection And Analysis:
Three review authors independently assessed trial quality and extracted data.
Main Results:
In five trials (3408 participants) there was a 44% reduction in suspected catheter-related bacteraemia in the clinically-indicated group (0.2 versus 0.4%) but this was not statistically significant (odds ratio (OR) 0.57; 95% confidence interval (CI) 0.17 to 1.94; P = 0.37). Phlebitis was assessed in six trials (3455 patients); there was a non-significant increase in phlebitis in the clinically-indicated group (9% versus 7.2%); the OR was 1.24 (95% CI 0.97 to 1.60; P = 0.09). We also measured phlebitis per 1000 device days using data from five trials, (8779 device days). No statistical differences in the incidence of phlebitis per 1,000 device days was found (clinically indicated 1.6 cases per 1,000 catheter days versus 1.5 cases per 1,000 catheter days in the routine-replacement group).The combined OR was 1.04 (95% CI 0.81 to 1.32; P = 0.77). Cost was measured in two trials (961 patients). Cannulation costs were significantly reduced in the clinically-indicated group (mean difference (MD) -6.21; 95% CI -9.32 to -3.11; P = < 0.000).
Authors' Conclusions:
The review found no conclusive evidence of benefit in changing catheters every 72 to 96 hours. Consequently, health care organisations may consider changing to a policy whereby catheters are changed only if clinically indicated. This would provide significant cost savings and would also be welcomed by patients, who would be spared the unnecessary pain of routine re-sites in the absence of clinical indications.
Related Concept Videos
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:30
Continuous Renal Replacement Therapy
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:25
Hemodialysis I: Introduction
 01:29
Endocarditis IV: Nursing Management
 01:24
Hemodialysis II: Procedure and Complications