Dowling-Degos disease: case report and review of the literature

Aleksandra Batycka-Baran1, Wojciech Baran, Anita Hryncewicz-Gwozdz

  • 1Department of Dermatology, Venereology and Allergology, Wroclaw Medical University, Wroclaw, Poland.

Dermatology (Basel, Switzerland)
|March 25, 2010
PubMed

Related Concept Videos

Degenerative Disc Disease I: Introduction01:27

Degenerative Disc Disease I: Introduction
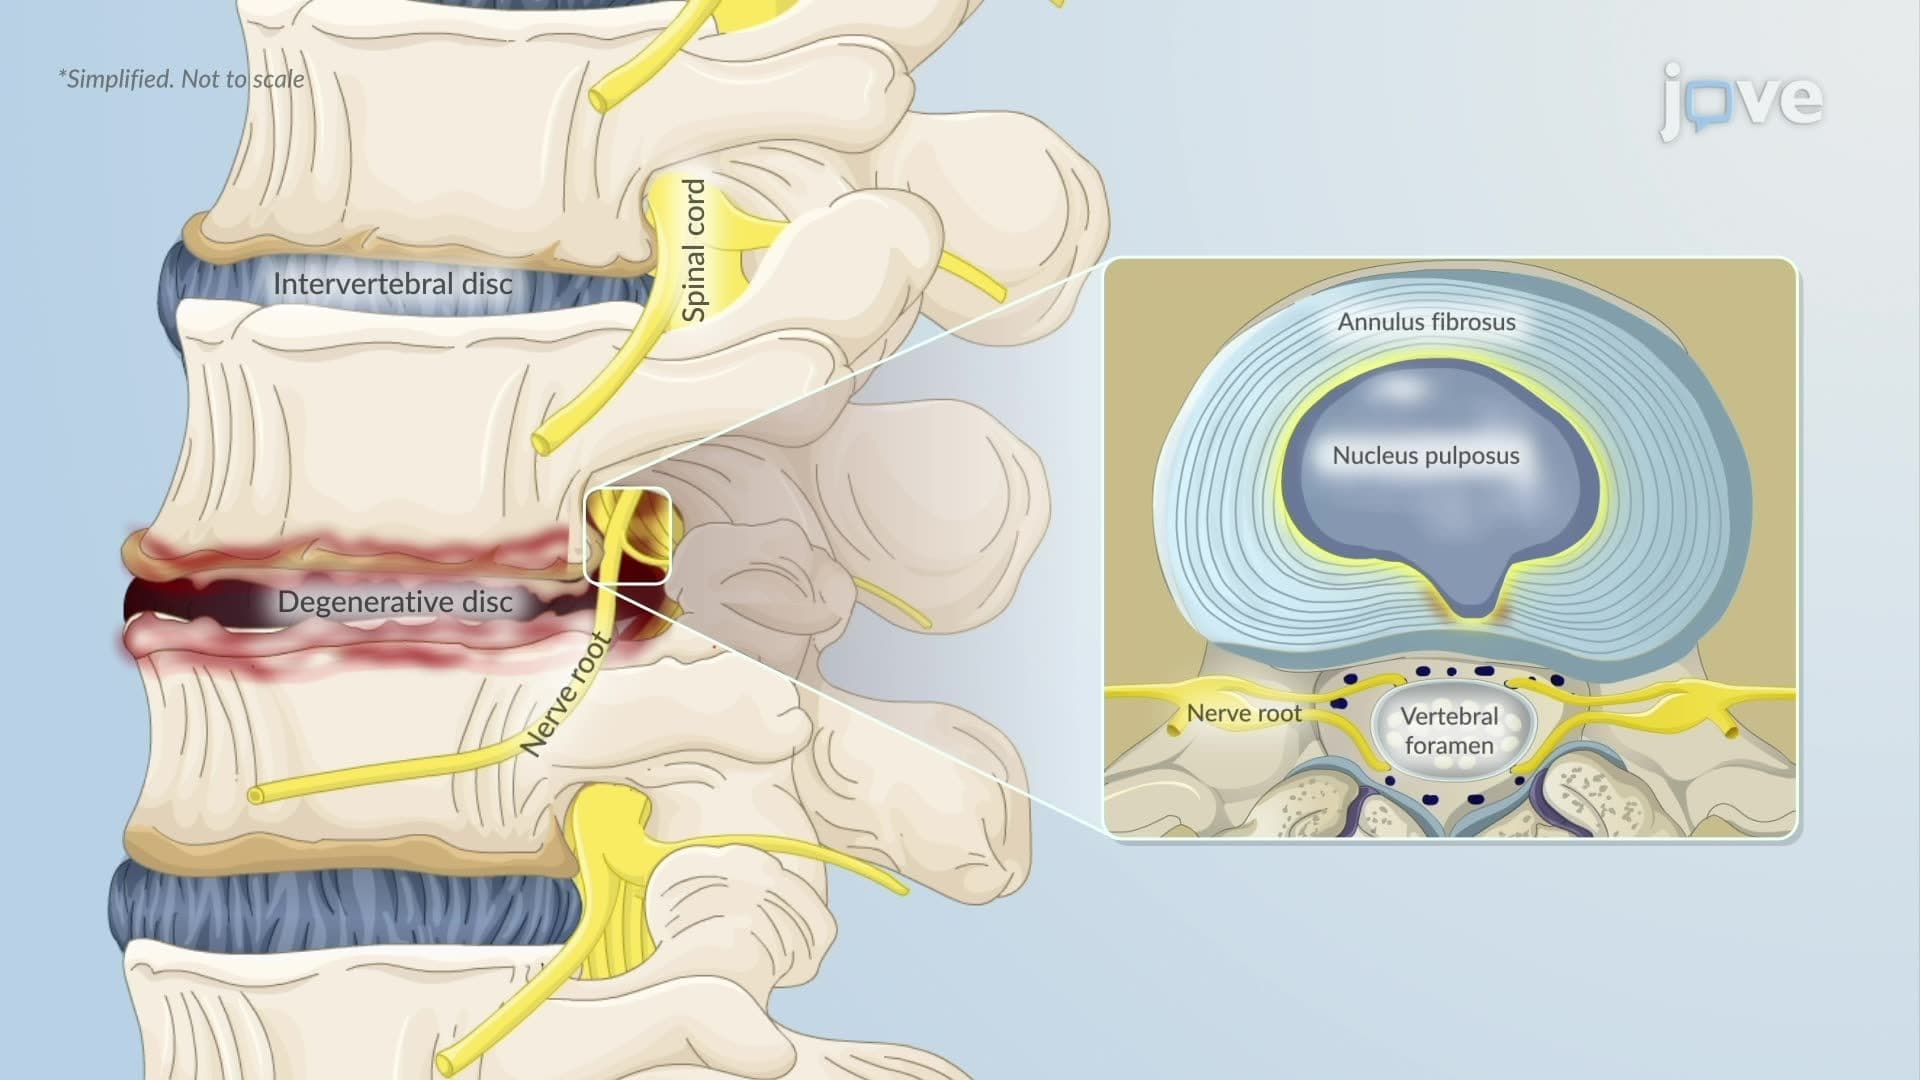
Degenerative disc disease is a chronic condition in which intervertebral discs gradually lose structure and function. It is not infectious or autoimmune; rather, it results from age-related biochemical and mechanical changes, influenced by genetic, metabolic, and environmental factors.Structure and Function of DiscsThe spine contains 23 intervertebral discs that absorb load, distribute forces, maintain spacing, and allow flexibility. Each disc consists of a nucleus pulposus, a gel-like core...
Degenerative Disc Disease ll: Pathophysiology01:23

Degenerative Disc Disease ll: Pathophysiology

The symptoms of degenerative disc disease arise from a combination of mechanical compression, vascular compromise, and biochemical inflammation, which together disrupt nerve function and produce pain.Mechanical CompressionDisc degeneration reduces height and elasticity, predisposing to herniation of the nucleus pulposus, a major cause of radicular pain. Herniations may be protrusion (bulging with intact annulus), extrusion (nucleus extends beyond disc but remains connected), or sequestration...
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation01:21

Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation

Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis01:25

Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis

Type 2 diabetes mellitus develops gradually and is often asymptomatic in early stages.Clinical ManifestationsWhen symptoms appear, they include fatigue, blurred vision, pruritus, delayed wound healing, and recurrent infections, particularly candidal infections. Peripheral neuropathy may present as numbness or tingling in the extremities. Classic hyperglycemia symptoms—polyuria, polydipsia, and polyphagia—are less common. Most patients are overweight and frequently have associated hypertension...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology

Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations

Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...

