Related Experiment Video
Updated: Jun 14, 2026
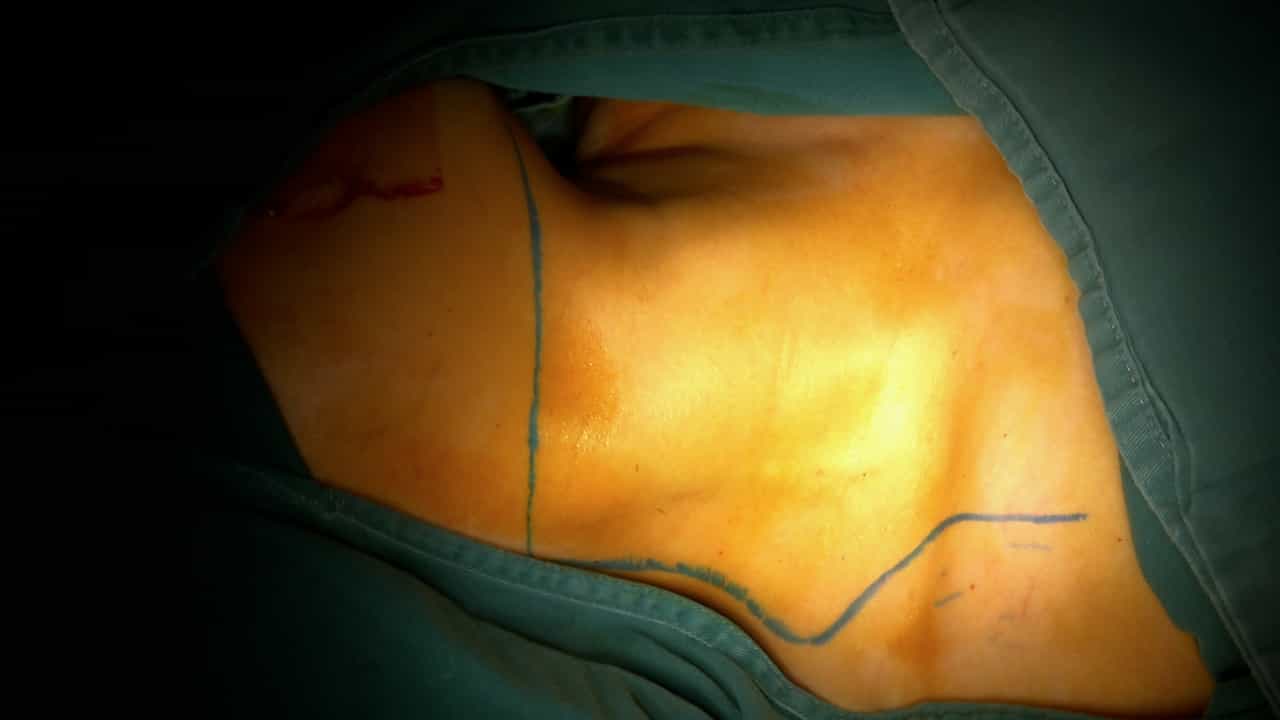

Modified Radical Neck Dissection for Cervical Metastasis
Published on: February 20, 2026
Cervical lymph node dissection for metastatic testicular cancer
M G van Vledder1, J A van der Hage, W J Kirkels
1Department of Surgery, Erasmus Medical Center, Daniel den Hoed Cancer Center, Rotterdam, The Netherlands.

Introduction:
Despite high response rates to systemic chemotherapy, 30% of patients with advanced stage testicular carcinoma will have extra-retroperitoneal residual masses that require resection. Most often, these are located in the lungs and mediastinum and neck. Limited data are available concerning the incidence, surgical management, and follow-up of neck metastasis arising from a testicular primary tumor.
Methods:
We retrospectively reviewed all 665 patients who were referred to a tertiary referral center with the diagnosis of testicular cancer from January 1997 to June 2009 for the presence of cervical metastases. Patients who underwent concomitant surgical therapy were identified and analyzed. Clinical and pathological data were collected from patient records, including radiology and pathology reports. Furthermore, data on primary treatment strategy, chemotherapeutic regimens, timing of surgical procedures, complications, disease recurrence, and follow-up were collected.
Results:
Twenty-six patients (4%) had cervical lymph node metastasis. The majority (n = 19) had multiple ERP sites. Nine patients (35%) underwent selective neck dissection: in six patients, this was indicated because of residual masses after chemotherapy, and in three patients, cervical masses represented a late and distant relapse of previously treated disease. Viable cancer cells were present in the resected specimen only in these three patients. Seven patients are currently without evidence of disease. Two patients died of disseminated disease.
Conclusions:
Cervical lymph node metastases originating from testicular cancer are rare but are more commonly observed in patients with advanced stage disease. Selective neck dissection can be safely performed both after chemotherapy and in the case of recurrent disease.
Insights
Cervical lymph node metastasis from testicular cancer is rare, occurring in 4% of advanced cases. Selective neck dissection is a safe and effective treatment option for these patients, even after chemotherapy or for recurrent disease.
Area of Science:
- Oncology
- Surgical Oncology
- Urologic Oncology
Background:
- Advanced testicular carcinoma often presents with extra-retroperitoneal residual masses requiring resection.
- Cervical metastasis from testicular tumors is uncommon, with limited data on its incidence and management.
- Neck involvement necessitates understanding surgical strategies and follow-up protocols.
Purpose of the Study:
- To investigate the incidence, surgical management, and outcomes of cervical lymph node metastasis in testicular cancer patients.
- To evaluate the safety and efficacy of selective neck dissection for managing neck metastases.
- To identify factors influencing disease recurrence and patient survival.
Main Methods:
- Retrospective review of 665 testicular cancer patients diagnosed between 1997 and 2009.
- Identification and analysis of patients with cervical metastases who underwent surgical therapy.
- Collection of clinical, pathological, treatment, and follow-up data.
Main Results:
- Cervical lymph node metastasis was identified in 26 patients (4%), predominantly in advanced disease stages.
- Nine patients underwent selective neck dissection, six post-chemotherapy and three for late relapse.
- Seven patients achieved disease-free status; two succumbed to disseminated disease.
Conclusions:
- Cervical lymph node metastases from testicular cancer are rare but associated with advanced disease.
- Selective neck dissection is a safe and viable surgical approach for managing these metastases.
- Effective management strategies are crucial for improving outcomes in patients with advanced testicular cancer and neck involvement.
