Access to care for children with fractures
Related Experiment Video
Updated: Jun 14, 2026

Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Christopher Iobst1, Wesley King, Avi Baitner
1Miami Children's Hospital, Miami, FL 33155, USA. christopher.iobst@mch.com

Background:
Earlier studies have found that children with fractures and PPO insurance have no access problems to orthopaedic care, but children with Medicaid have problems with access to orthopaedic care.
Methods:
Fifty randomly selected orthopaedic offices in each of the 2 counties served by a children's hospital were telephoned to seek an appointment for a fictitious 10-year-old boy with a forearm fracture. Each office was called twice, 1 time reporting that the child had PPO insurance and 1 time that he was having Medicaid. In the second arm of the study, data including insurance status were prospectively collected on all patients with fractures seen in the emergency department of children's hospital.
Results:
Of the 100 offices telephoned, 8 offices gave an appointment within 1 week to the child with Medicaid insurance. Thirty-six of the 100 offices gave an appointment within 1 week to the child with PPO insurance. For the 2210 pediatric fractures seen in the emergency department, the payer mix for patients presenting initially to our facility (1326 patients) was 41% Medicaid, 9% selfpay, and 50% commercial. For the patients presenting to our emergency department after being seen at an outside facility first (884 patients), the payer mix was 47% Medicaid, 13% self-pay, and 40% commercial. The percentages between these two groups were similar but did have a statistically significant difference (P=0.021).
Conclusions:
To the best of our knowledge, this is the first study that reports a majority (64/100) of orthopaedic offices in the region would not care for a child with a fracture regardless of insurance status. Consistent with earlier studies, children with Medicaid have less access to care. The similar insurance status of children sent to the emergency department from other facilities compared with those presenting directly suggests that children in this study are sent to a children's hospital for specialized care rather than for economic reasons.
Level Of Evidence:
Level II.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 11:21
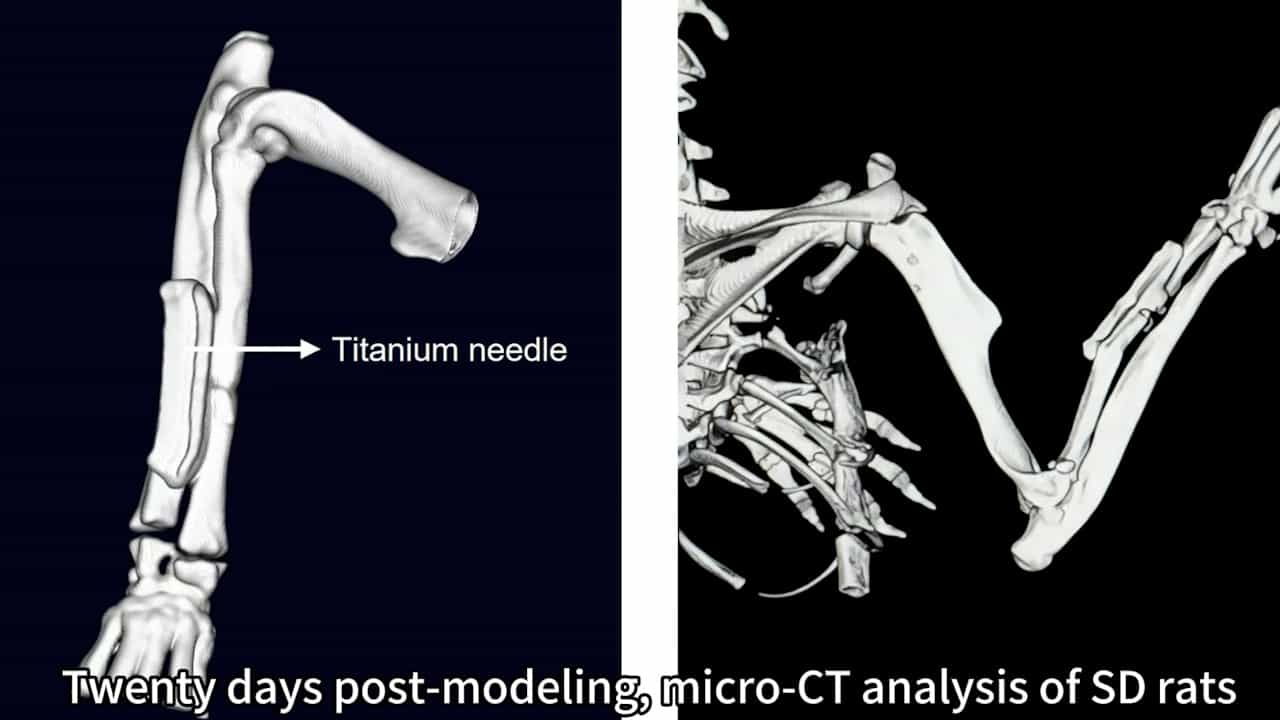
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:11
Secondary Healthcare System
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Growth of Cartilage and Bone Tissue
 01:19
Restorative Care