Related Experiment Video
Updated: Jun 14, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
[Uncomplicated and complicated myocardial peripheral blocks]
Alfredo de Micheli1, Gustavo A Medrano, Pedro Iturralde-Torres
1Instituto Nacional de Cardiología Ignacio Chávez, México.

Abstract:
Septal necrosis + peripheral left blocks. Because of an extensive septal necrosis, the manifestation of the initial ventricular activation forces decreases in the precordial leads. With left bifascicular block (LASB + LPSB), the first ventricular activation forces become more evident and the electrical signs of septal necrosis can be concealed. In the presence of a trifascicular block, the manifestation of the first ventricular electromotive forces diminishes again and the electrical signs of septal necrosis become evident once more. Small Q waves are present in leads V1 to V4. Extensive anterior necrosis + left peripheral blocks. This necrosis is manifested by QS complexes from V2 to V6. An associated left bifascicular block reduces the electrical manifestation of dead tissue: QS complexes persist only in V3 and V4. In turn, a coexisting trifascicular block causes the presence of QS complexes from V2 to V5. Posteroinferior necrosis + left peripheral blocks. Electromotive forces of the ventricular activation shift upward, due to a posteroinferior necrosis, and QS or QR complexes are recorded in leads aVF, II and III. An associated left bifascicular block displaces the main electromotive forces downward, posteriorly and to the left, due to a delay of the posteroinferior activation fronts. The ventricular complexes become positive and wider in all leads, reflecting the potential variations of the inferior portions of the left ventricle: aVF, II, III, sometimes V5 and V6. Consequently, the electrical signs of necrosis are reduced or abolished. Right ventricular peripheral blocks do not conceal the electrocardiographic signs of univentricular and biventricular dead myocardium.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 06:39
Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:28
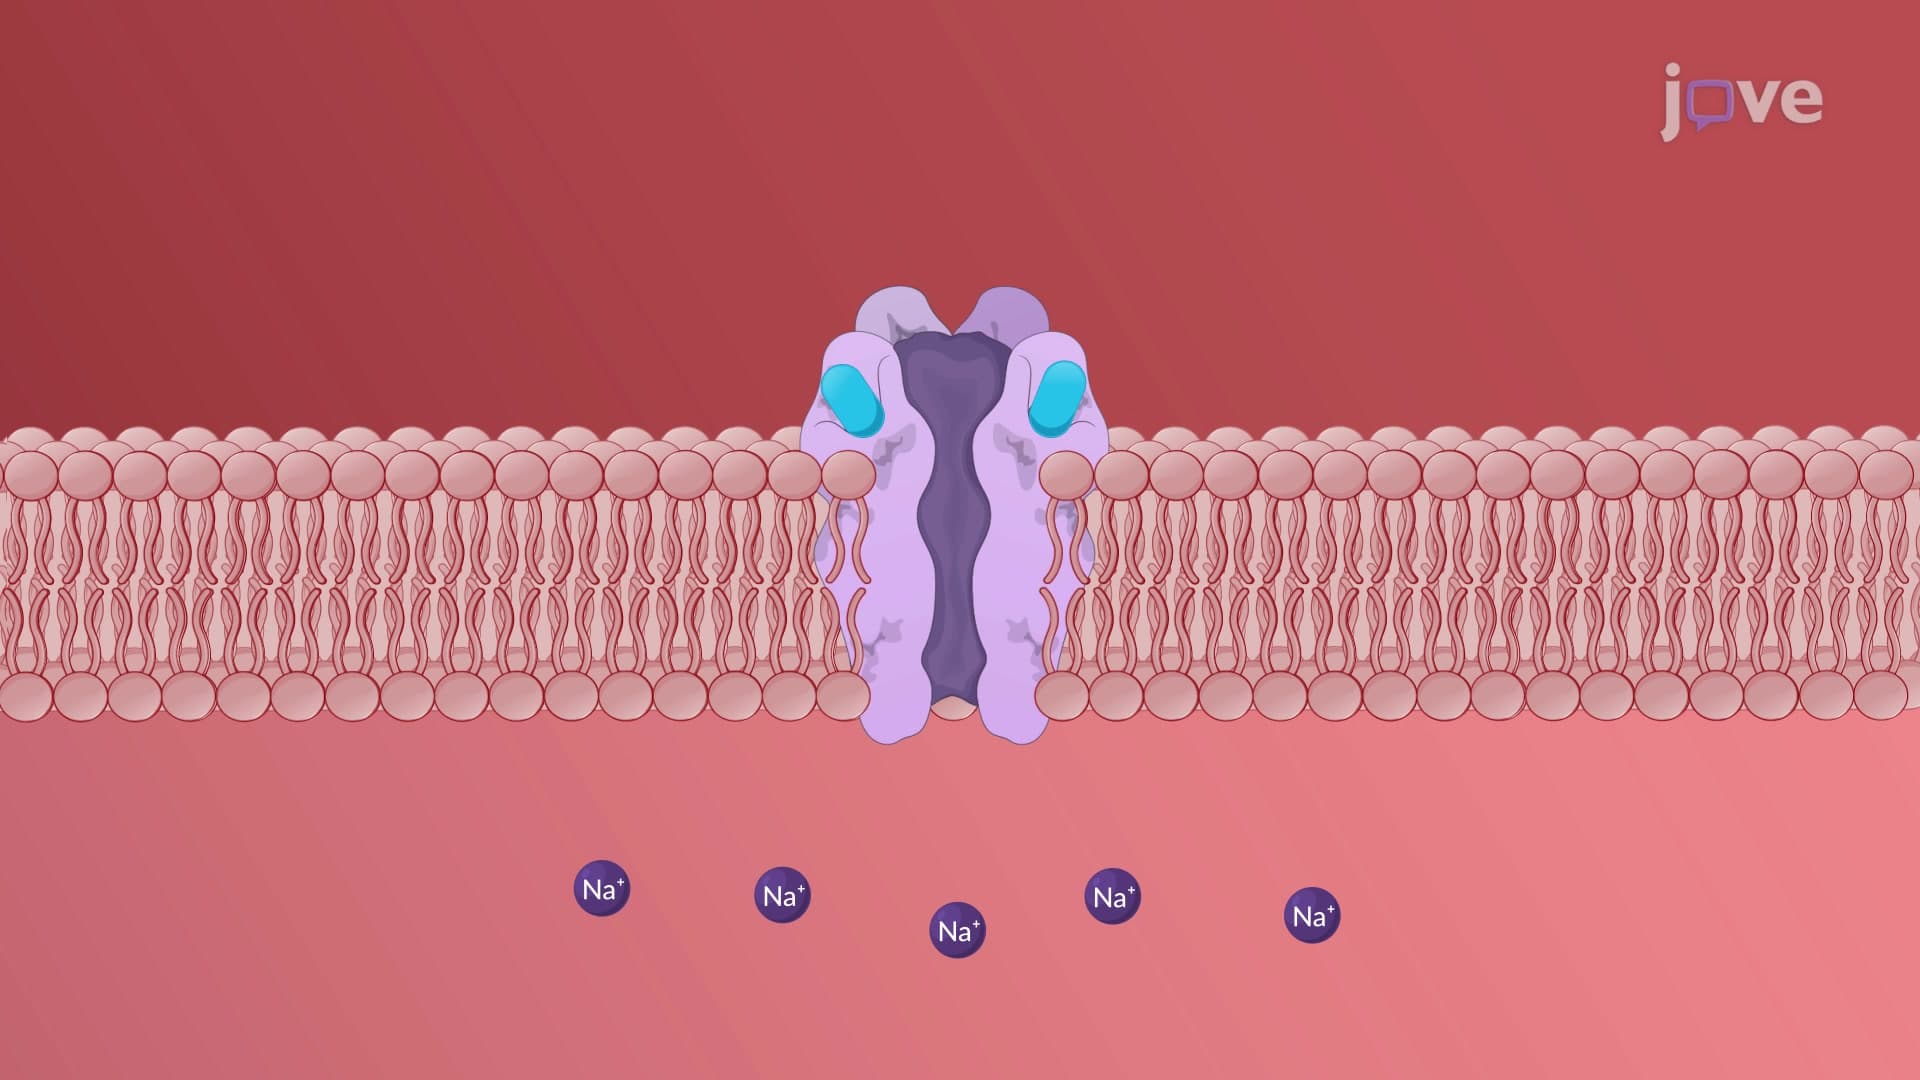
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:17
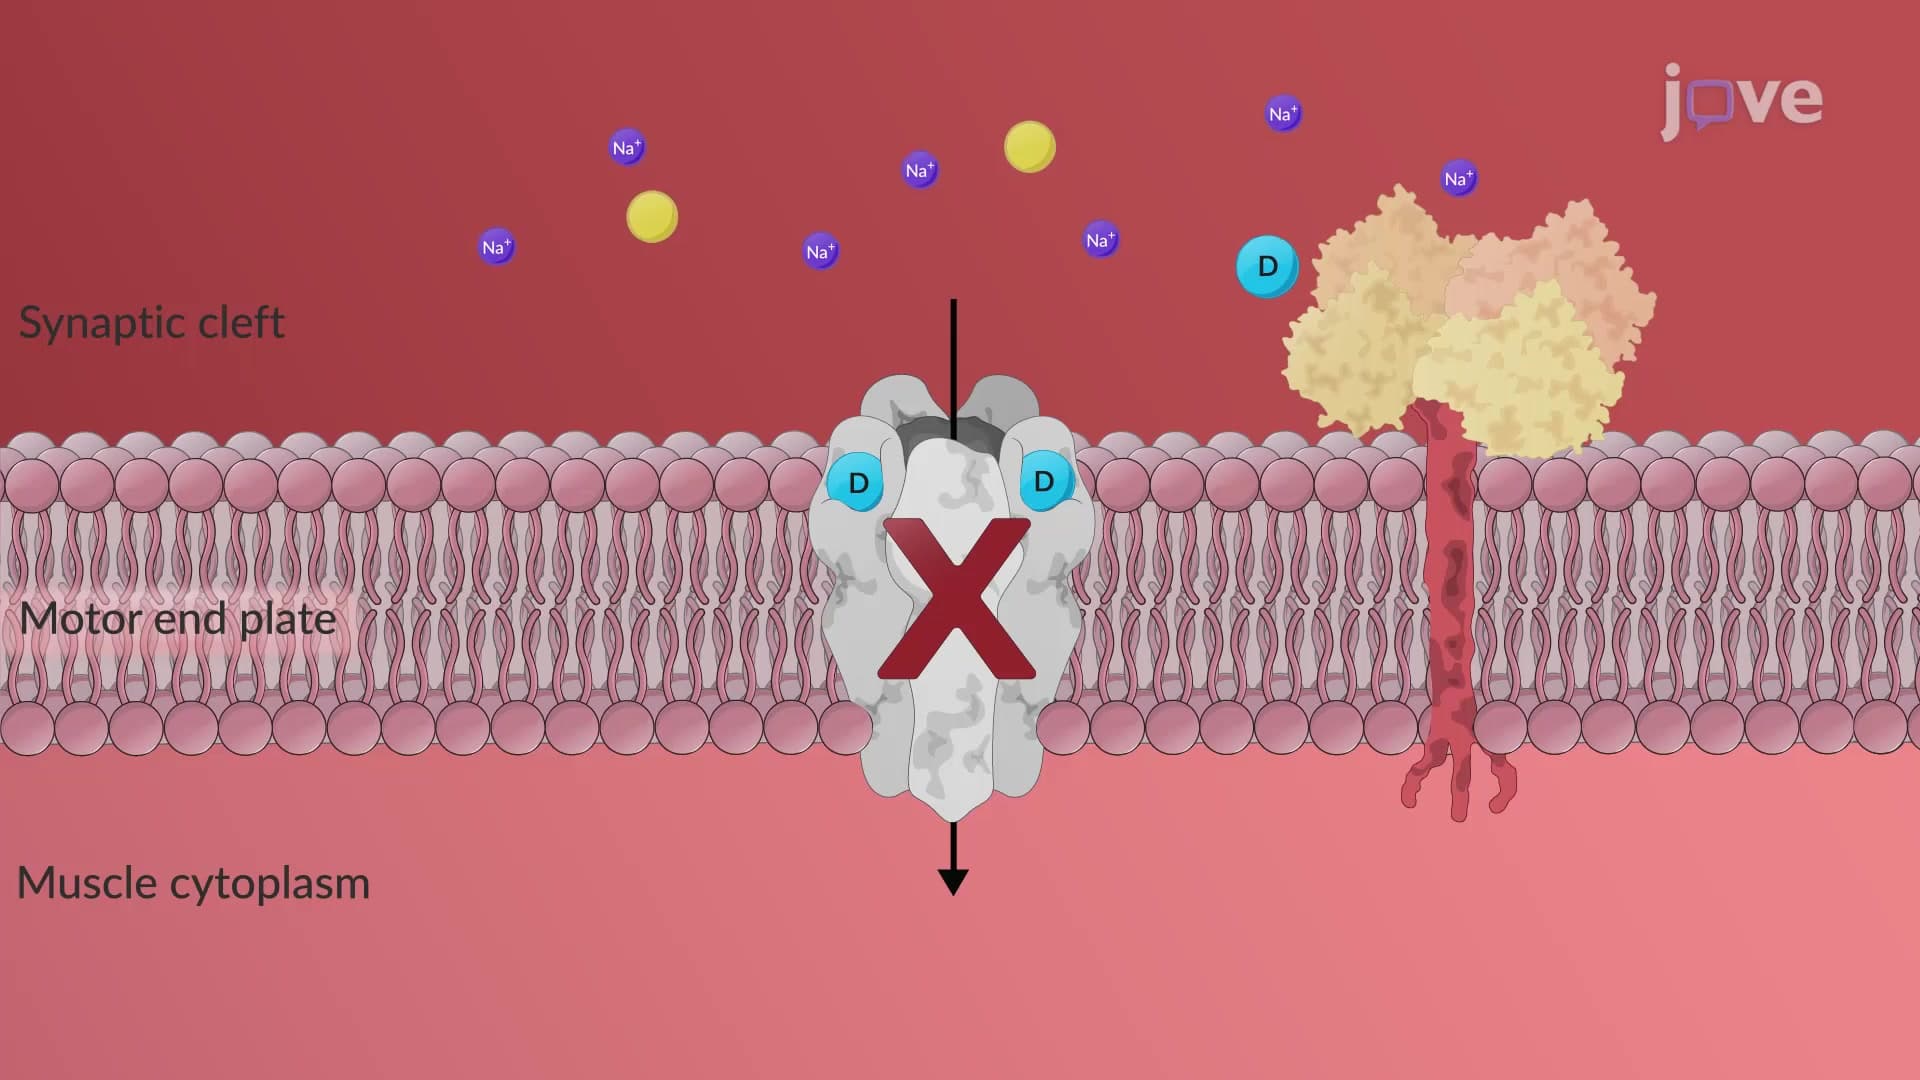
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...