Related Experiment Video
Updated: Jun 14, 2026

In Vivo Measurement of Hindlimb Dorsiflexor Isometric Torque from Pig
Published on: September 3, 2021
Deep posterior compartment strength and foot kinematics in subjects with stage II posterior tibial tendon dysfunction
Christopher Neville1, Adolph S Flemister, Jeff R Houck
1SUNY Upstate Medical University, 750 E. Adams Street, Syracuse, NY 13210, USA. nevillec@upstate.edu

Background:
Tibialis posterior muscle weakness has been documented in subjects with Stage II posterior tibial tendon dysfunction (PTTD) but the effect of weakness on foot structure remains unclear. The association between strength and flatfoot kinematics may guide treatment such as the use of strengthening programs targeting the tibialis posterior muscle.
Materials And Methods:
Thirty Stage II PTTD subjects (age; 58.1 +/- 10.5 years, BMI 30.6 +/- 5.4) and 15 matched controls (age; 56.5 +/- 7.7 years, BMI 30.6 +/- 3.6) volunteered for this study. Deep Posterior Compartment strength was measured from both legs of each subject and the strength ratio was used to compare each subject's involved side to their uninvolved side. A 20% deficit was defined, a priori, to define two groups of subjects with PTTD. The strength ratio for each group averaged; 1.06 +/- 0.1 (range 0.87 to 1.36) for controls, 1.06 +/- 0.1 (range, 0.89 to 1.25), for the PTTD strong group, and 0.64 +/- 0.2 (range 0.42 to 0.76) for the PTTD weak group. Across four phases of stance, kinematic measures of flatfoot were compared between the three groups using a two-way mixed effect ANOVA model repeated for each kinematic variable.
Results:
Subjects with PTTD regardless of group demonstrated significantly greater hindfoot eversion compared to controls. Subjects with PTTD who were weak demonstrated greater hindfoot eversion compared to subjects with PTTD who were strong. For forefoot abduction and MLA angles the differences between groups depended on the phase of stance with significant differences between each group observed at the pre-swing phase of stance.
Conclusion:
Strength was associated with the degree of flatfoot deformity observed during walking, however, flatfoot deformity may also occur without strength deficits.
Clinical Relevance:
Strengthening programs may only partially correct flatfoot kinematics while other clinical interventions such as bracing or surgery may also be indicated.
Related Concept Videos
 01:28
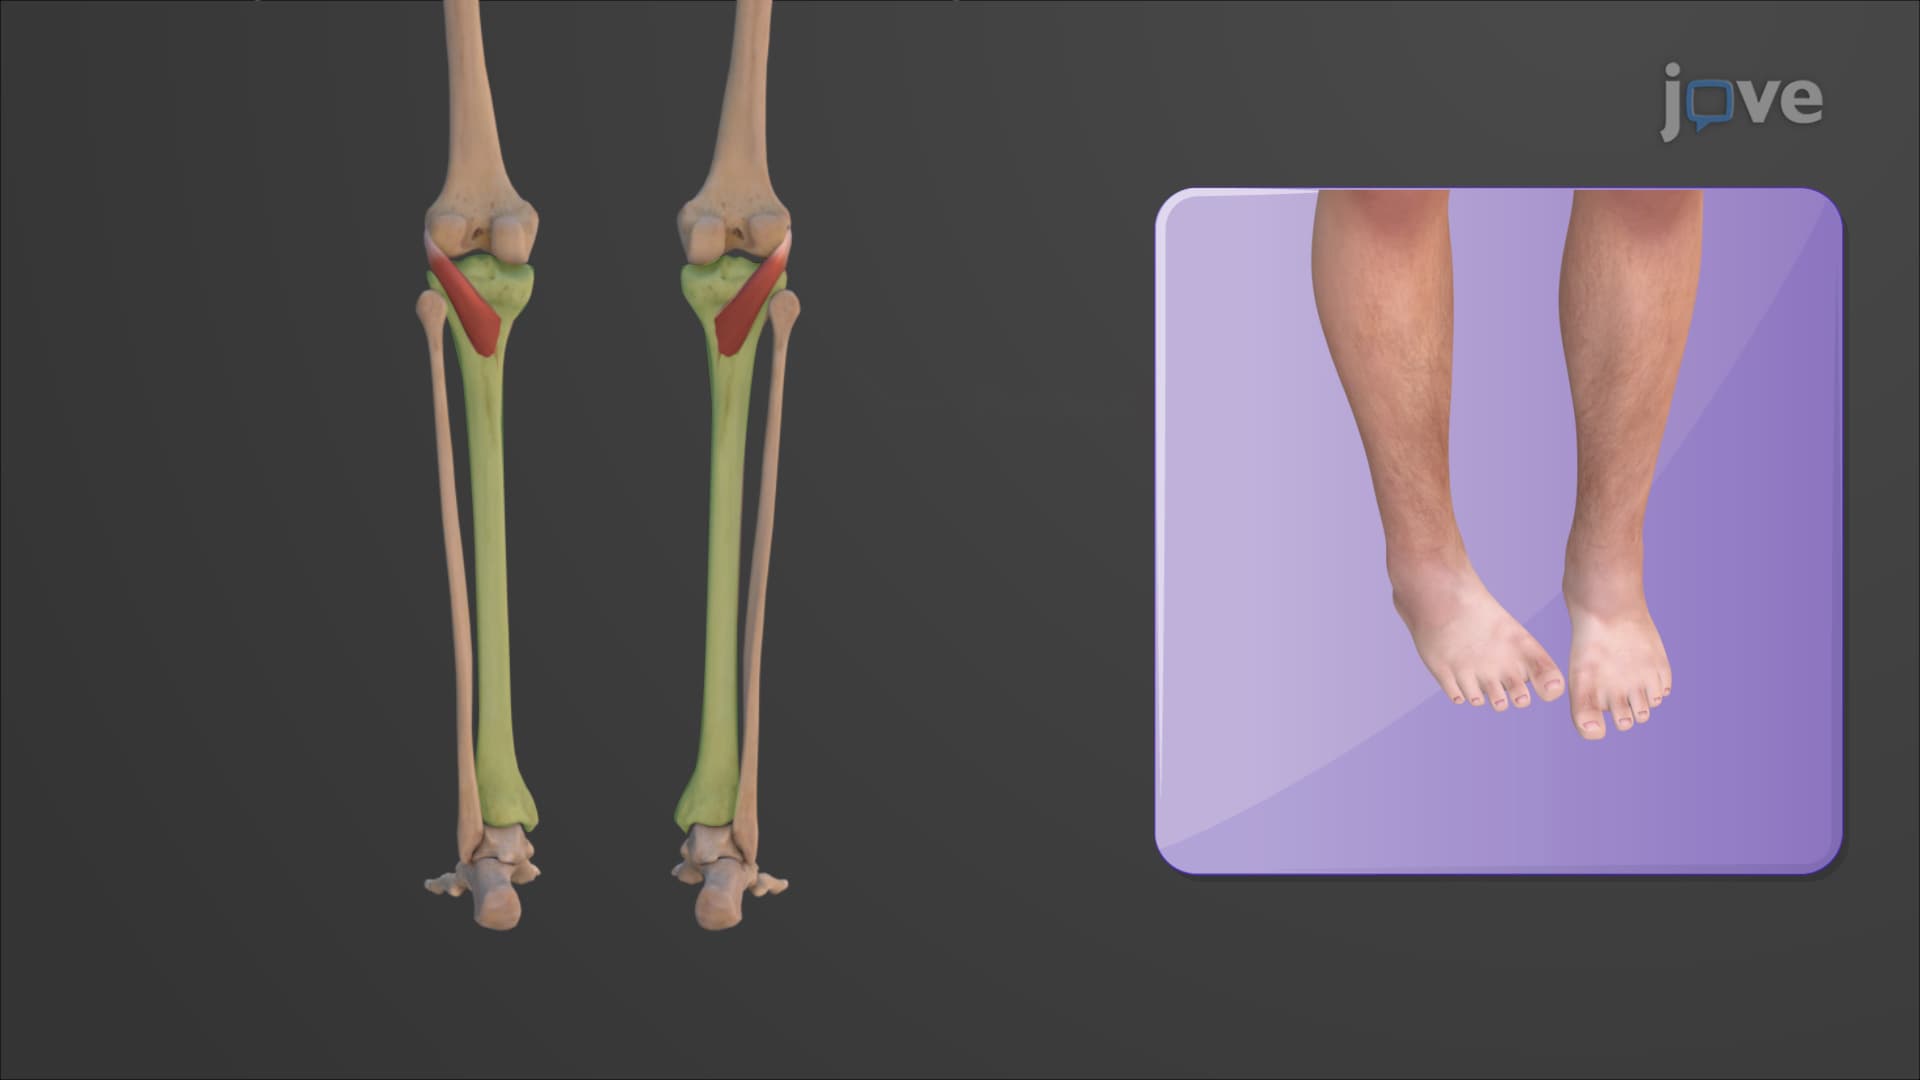
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
 01:11
Pulse Assessment Sites
 01:23
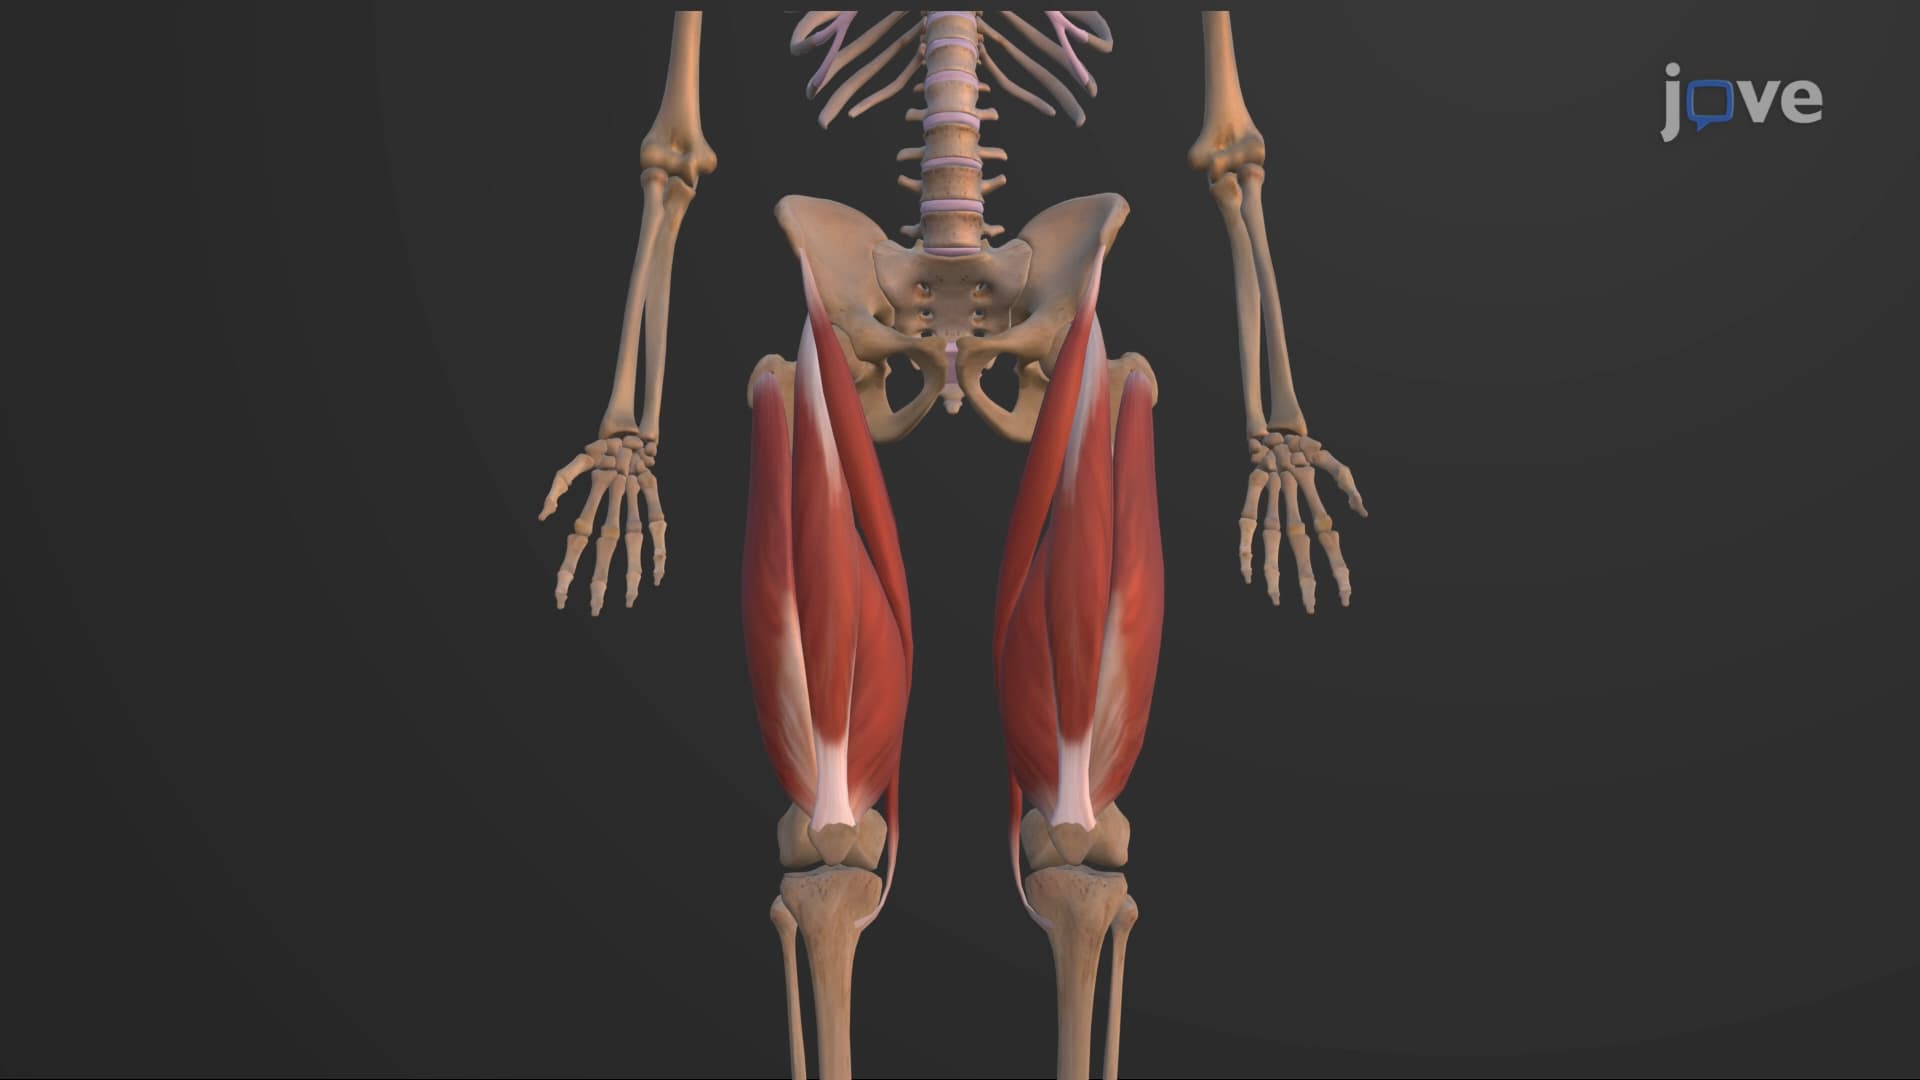
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...