Related Experiment Video
Updated: Jun 14, 2026
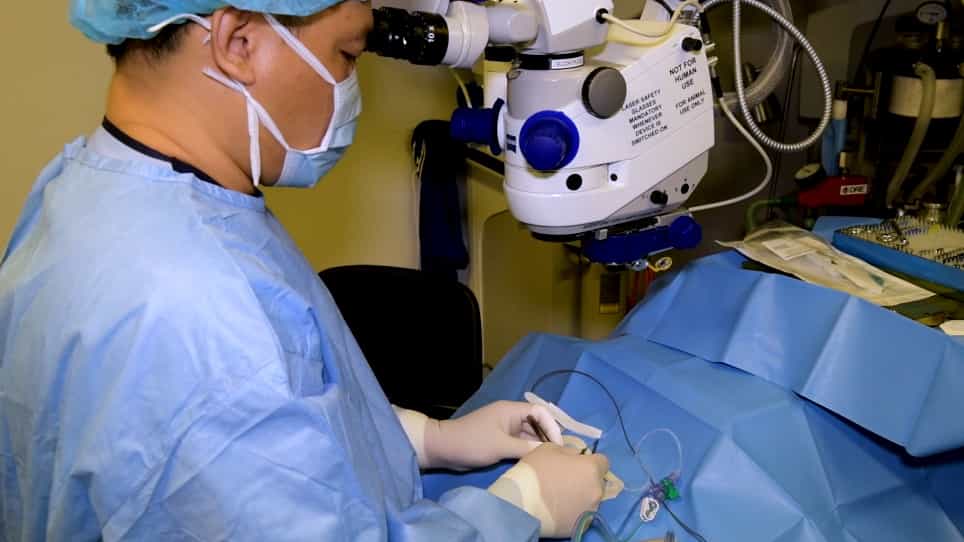

Retinal Pigment Epithelium Transplantation in a Non-human Primate Model for Degenerative Retinal Diseases
Published on: June 14, 2021
Surgical techniques for repair of primary retinal detachment: Part II. Comparison of present techniques in relation
1Department of Ophthalmology, University of Mannheim-Heidelberg, Germany. Ingrid.kreissig@medma.uni-heidelberg.de

Purpose:
To compare present surgical techniques for repair of primary retinal detachment. AIM of each technique is closing the retinal break(s), but the approach is either extraocular (e.o.) with scleral buckling or intraocular (i.o.) with pneumatic retinopexy or vitrectomy. The results are similar ranging between 94% and 99% attachment, however, the difference lies in their morbidity and socioeconomic implications which will be compared.
Material And Methods:
Literature of cerclage, minimal segmental buckling, pneumatic retinopexy and primary vitrectomy are reviewed for anatomical results, postoperative PVR, new breaks, reoperation and secondary complications jeopardizing regained visual acuity.
Results:
All 4 surgical approaches for repair of a primary retinal detachment, i.e., e.o. or i.o. procedures, have one common premise for sustained success: To find and close the break(s). This is so whether the surgery is limited to the break or extending over the entire detachment or whether it is performed as an e.o. or i.o. procedure. At present the i.o. procedures still harbour a 6-fold higher risk of postoperative PVR and 2.5-fold of reoperation. The recent SPR Study confirms that in a phakic eye postoperative visual function is statistically significant better after scleral buckling than after primary vitrectomy.
Conclusion:
Since the results after the 4 major techniques for reattaching the retina are similar, therefore, the selected procedure has to fulfill 4 postulates: (1) Retinal attachment with 1 operation, (2) it should harbour a minimum of morbidity, (3) be performed on a small budget and under local anesthesia, (4) it should provide long-term visual function, not jeopardized by secondary complications.
