Related Experiment Videos
Are there still limitations for the use of target-controlled infusion in children?
Brian J Anderson1, Bryan Hodkinson
1Department of Anaesthesiology, University of Auckland, Auckland, New Zealand. briana@adhb.govt.nz

Insights
Target controlled infusion (TCI) devices offer benefits in pediatric anesthesia, but limited pharmacokinetic data and hardware issues hinder widespread use. Further research is needed for optimal pediatric TCI application.
Area of Science:
- Anesthesiology
- Pharmacokinetics
- Pediatric Medicine
Background:
- Target controlled infusion (TCI) offers advantages in pediatric anesthesia, including rapid drug action and reduced side effects.
- Despite benefits, TCI use in children is not widespread due to several limitations.
Purpose of the Study:
- To review the reasons limiting the widespread adoption of TCI in pediatric anesthesia.
- To identify challenges in implementing TCI for pediatric patients.
Main Methods:
- Literature review examining current TCI devices and their application in pediatric anesthesia.
- Analysis of pharmacokinetic/pharmacodynamic data relevant to pediatric TCI.
Main Results:
- Lack of integrated pharmacokinetic/pharmacodynamic models for pediatric TCI across age ranges.
- Divergent pharmacokinetic parameter sets and limited validation studies for pediatric populations.
- Need for neonate-specific algorithms for advanced monitoring and challenges with intravenous induction.
Conclusions:
- Hardware limitations, insufficient pharmacokinetic/pharmacodynamic integration, and monitoring issues restrict TCI use in pediatrics.
- While intravenous induction remains a challenge, TCI is increasingly used for maintenance anesthesia in children.
Purpose Of Review:
Target controlled infusion (TCI) devices are gaining popularity among paediatric anaesthesia practitioners because propofol and short-acting opioids allow rapid onset and offset of action, reduce postoperative nausea and vomiting, reduce emergence delirium, lessen exposure to atmospheric pollutants and can be used in peripheral locations. Widespread use remains limited and this review examines reasons why children do not yet enjoy such benefits.
Recent Findings:
There is no integrated pharmacokinetic/pharmacodynamic analysis that can supply parameter estimates to be programmed into pumps for either plasma or effect-site concentration determination over the broad paediatric age range. The six pharmacokinetic parameter sets available for children out of infancy all differ. Validation studies are few. Estimates in neonates and infants are dependent on maturation and size considerations that have not yet been elucidated. There remains a need for specific neonate-derived algorithms if electroencephalogram (EEG)-derived anaesthesia depth monitors are to be used for neonates or infants. End-tidal breath analysis of propofol offers a useful tool for central compartment monitoring.
Summary:
Hardware limitations, a lack of integrated pharmacokinetic/pharmacodynamic studies and target monitoring issues restrict use. Intravenous induction remains a hurdle, but increasing familiarity with the technique guarantees continued use for maintenance anaesthesia.
Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
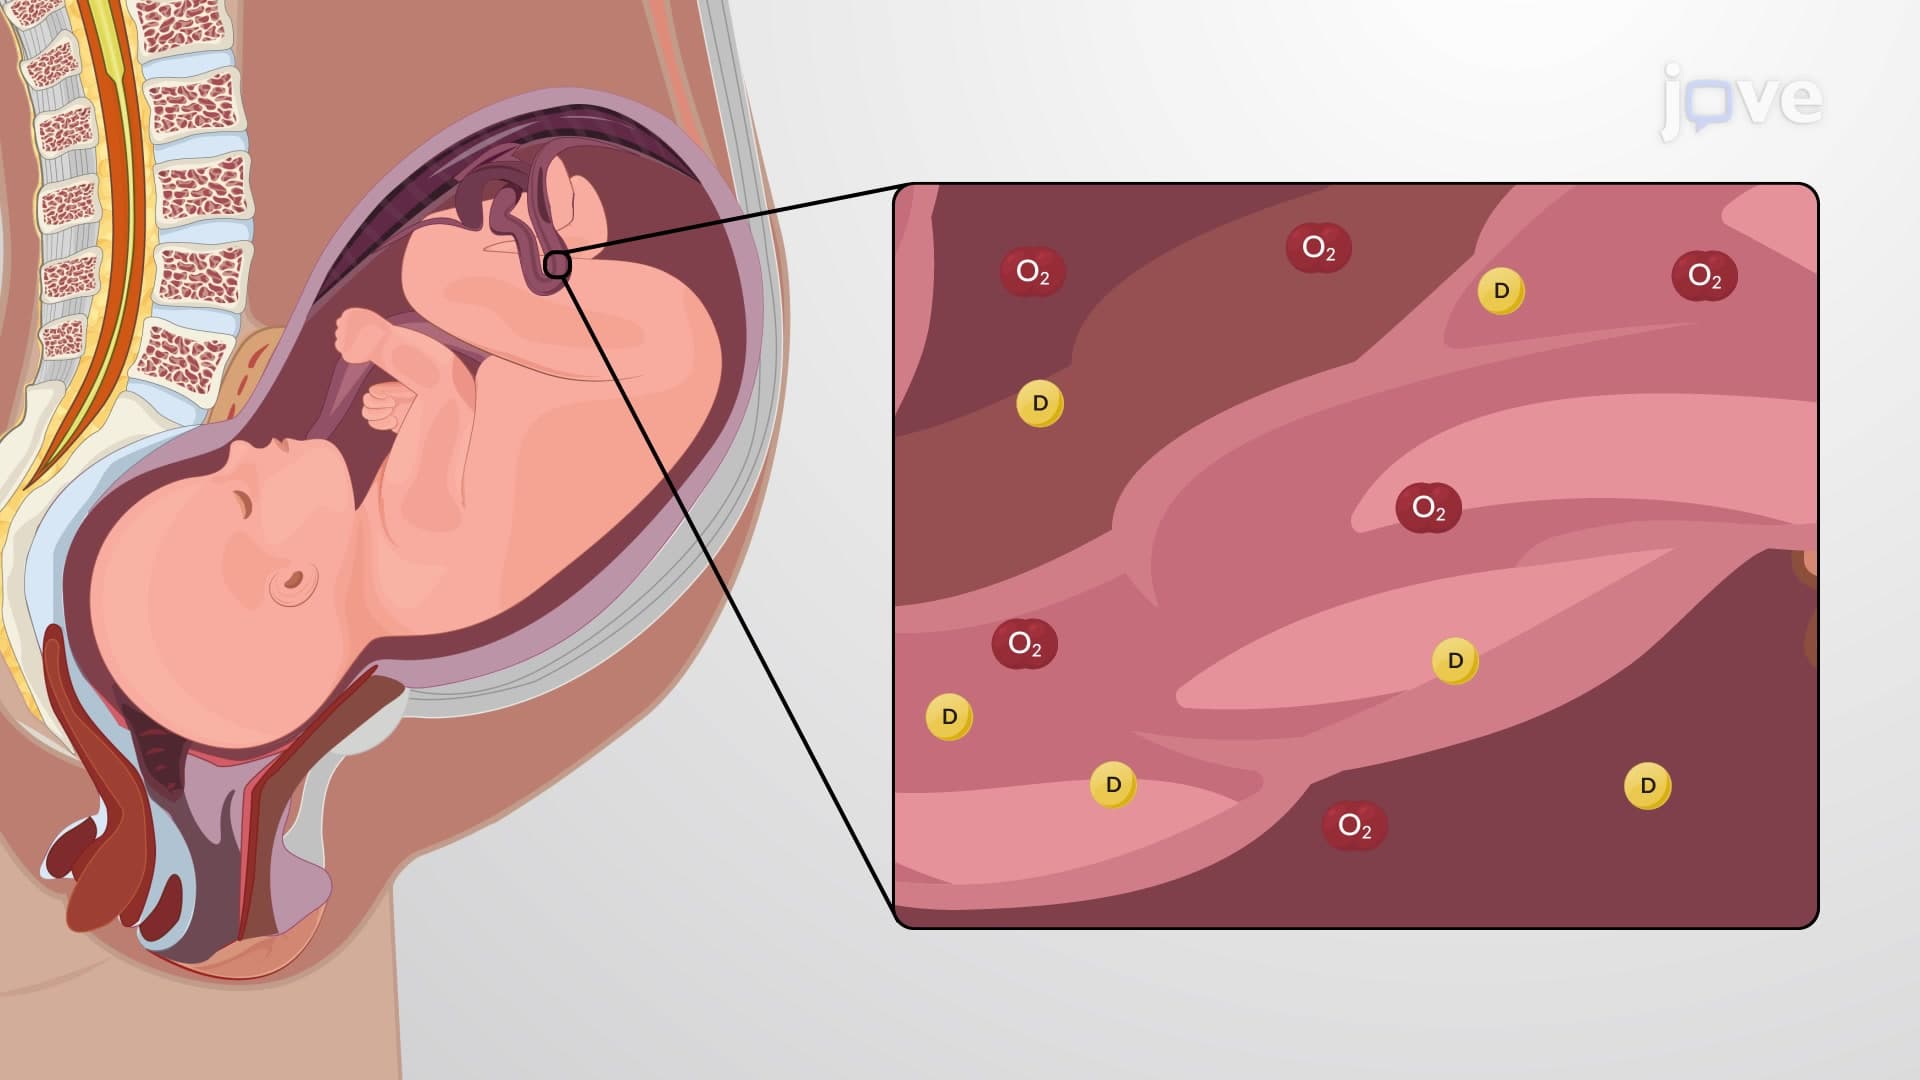 01:21
Factors Affecting Drug Response: Overview