Related Experiment Video
Updated: Jun 13, 2026


Establishment of a Mouse Severe Acute Pancreatitis Model using Retrograde Injection of Sodium Taurocholate into the Biliopancreatic Duct
Published on: April 1, 2022
[The intervention effects of different drugs on dendritic cells in acute pancreatitis in mouse]
1Department of Infectious Diseases, Beijing Friendship Hospital Affiliated to the Capital Medical University, Beijing 100050, China.

Objective:
To study the immunologic mechanism in pathogenesis of the acute pancreatitis (AP) and the intervention effects of sandostatin and magnolol.
Methods:
Ninety BALB/c mice were divided into negative control group, caerulein-induced model group, sandostatin-treatment group, magnolol-treatment group, combined sandostatin- and magnolol-treatment group by means of random number table, with 18 mice in each group. AP model was reproduced by seven intraperitoneal injections of caerulein at an interval of 1 hour. Every 30 minutes before the caerulein challenge, sandostatin was injected sub- cutaneously. Magnolol was injected intravenously immediately after the AP model was reproduced. Then at 9, 12, 24 hours after modelling, blood was drawn from orbital vein and serum was separated. Serum amylase (SA), interleukin-10 (IL-10) and gamma-interferon (IFN-gamma) were determined after the mice were sacrificed, and pancreas and spleen were harvested . The pathological changes of pancreas were observed, and the number and the ratio of myeloid- dendritic cells (MDCs) to lymphoid dendritic cells (LDCs) were measured with flow cytometry.
Results:
Compared with control group [SA (1.12 + or - 0.05) kU/L, pancreatic score (PS) 0.09 + or - 0.10], both indexes increased progressively in the model group [SA (26.11 + or - 1.96) kU/L, PS 5.32 + or - 0.19, both P<0.01]. The ratio of MDCs/LDCs showed downward tendency at every time-point especially at 9th hour (0.421 + or - 0.049 vs. 1.712 + or - 0.372, P<0.05), while the ratio of IL-10 to IFN-gamma did not show significant differences. Compared with model group, both SA and PS significantly decreased in all the three drug intervention groups [SA (kU/L): 18.25 + or - 1.09, 17.32 + or - 1.26, 17.62 + or - 0.56, PS: 4.55 + or - 0.15, 4.16 + or - 0.18, 4.10 + or - 0.13, all P<0.01]. There was no significant difference in the two ratios of MDCs/LDCs and IL-10/IFN-gamma between sandostatin-treatment group and model group. However, the ratio of MDCs/LDCs of the magnolol-treatment group was higher than that in sandostatin-treatment group 9, 12, 24 hours after modelling (9 hours: 4.694 + or - 0.527 vs. 0.819 + or - 0.182, 12 hours: 2.566 + or - 0.463 vs. 1.421 + or - 0.163, 24 hours : 2.343 + or - 0.359 vs. 1.421 + or - 0.113, P<0.05 or P<0.01). At every time-point, the ratio of IL-10/IFN-gamma in the magnolol-treatment group was significantly higher compared with the model group, and at the 12-hour point, it was higher than that of sandostatin-treatment group (8.000 + or - 1.738 vs. 3.558 + or - 0.362, P<0.05 ). The combined treatment group showed similar changes as the magnolol-treatment group.
Conclusion:
When AP occurs, the differentiation from T helper (Th0) to Th1 is augmented, while differentiation of Th0 to Th2 decreases, thus inducing an imbalance in the relationship of pro- and anti-inflammatory response. Magnolol can induce the differentiation from Th0 to Th2 by modulating the different subtype dendritic cells, thus improving the anti-inflammatory response, resulting in attenuating local and systemic inflammatory response in AP. However, sandostatin did not show such effect.

Related Concept Videos
 01:27
Acute Pancreatitis I: Introduction
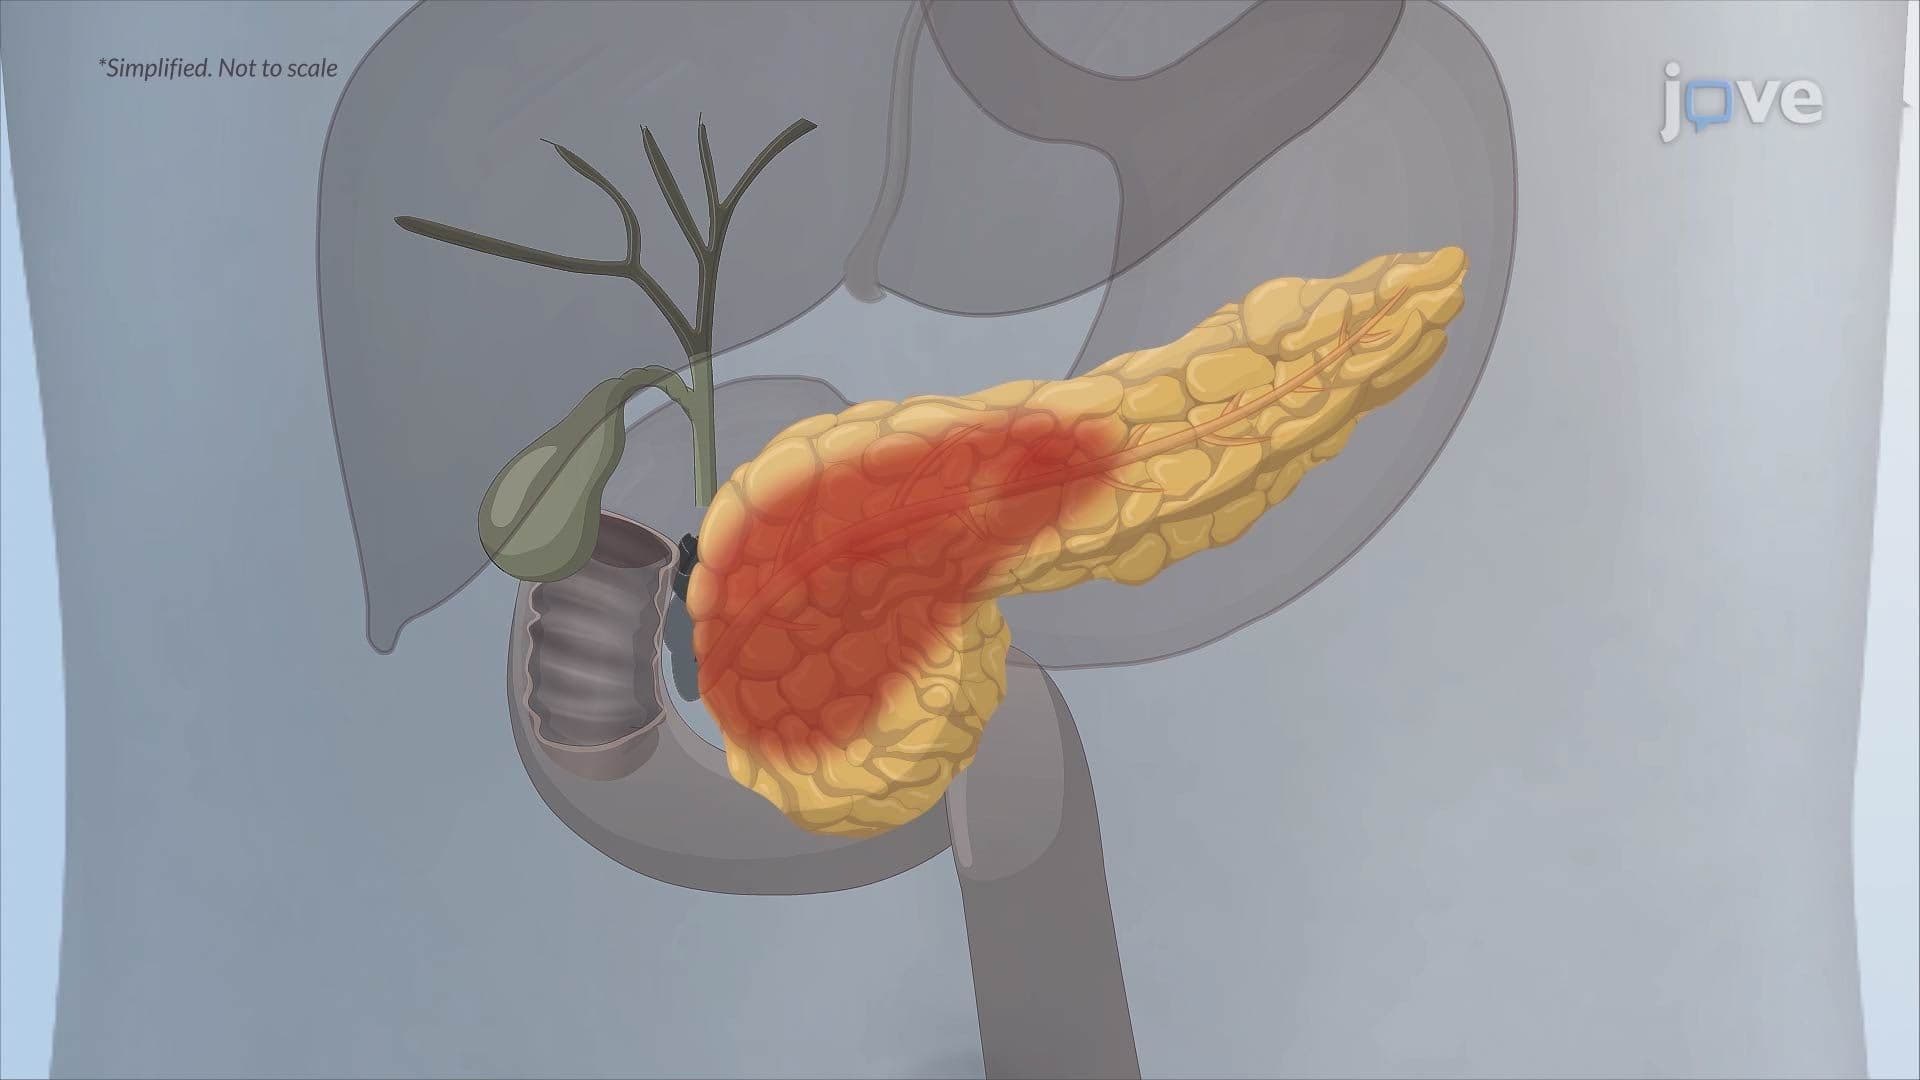
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Acute Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction