Related Experiment Video
Updated: Jun 13, 2026
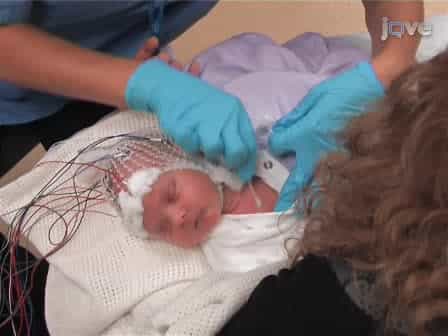

Electrophysiological Measurements and Analysis of Nociception in Human Infants
Published on: December 20, 2011
Considerations for using sucrose to reduce procedural pain in preterm infants
1Developmental Neurosciences and Child Health, Child and Family Research Institute, Vancouver, British Columbia, Canada. lholsti@cw.bc.ca

Preterm and critically ill newborns admitted to a NICU undergo repeated skin-breaking procedures that are necessary for their survival. Sucrose is rapidly becoming the accepted clinical standard nonpharmacologic intervention for managing acute procedural pain for these infants. Although shown to be safe in single doses, only 4 studies have evaluated the effects of repeated doses of sucrose over relatively short periods of time. None has examined the use of sucrose throughout the NICU stay, and only 1 study evaluated the neurodevelopmental outcomes after repeated doses of sucrose. In that study, infants born at <31 weeks' gestational age and exposed to >10 doses per day in the first week of life were more likely to show poorer attention and motor development in the early months after discharge from the NICU. Results of studies in animal models have suggested that the mechanism of action of sucrose is through opioid pathways; however, in human infants, little has been done to examine the physiologic mechanisms involved, and the findings reported thus far have been ambiguous. Drawing from the growing animal literature of research that has examined the effects of chronic sugar exposure, we describe alternative amine and hormone pathways that are common to the processing of sucrose, attention, and motor development. In addition, a review of the latest research to examine the effects of repeated sucrose on pain processing is presented. These 2 literatures each can inform the other and can provide an impetus to initiate research to examine not only the mechanisms involved in the calming mechanisms of sucrose but also in the long-term neurodevelopmental effects of repeated sucrose in those infants born extremely preterm or critically ill.
Preterm and critically ill newborns admitted to a NICU undergo repeated skin-breaking procedures that are necessary for their survival. Sucrose is rapidly becoming the accepted clinical standard nonpharmacologic intervention for managing acute procedural pain for these infants. Although shown to be safe in single doses, only 4 studies have evaluated the effects of repeated doses of sucrose over relatively short periods of time. None has examined the use of sucrose throughout the NICU stay, and only 1 study evaluated the neurodevelopmental outcomes after repeated doses of sucrose. In that study, infants born at <31 weeks' gestational age and exposed to >10 doses per day in the first week of life were more likely to show poorer attention and motor development in the early months after discharge from the NICU. Results of studies in animal models have suggested that the mechanism of action of sucrose is through opioid pathways; however, in human infants, little has been done to examine the physiologic mechanisms involved, and the findings reported thus far have been ambiguous. Drawing from the growing animal literature of research that has examined the effects of chronic sugar exposure, we describe alternative amine and hormone pathways that are common to the processing of sucrose, attention, and motor development. In addition, a review of the latest research to examine the effects of repeated sucrose on pain processing is presented. These 2 literatures each can inform the other and can provide an impetus to initiate research to examine not only the mechanisms involved in the calming mechanisms of sucrose but also in the long-term neurodevelopmental effects of repeated sucrose in those infants born extremely preterm or critically ill.
Related Concept Videos
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:24
Parenteral Anesthetics: Overview