Related Experiment Video
Updated: Jun 13, 2026

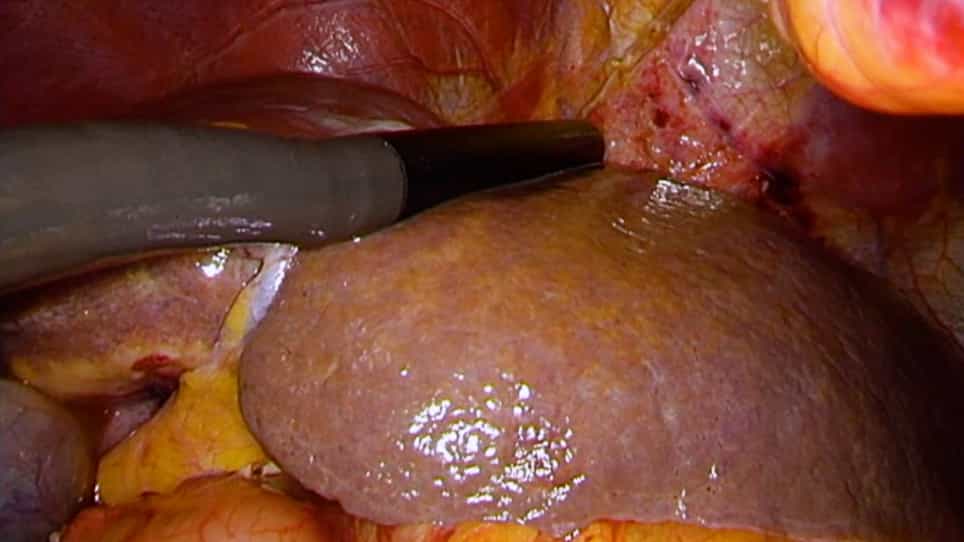
Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Isolated caudate lobe resection for hepatic tumor: surgical approaches and perioperative outcomes
Yi Wang1, Lei Y Zhang, Lei Yuan
1Eastern Hepatobiliary Surgery Hospital, Shanghai, People's Republic of China. wangyi-ehbh@163.com

Insights
Isolated caudate lobe resection (ICLR) for liver tumors is challenging but safe. Surgical approach and vascular control methods should be tailored to tumor specifics and surgeon expertise.
Area of Science:
- Hepatobiliary Surgery
- Surgical Oncology
Background:
- The caudate lobe of the liver is difficult to access due to its deep location and proximity to major blood vessels.
- Isolated caudate lobe resection (ICLR) presents significant surgical challenges.
Purpose of the Study:
- To evaluate the safety and feasibility of isolated caudate lobe resection (ICLR) for hepatic tumors.
- To analyze different surgical approaches and vascular control techniques used in ICLR.
Main Methods:
- Retrospective review of prospectively collected data from patients who underwent ICLR for hepatic tumors.
- Analysis of 46 patients with malignant (39) and benign (7) hepatic tumors.
Main Results:
- No perioperative deaths occurred in 46 patients undergoing ICLR.
- The postoperative complication rate was 8.7% (4/46), with a mean operative time of 174.5 minutes and mean blood loss of 504.4 mL.
- Various surgical approaches and vascular control methods (none, Pringle maneuver, sequential occlusion) were employed.
Conclusions:
- Isolated caudate lobe resection (ICLR) is a technically demanding yet safe surgical procedure.
- The selection of surgical strategies and vascular control techniques should be individualized based on tumor characteristics and surgeon experience.
Background:
Caudate lobe of the liver is relatively inaccessible because of its deep location and lying between the major vascular structures. Therefore, isolated caudate lobe resection (ICLR) is a much challengeable operation.
Methods:
Review of prospectively collected data from patients who underwent ICLR for hepatic tumor.
Results:
Forty-six patients (mean age 46.8 years) underwent ICLR for malignant (39 cases) and benign (7 cases) hepatic tumors. ICLRs were performed by 3 different approaches and in different ways of hepatic vascular control: without any vascular control in 7 patients, under Pringle maneuver in 26 patients, and under sequential inflow and outflow vascular occlusion in 13 patients. There were no perioperative deaths, and the postoperative complication rate was 8.7% (4/46). The mean operative time was 174.5 +/- 44.3 minutes and the mean estimated intraoperative blood loss was 504.4 +/- 356.2 mL.
Conclusions:
ICLR is a technically demanding but safe procedure. Choice of surgical approaches and ways of hepatic vascular control should be based on tumor location and surgeons'experience.