Related Experiment Video
Updated: Jun 13, 2026
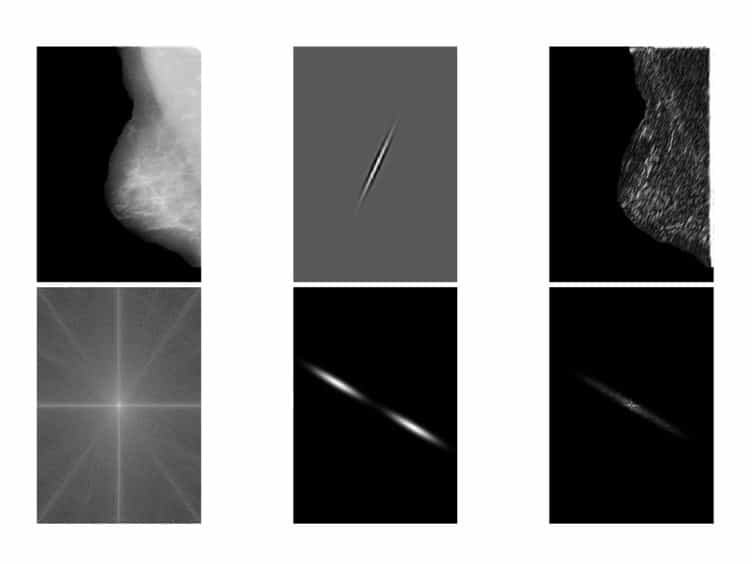

Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Identifying minimally acceptable interpretive performance criteria for screening mammography
Patricia A Carney1, Edward A Sickles, Barbara S Monsees
1Department of Family Medicine and Department of Public Health and Preventive Medicine, Oregon Health & Science University, 3181 SW Sam Jackson Park Rd, Portland, OR 97239-3098, USA. carneyp@ohsu.edu

Purpose:
To develop criteria to identify thresholds for minimally acceptable physician performance in interpreting screening mammography studies and to profile the impact that implementing these criteria may have on the practice of radiology in the United States.
Materials And Methods:
In an institutional review board-approved, HIPAA-compliant study, an Angoff approach was used in two phases to set criteria for identifying minimally acceptable interpretive performance at screening mammography as measured by sensitivity, specificity, recall rate, positive predictive value (PPV) of recall (PPV(1)) and of biopsy recommendation (PPV(2)), and cancer detection rate. Performance measures were considered separately. In phase I, a group of 10 expert radiologists considered a hypothetical pool of 100 interpreting physicians and conveyed their cut points of minimally acceptable performance. The experts were informed that a physician's performance falling outside the cut points would result in a recommendation to consider additional training. During each round of scoring, all expert radiologists' cut points were summarized into a mean, median, mode, and range; these were presented back to the group. In phase II, normative data on performance were shown to illustrate the potential impact cut points would have on radiology practice. Rescoring was done until consensus among experts was achieved. Simulation methods were used to estimate the potential impact of performance that improved to acceptable levels if effective additional training was provided.
Results:
Final cut points to identify low performance were as follows: sensitivity less than 75%, specificity less than 88% or greater than 95%, recall rate less than 5% or greater than 12%, PPV(1) less than 3% or greater than 8%, PPV(2) less than 20% or greater than 40%, and cancer detection rate less than 2.5 per 1000 interpretations. The selected cut points for performance measures would likely result in 18%-28% of interpreting physicians being considered for additional training on the basis of sensitivity and cancer detection rate, while the cut points for specificity, recall, and PPV(1) and PPV(2) would likely affect 34%-49% of practicing interpreters. If underperforming physicians moved into the acceptable range, detection of an additional 14 cancers per 100000 women screened and a reduction in the number of false-positive examinations by 880 per 100000 women screened would be expected.
Conclusion:
This study identified minimally acceptable performance levels for interpreters of screening mammography studies. Interpreting physicians whose performance falls outside the identified cut points should be reviewed in the context of their specific practice settings and be considered for additional training.
Insights
This study establishes performance benchmarks for interpreting screening mammography. Physicians falling below these criteria for sensitivity, specificity, and cancer detection rates may require additional training.
Area of Science:
- Radiology
- Medical Imaging
- Quality Improvement
Background:
- Screening mammography interpretation is crucial for early breast cancer detection.
- Establishing clear performance benchmarks is essential for maintaining high-quality diagnostic services.
- Variability in interpretation performance can impact patient outcomes and healthcare resource utilization.
Purpose of the Study:
- To define objective criteria for minimally acceptable physician performance in interpreting screening mammograms.
- To assess the potential impact of implementing these performance criteria on radiology practices in the U.S.
Main Methods:
- Utilized an Angoff approach with expert radiologists to establish performance cut points for sensitivity, specificity, recall rate, and positive predictive values (PPV).
- Phased approach involved expert consensus on performance thresholds and simulation to estimate practice impact.
- Performance measures included sensitivity, specificity, recall rate, PPV(1), PPV(2), and cancer detection rate.
Main Results:
- Defined specific cut points for minimally acceptable performance (e.g., sensitivity <75%, specificity <88% or >95%).
- Estimated that 18%-49% of interpreting physicians might fall below these thresholds, potentially requiring additional training.
- Projected that improvement to acceptable levels could lead to 14 additional cancers detected and 880 fewer false positives per 100,000 women screened.
Conclusions:
- Successfully identified minimally acceptable performance levels for screening mammography interpreters.
- Physicians performing below established cut points warrant review and consideration for further training.
- Implementation of these criteria can enhance the quality and effectiveness of mammography screening programs.

Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:14
Imaging Studies I: CT and MRI
Description of the Procedures
Computed Tomography (CT) scan:
Computed Tomography (CT) scans use X-ray technology to generate detailed images of bones, organs, and tissues. During the scan, the patient lies on a moving table...