Related Experiment Video
Updated: Jun 13, 2026
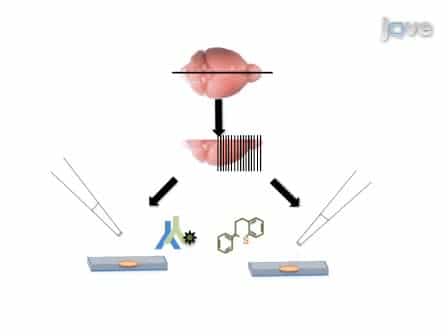

Detection of Neuritic Plaques in Alzheimer's Disease Mouse Model
Published on: July 26, 2011
Plaque deposition dependent decrease in 5-HT2A serotonin receptor in AbetaPPswe/PS1dE9 amyloid overexpressing mice
Peter Holm1, Anders Ettrup, Anders B Klein
1Neurobiology Research Unit and Center for Integrated Molecular Brain Imaging, Copenhagen University Hospital Rigshospitalet, Copenhagen, Denmark.

Abstract:
Intrahippocampal injections of aggregated amyloid-beta (Abeta)1-42 in rats result in memory impairment and in reduction of hippocampal 5-HT2A receptor levels. In order to investigate how changes in 5-HT2A levels and functionality relate to the progressive accumulation of Abeta protein, we studied 5-HT2A receptor regulation in double transgenic AbetaPPswe/PS1dE9 mice which display excess production of Abeta and age-dependent increase in amyloid plaques. Three different age-groups, 4-month-old, 8- month-old, and 11-month-old were included in the study. [3H]-MDL100907, [3H]-escitalopram, and [11C]-PIB autoradiography was performed for measuring 5-HT2A receptor, serotonin transporter (SERT), and Abeta plaque levels in medial prefrontal cortex (mPFC), prefrontal cortex (PFC), frontoparietal cortex (FPC), dorsal and ventral hippocampus, and somatosensory cortex. To investigate 5-HT2A receptor functionality, animals were treated with the 5-HT2A receptor agonist DOI and head-twitch response (HTR) subsequently recorded. Expression level of the immediate early gene c-fos was measured by in situ hybridization. We found that the age-related increase in Abeta plaque burden was accompanied by a significant decrease in 5-HT2A receptor binding in mPFC in the 11-month-old group. The changes in 5-HT2A receptor binding correlated negatively with [11C]-PIB binding and were not accompanied by decreases in SERT binding. Correspondingly, 11-month-old transgenic mice showed diminished DOI-induced HTR and reduced increase in expression of c-fos mRNA in mPFC and FPC. These observations point towards a direct association between Abeta accumulation and changes in 5-HT2A receptor expression that is independent of upstream changes in the serotonergic system.
Insights
Alzheimer's disease models show amyloid-beta plaque buildup reduces 5-HT2A receptor levels and function. This change is linked to amyloid accumulation, not serotonin transporter levels.
Area of Science:
- Neuroscience
- Pharmacology
- Alzheimer's Disease Research
Background:
- Amyloid-beta (Abeta) accumulation is central to Alzheimer's disease pathology.
- Reduced hippocampal 5-HT2A receptor levels are observed in Abeta-induced memory impairment.
Purpose of the Study:
- To investigate the relationship between progressive Abeta accumulation and 5-HT2A receptor regulation and function.
- To examine age-dependent changes in 5-HT2A receptor binding and functionality in a mouse model of Alzheimer's disease.
Main Methods:
- Utilized AbetaPPswe/PS1dE9 double transgenic mice across three age groups (4, 8, and 11 months).
- Performed autoradiography for 5-HT2A receptors, SERT, and Abeta plaques ([11C]-PIB).
- Assessed 5-HT2A receptor functionality via DOI-induced head-twitch response (HTR) and c-fos mRNA expression.
Main Results:
- Abeta plaque burden increased with age, correlating with decreased 5-HT2A receptor binding in the medial prefrontal cortex (mPFC).
- 5-HT2A receptor binding changes were negatively correlated with [11C]-PIB binding and independent of SERT levels.
- Diminished DOI-induced HTR and reduced c-fos mRNA induction were observed in older transgenic mice.
Conclusions:
- Abeta accumulation is directly associated with reduced 5-HT2A receptor expression and function.
- These changes occur independently of alterations in the upstream serotonergic system.
- Findings suggest a specific link between Abeta pathology and 5-HT2A receptor dysregulation in Alzheimer's disease progression.

Related Concept Videos
 01:23
Alzheimer Disease ll: Pathophysiology
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:29
Alzheimer Disease l: Introduction
 01:22
Alzheimer's Disease: Treatment