Related Experiment Video
Updated: Jun 13, 2026
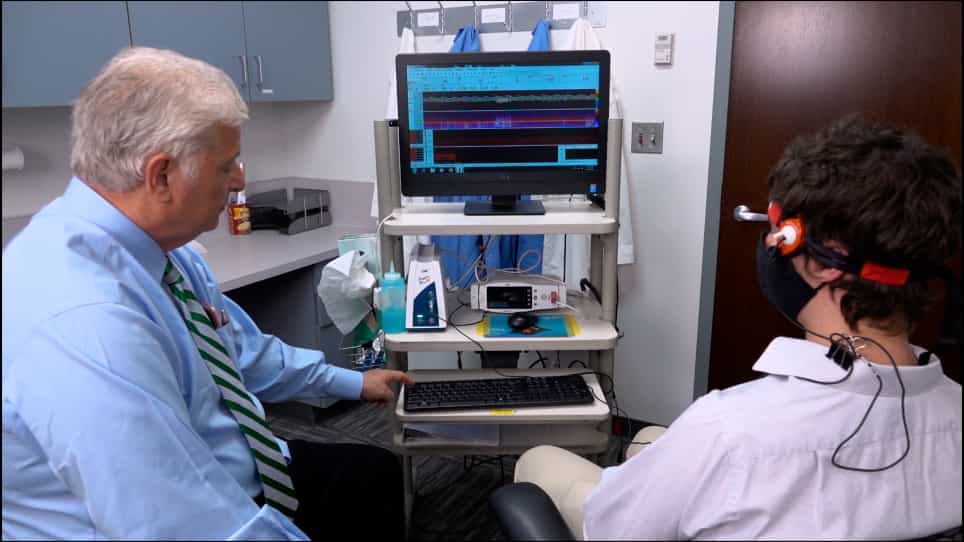
Functional Transcranial Doppler Ultrasound for Monitoring Cerebral Blood Flow
Published on: March 15, 2021
Utility of transcranial doppler in idiopathic intracranial hypertension
Gary Hunter1, Chris Voll, Michele Rajput
1Department of Neurology, University of Saskatchewan, Saskatoon, Saskatchewan, Canada.

Insights
Pulsatility index (PI) may offer a non-invasive method for monitoring idiopathic intracranial hypertension (IIH). This study found PI correlates with intracranial pressure (ICP) changes after cerebrospinal fluid withdrawal in IIH patients.
Area of Science:
- Neurology
- Neurosurgery
- Ophthalmology
Background:
- Idiopathic intracranial hypertension (IIH) poses diagnostic challenges and risks vision loss.
- Current monitoring relies on invasive, repeated lumbar punctures.
- Transcranial Doppler (TCD) pulsatility measurements show promise for assessing intracranial pressure (ICP).
Purpose of the Study:
- To evaluate the correlation between pulsatility index (PI) and ICP in newly diagnosed IIH patients.
- To determine if PI can serve as a non-invasive marker for ICP in IIH.
Main Methods:
- Seven patients with suspected IIH underwent TCD to measure PI in middle cerebral arteries.
- Cerebrospinal fluid (CSF) was withdrawn, and ICP was recorded.
- PI was re-measured post-CSF withdrawal and correlated with ICP changes.
Main Results:
- All patients presented with elevated opening ICP (average 39 cm H2O).
- PI significantly decreased after CSF withdrawal (0.95 to 0.70, p=0.02).
- The change in PI strongly correlated with the change in ICP (p=0.004).
Conclusions:
- Pulsatility index shows potential as a non-invasive tool for monitoring ICP in IIH.
- Further research with larger, blinded studies is warranted to validate PI's accuracy for IIH management.
Introduction:
Idiopathic intracranial hypertension (IIH) can be an elusive diagnosis, and poor visual outcomes may occur. Currently, the only means of accurately diagnosing and following these patients is with repeated lumbar puncture. Previous work has shown that transcranial doppler measurements of pulsatility correlate accurately with elevated intracranial pressure (ICP). This study is designed to assess whether pulsatility index (PI) correlates with ICP in patients newly diagnosed with IIH.
Methods:
Seven patients with clinical suspicion of IIH were included in this study. Clinical suspicion was based on history of recurrent headaches and papilledema. All patients had otherwise normal examinations and imaging. Middle cerebral arteries were insonated to obtain average PI values. Cerebrospinal fluid (CSF) was then withdrawn, and closing pressures were recorded. Pulsatility index values were then obtained again, within ten minutes after completing CSF withdrawal. PI values were correlated with ICP values, and pre and post CSF withdrawal values were compared.
Results:
All seven patients had elevated opening pressures (average 39 cm H2O, range 27-70). The average closing pressure after approximately 30 cc of CSF withdrawal was 11.9 cm H2O. The average PI before CSF withdrawal was 0.95, which dropped to 0.70 after CSF withdrawal (p = 0.02). The change in ICP was found to be correlated with a change in PI (p = 0.004).
Conclusions:
These findings suggest that PI may be useful for following patients with IIH non-invasively. Further study with larger groups and blinded assessments should be useful in better characterizing the accuracy of this technique.
Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:26
Transient Ischemic Attack l: Introduction