Related Experiment Video
Updated: Jun 13, 2026

Structured Motor Rehabilitation After Selective Nerve Transfers
Published on: August 15, 2019
Residual neuromuscular block: lessons unlearned. Part II: methods to reduce the risk of residual weakness
Sorin J Brull1, Glenn S Murphy
1Department of Anesthesiology, Mayo Clinic College of Medicine, 4500 San Pablo Rd., Jacksonville, FL 32224, USA. SJBrull@me.com

Abstract:
The aim of the second part of this review is to examine optimal neuromuscular management strategies that can be used by clinicians to reduce the risk of residual paralysis in the early postoperative period. Current evidence has demonstrated that frequently used clinical tests of neuromuscular function (such as head lift or hand grip) cannot reliably exclude the presence of residual paralysis. When qualitative (visual or tactile) neuromuscular monitoring is used (train-of-four [TOF], double-burst, or tetanic stimulation patterns), clinicians often are unable to detect fade when TOF ratios are between 0.6 and 1.0. Furthermore, the effect of qualitative monitoring on postoperative residual paralysis remains controversial. In contrast, there is strong evidence that acceleromyography (quantitative) monitoring improves detection of small degrees (TOF ratios >0.6) of residual blockade. The use of intermediate-acting neuromuscular blocking drugs (NMBDs) can reduce, but do not eliminate, the risk of residual paralysis when compared with long-acting NMBDs. In addition, complete recovery of neuromuscular function is more likely when anticholinesterases are administered early (>15-20 minutes before tracheal extubation) and at a shallower depth of block (TOF count of 4). Finally, the recent development of rapid-onset, short-acting NMBDs and selective neuromuscular reversal drugs that can effectively antagonize deep levels of blockade may provide clinicians with novel pharmacologic approaches for the prevention of postoperative residual weakness and its associated complications.
Related Concept Videos
 01:17
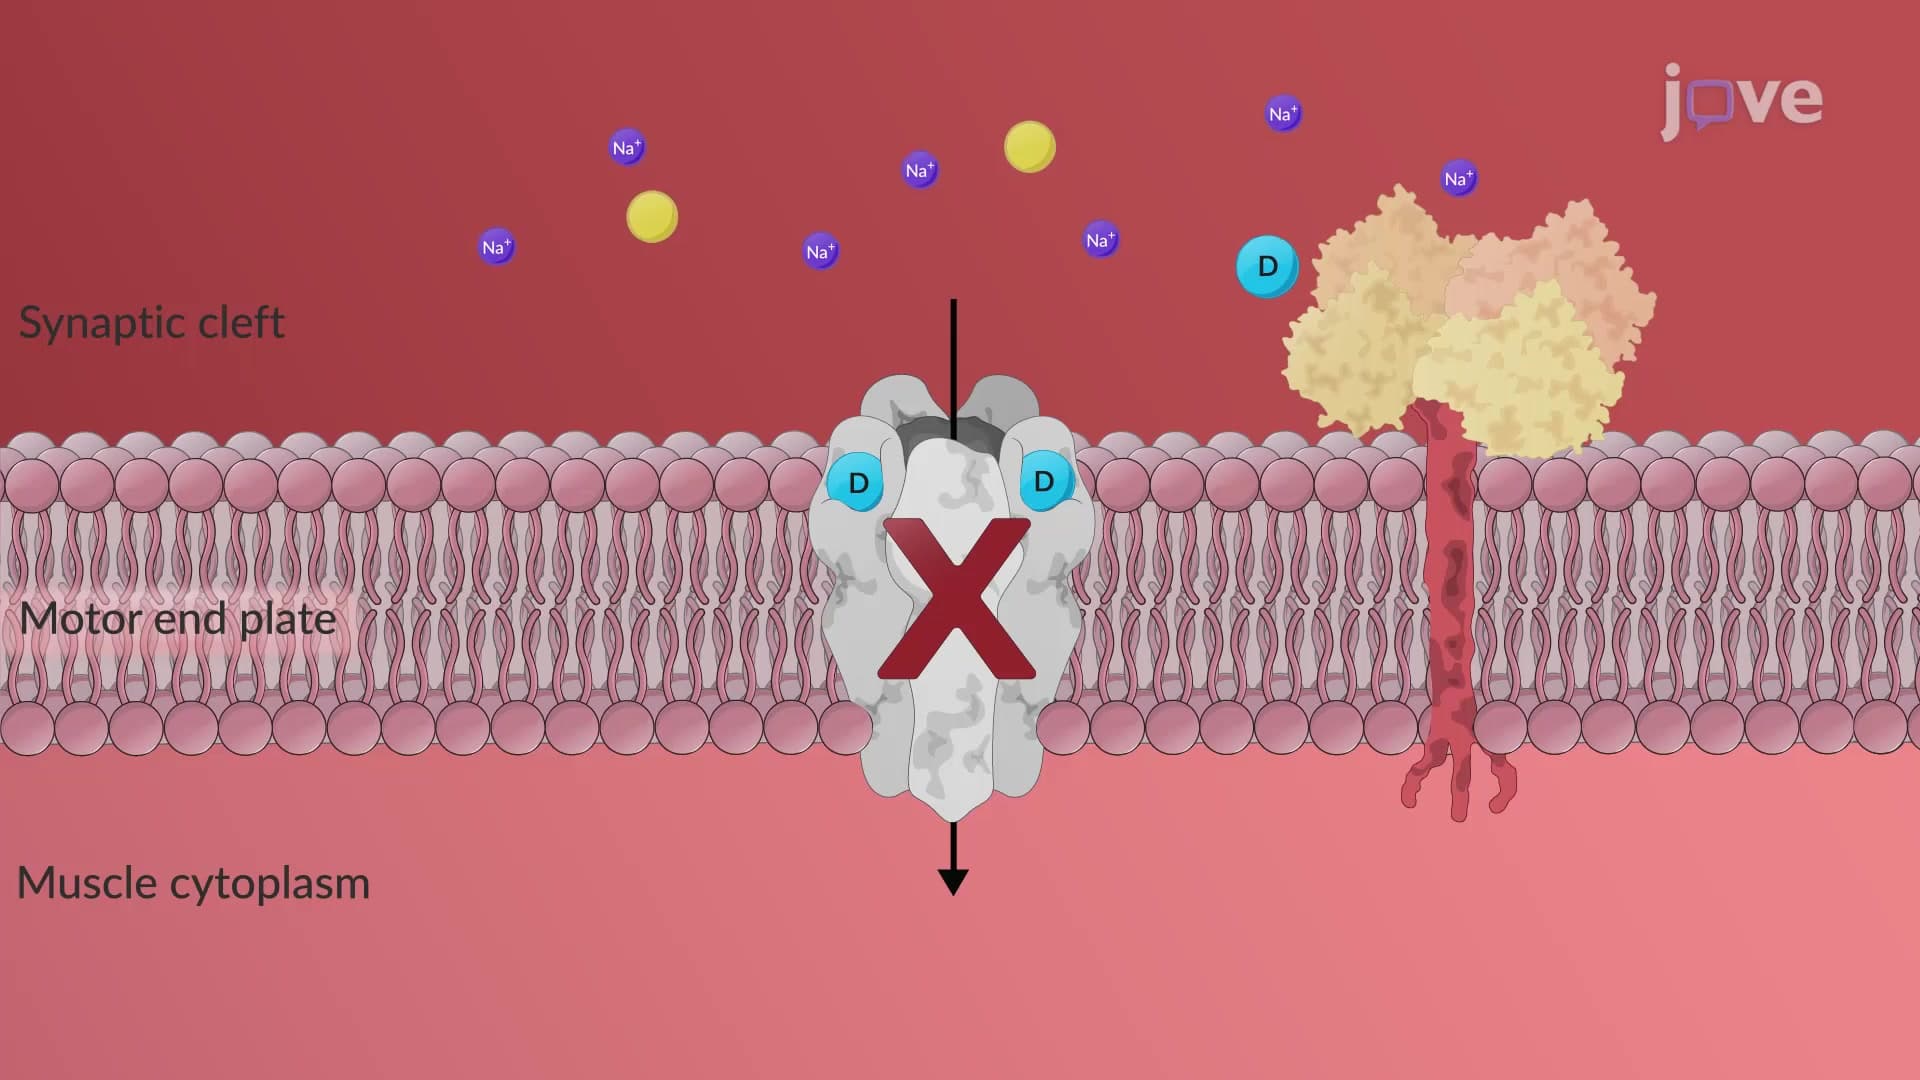
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:11
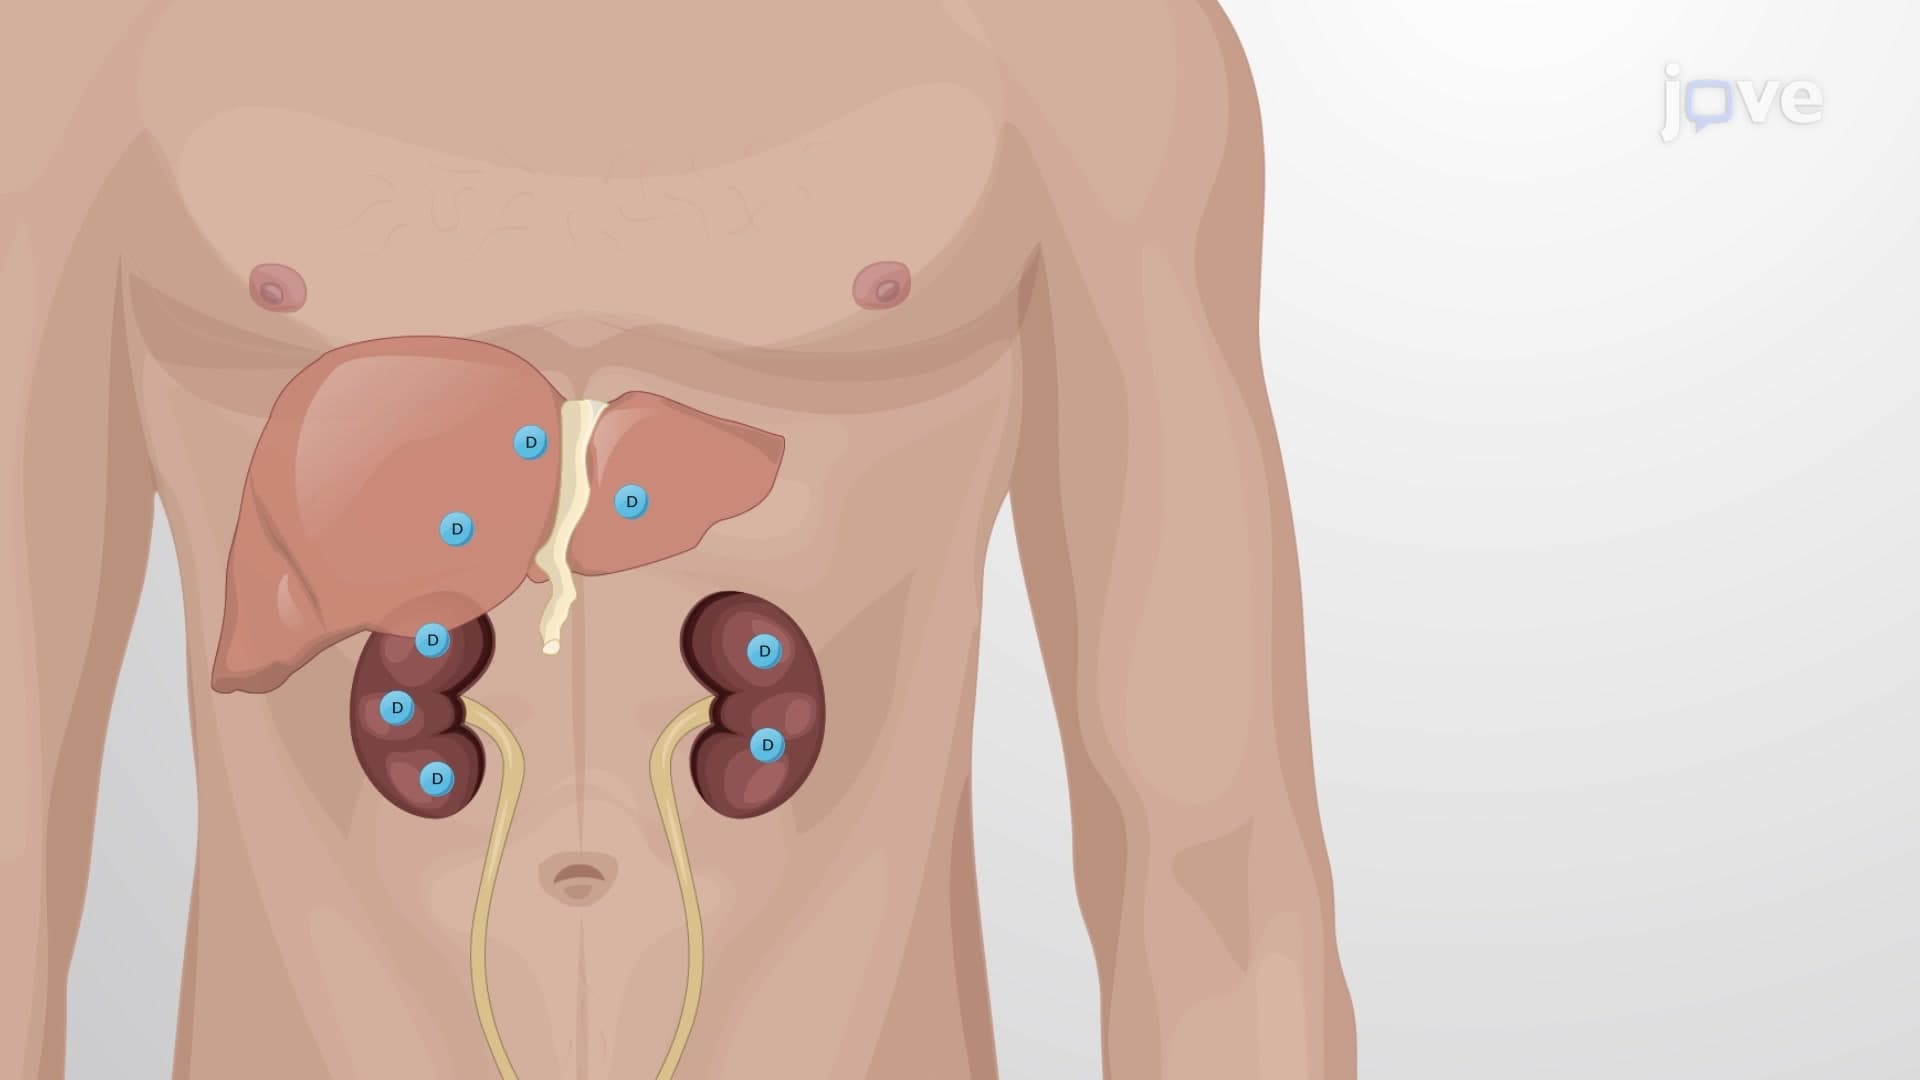
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...