Related Experiment Video
Updated: Jun 13, 2026
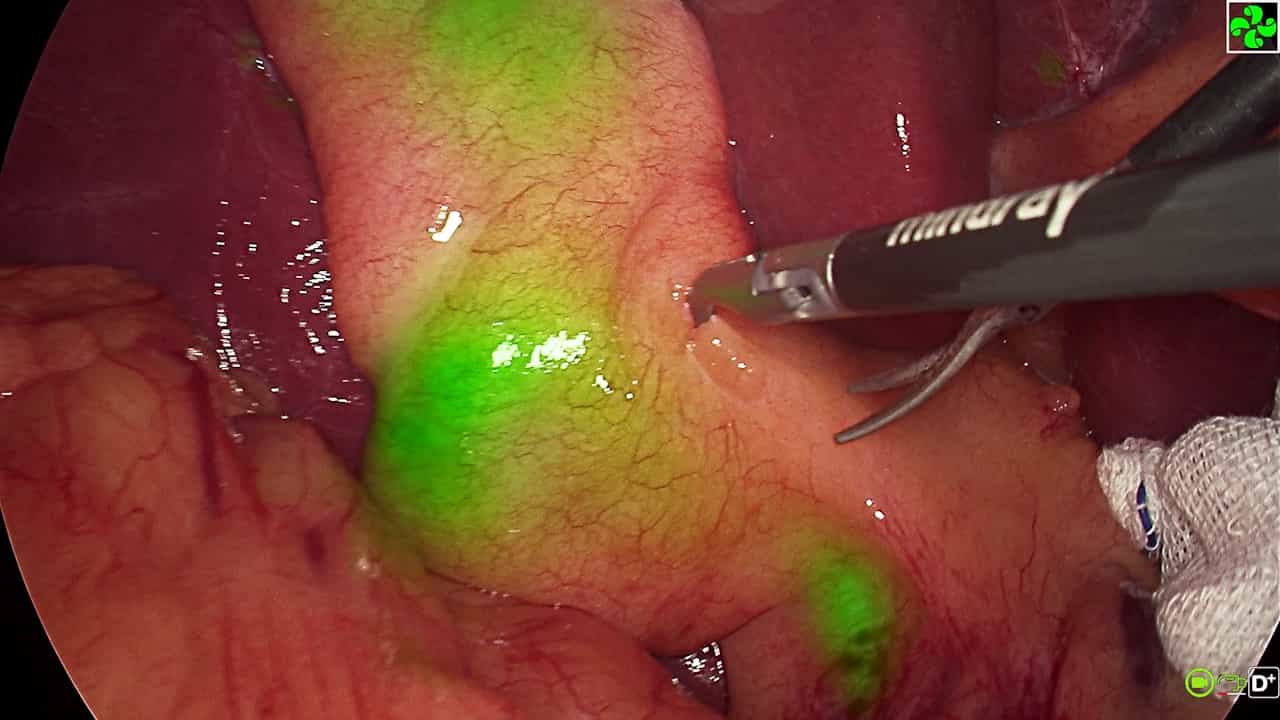

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Long-term outcome of endoscopic papillotomy for choledocholithiasis with cholecystolithiasis
Tatsuya Fujimoto1, Toshio Tsuyuguchi, Yuji Sakai
1Department of Medicine and Clinical Oncology, Chiba University Graduate School of Medicine, Japan. tatsuyafujimoto2002@yahoo.co.jp <tatsuyafujimoto2002@yahoo.co.jp>

Aim:
To assess long-term outcome of endoscopic papillotomy alone without subsequent cholecystectomy in patients with choledocholithiasis and cholecystolithiasis.
Methods:
Retrospective review of clinical records of patients treated for choledocholithiasis and cholecystolithiasis from 1976 to 2006. Of 564 patients subjected to endoscopic papillotomy and endoscopic stone extraction, 522 patients (279 men, 243 women; mean age 66.2 years) were followed up and predisposing risk factors for late complications were analyzed.
Results:
The mean duration of follow up was 5.6 years. Cholecystitis and recurrent choledocholithiasis occurred in 39 (7.5%) and 60 (11.5%) patients, respectively. Cholecystitis, including one severe case, resolved with conservative treatment. Recurrent choledocholithiasis was successfully treated endoscopically except in one case. Pneumobilia was found to be a significant risk factor for cholecystitis (P = 0.019) and recurrent choledocholithiasis (P = 0.013). Biliary tract cancer occurred in 16 patients; gallbladder cancer in 13 and bile duct cancer in three. Gallbladder cancer developed within 2 years after endoscopic papillotomy in seven of the 13 patients (53.8%).
Conclusion:
Pneumobilia was the only significant risk factor for cholecystitis and recurrent choledocholithiasis in our study population. As for the long-term outcome, it was unclear whether endoscopic papillotomy contributed to the occurrence of biliary tract cancer.
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: