Related Experiment Video
Updated: Jun 13, 2026


Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Effects of respiratory muscle work on blood flow distribution during exercise in heart failure
Thomas P Olson1, Michael J Joyner, Niki M Dietz
1Department of Internal Medicine, Division of Cardiovascular Diseases, Mayo Clinic, Rochester, MN 55905, USA.

Abstract:
Heart failure (HF) patients have a reduced cardiac reserve and increased work of breathing. Increased locomotor muscle blood flow demand may result in competition between respiratory and locomotor vascular beds. We hypothesized that HF patients would demonstrate improved locomotor blood flow with respiratory muscle unloading during activity. Ten patients (ejection fraction = 31 +/- 3%) and 10 controls (CTL) underwent two cycling sessions (60% peak work). Session 1 (S1): 5 min of normal breathing (NB), 5 min respiratory muscle unloading with a ventilator, and 5 min of NB. Session 2 (S2): 5 min NB, 5 min of respiratory muscle loading with inspiratory resistance, and 5 min of NB. Measurements included: leg blood flow (LBF, thermodilution), cardiac output (Q), and oesophageal pressure (P(pl), index of pleural pressure). S1: P(pl) was reduced in both groups (HF: 73 +/- 8%; CTL: 60 +/- 13%, P < 0.01). HF: Q increased (9.6 +/- 0.4 vs. 11.3 +/- 0.8 l min(-1), P < 0.05) and LBF increased (4.8 +/- 0.8 vs. 7.3 +/- 1.1 l min(-1), P < 0.01); CTL: no changes in Q (14.7 +/- 1.0 vs. 14.8 +/- 1.6 l min(-1)) or LBF (10.9 +/- 1.8 vs. 10.3 +/- 1.7 l min(-1)). S2: P(pl) increased in both groups (HF: 172 +/- 16%, CTL: 220 +/- 40%, P < 0.01). HF: no change was observed in Q(10.0 +/- 0.4 vs. 10.3 +/- 0.8 l min(-1)) or LBF (5.0 +/- 0.6 vs. 4.7 +/- 0.5 l min(-1)); CTL: increased (15.4 +/- 1.4 vs. 16.9 +/- 1.5 l min(-1), P < 0.01) and LBF remained unchanged (10.7 +/- 1.5 vs. 10.3 +/- 1.8 l min(-1)). These data suggest HF patients preferentially steal blood flow from locomotor muscles to accommodate the work of breathing during activity. Further, HF patients are unable to vasoconstrict locomotor vascular beds beyond NB when presented with a respiratory load.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 09:04
Skeletal Muscle Neurovascular Coupling, Oxidative Capacity, and Microvascular Function with 'One Stop Shop' Near-infrared Spectroscopy
Published on: February 20, 2018
Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:29
Pathophysiology of Cardiac Performance
 01:20
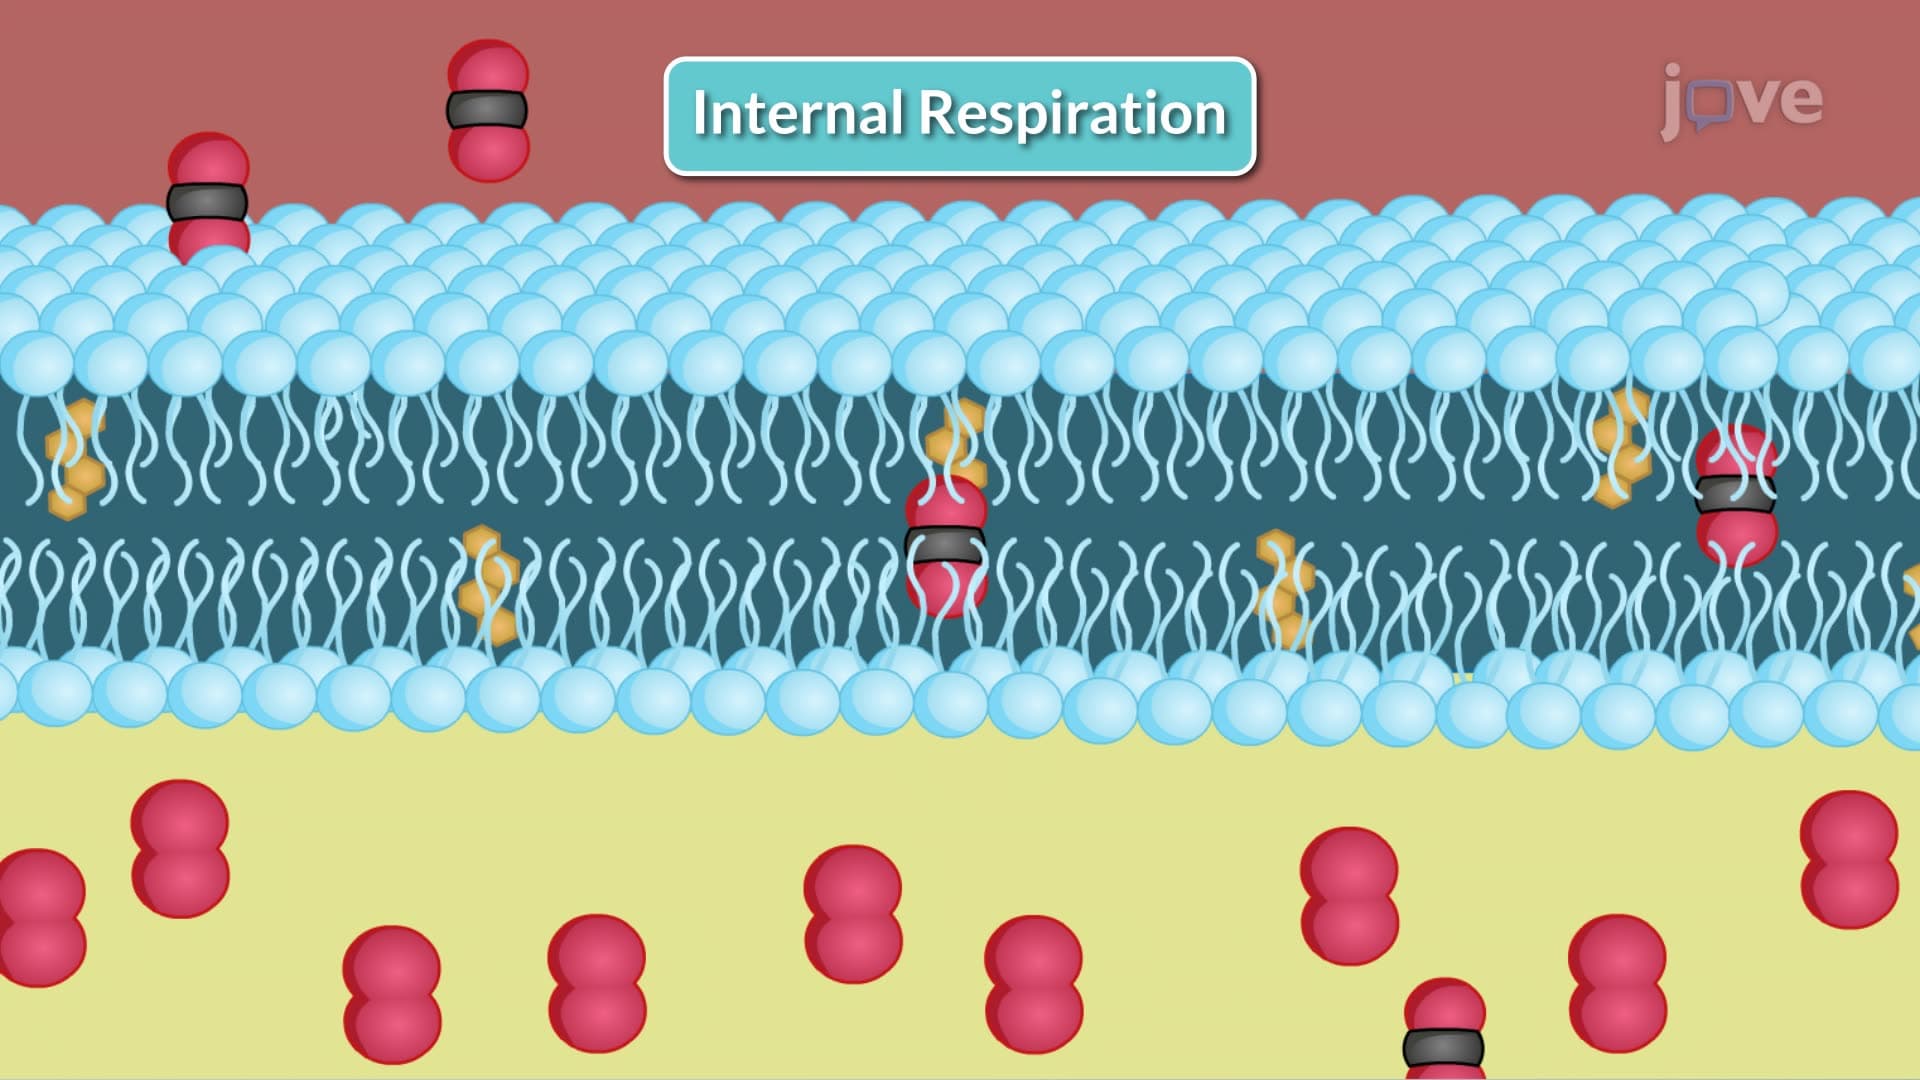
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:24
Factors Affecting Respiration
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: