Related Experiment Video
Updated: Jun 13, 2026


Comprehensive Analysis of Procoagulant Platelets Exhibiting Features of Necrosis, Apoptosis and Platelet Activation
Published on: May 23, 2025
[Antiphospholipid syndrome with autoimmune hemolytic anemia which mimics thrombotic thrombocytopenic purpura]
Naoki Karasawa1, Yasuhiro Taniguchi, Tomonori Hidaka
1Division of Gastroenterology and Hematology, Department of Internal Medicine, Faculty of Medicine, University of Miyazaki.

A 67-year-old woman was admitted to the hospital for lethargy, fever, hemolytic anemia, thrombocytopenia, and consciousness disturbance. Direct Coombs test was positive, and anti-cardiolipin beta2-glycoprotein I antibody was detected. She was diagnosed with antiphospholipid syndrome complicated with autoimmune hemolytic anemia (AIHA). She demonstrated variable consciousness disturbance, inability to distinguish right from left, dysgraphia and dyscalculia. Multiple cerebral infarctions, especially dominant cerebral hemisphere infarctions, were observed on magnetic resonance imaging. A ventilation-perfusion scan demonstrated the presence of a ventilation-perfusion mismatch in both lung fields, and multiple veinous embolisms in the right femoral, bilateral the great saphenous and popliteal veins. Therefore, pulmonary embolism and thrombophlebitis were diagnosed. Based on these findings, it was necessary to distinguish this diagnosis from thrombotic thrombocytopenic purpura (TTP). As ADAMTS-13 activity was within the normal range, TTP was denied. Thereafter, the patient was treated with 1 mg/kg of prednisolone for AIHA, 3 mg of warfarin, and 3500 units of low-molecular-weight heparin for thrombosis, and her condition improved.
A 67-year-old woman was admitted to the hospital for lethargy, fever, hemolytic anemia, thrombocytopenia, and consciousness disturbance. Direct Coombs test was positive, and anti-cardiolipin beta2-glycoprotein I antibody was detected. She was diagnosed with antiphospholipid syndrome complicated with autoimmune hemolytic anemia (AIHA). She demonstrated variable consciousness disturbance, inability to distinguish right from left, dysgraphia and dyscalculia. Multiple cerebral infarctions, especially dominant cerebral hemisphere infarctions, were observed on magnetic resonance imaging. A ventilation-perfusion scan demonstrated the presence of a ventilation-perfusion mismatch in both lung fields, and multiple veinous embolisms in the right femoral, bilateral the great saphenous and popliteal veins. Therefore, pulmonary embolism and thrombophlebitis were diagnosed. Based on these findings, it was necessary to distinguish this diagnosis from thrombotic thrombocytopenic purpura (TTP). As ADAMTS-13 activity was within the normal range, TTP was denied. Thereafter, the patient was treated with 1 mg/kg of prednisolone for AIHA, 3 mg of warfarin, and 3500 units of low-molecular-weight heparin for thrombosis, and her condition improved.
More Related Videos


Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:01
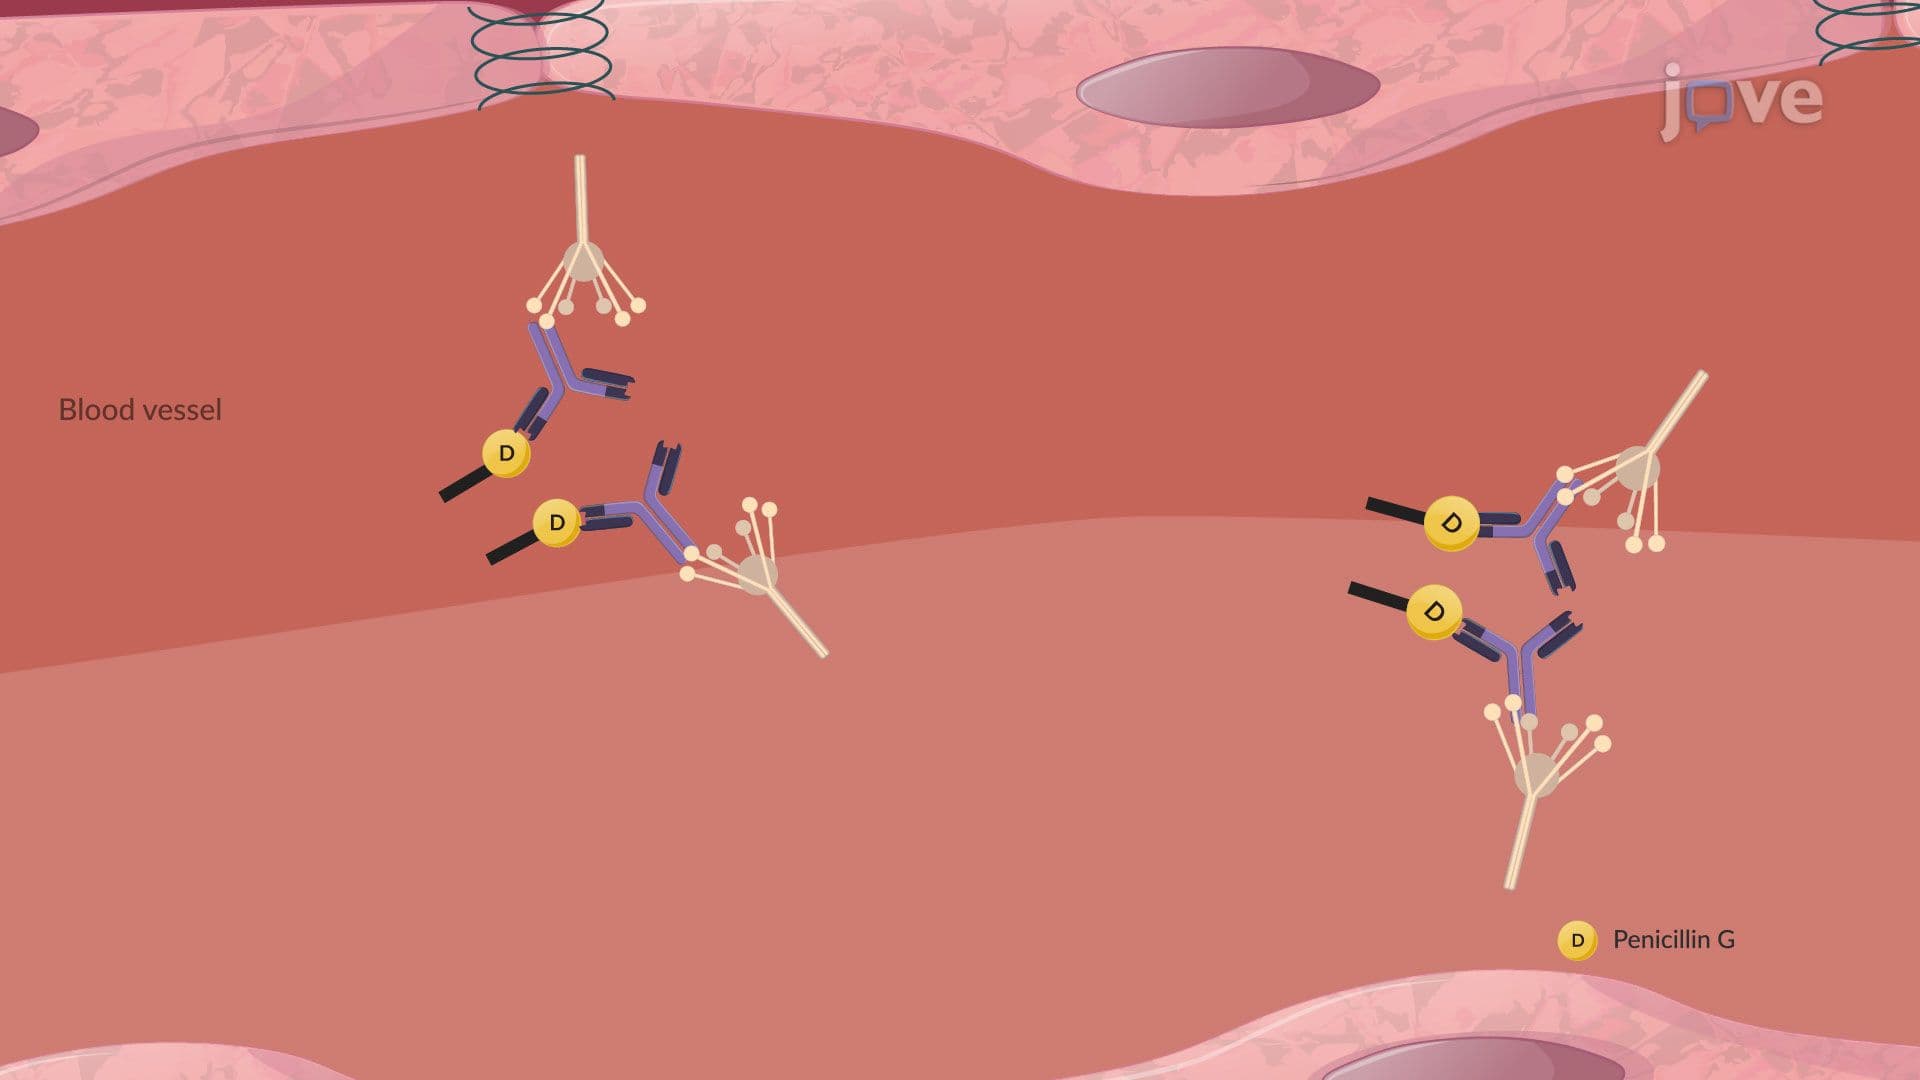
Hypersensitivity Reactions: Cytolytic Reactions
 01:30
Peripheral Artery Disease I: Introduction
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:30
Venous Thrombosis I: Introduction
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.