Related Experiment Video
Updated: Jun 13, 2026
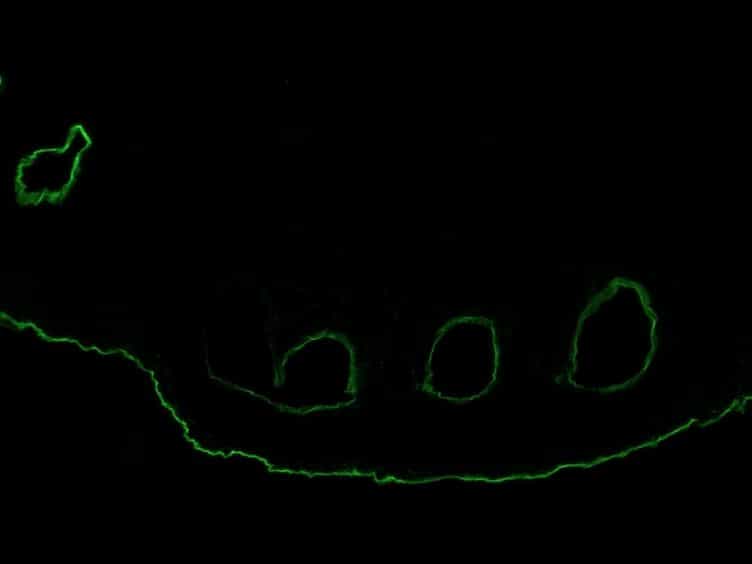
Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
The role of therapeutic plasma exchange in pemphigus vulgaris
1Department of Dermatology, Sheba Medical Center, Affiliated to Sackler Faculty of Medicine, Tel Aviv University, Tel Aviv, Israel. lior115@gmail.com

Background:
The treatment of pemphigus, an autoimmune bullous disease, is based on the combination of corticosteroids and adjuvant therapies, such as immunosuppressive drugs, anti-inflammatory drugs and immunomodulatory procedures, such as intravenous immunoglobulin and therapeutic plasma exchange (TPE).
Objective:
This study aims to assess our experience with TPE as a steroid-sparing modality in moderate and severe intractable pemphigus patients.
Methods:
A retrospective evaluation for all intractable pemphigus patients treated by TPE in a university-affiliated tertiary referral medical centre between the years 1998 and 2008. Treatment protocol included three TPE treatments weekly for 1-3 months, combined with monthly pulse therapy of dexamethasone and/or cyclophosphamide. Maintenance therapy was based on once/bi weekly TPE treatments or monthly intravenous immunoglobulin.
Results:
Seven patients were included in the study, four with severe pemphigus vulgaris and three with moderate disease. Six of the seven patients responded to TPE: Four patients (57%) achieved complete remission and two patients (28%) achieved partial remission on minimal therapy. Mild adverse effects related to TPE were observed in two patients and included dizziness and mild headache.
Conclusion:
TPE is a well-tolerated effective steroid-sparing agent in recalcitrant pemphigus patients.

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:19
Clinical Applications of Epidermal Stem Cells
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations: