Related Experiment Video
Updated: Jun 12, 2026
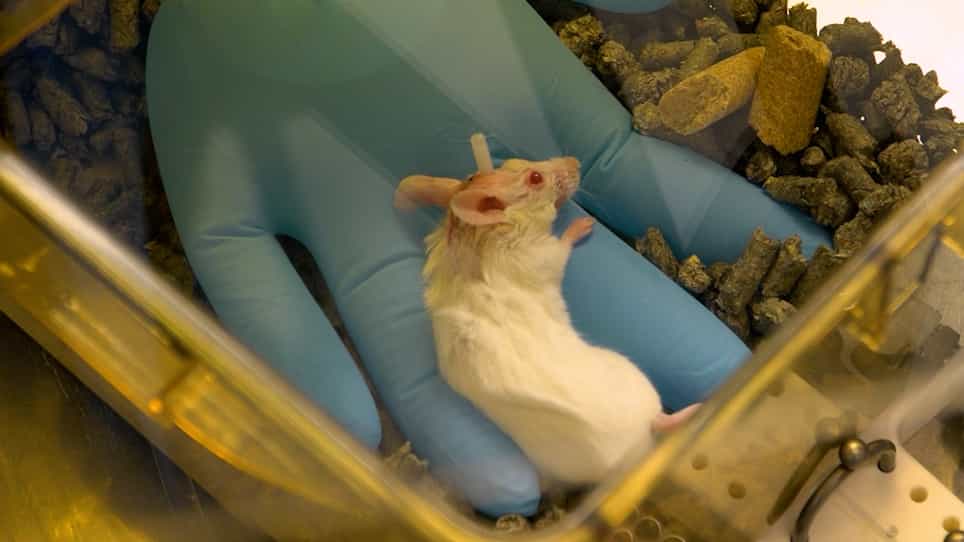

A Murine Ommaya Xenograft Model to Study Direct-Targeted Therapy of Leptomeningeal Disease
Published on: January 29, 2021
Can leptomeningeal myelomatosis be predicted in patients with IgD multiple myeloma?

Abstract:
Involvement of the central nervous system (CNS) by multiple myeloma (MM) is rare. Immunoglobulin D (IgD) MM represents only 1% to 2% of all MM patients. Previous reports show a disproportionate number of patients with IgD MM with leptomeningeal myelomatosis (LMM). Several biological markers have been associated with LMM. The development of LMM in a woman with IgD MM is reported. Our patient should be considered as having a high-risk of CNS disease based on: (i) presence of IgD-lambda MM; (ii) high myeloma burden (stage III); (iii) additional extramedullary disease; (iv) presence of circulating plasma cells, some with plasmablastic morphology; and (v) CD56-negative immunophenotype. The association between these features of MM reported previously and a high risk of LMM is reviewed. Studies including patients with these features are warranted to confirm their attributed LMM risk and to investigate the role of prophylactic chemoradiotherapy in this clinical setting.
Insights
Central nervous system involvement is rare in multiple myeloma (MM). This case highlights IgD MM with leptomeningeal myelomatosis (LMM), suggesting high-risk factors warranting further study.
Area of Science:
- Hematology
- Oncology
- Neurology
Background:
- Multiple myeloma (MM) rarely involves the central nervous system (CNS).
- Immunoglobulin D (IgD) MM constitutes a small fraction (1-2%) of MM cases.
- Leptomeningeal myelomatosis (LMM) is an uncommon but serious CNS complication of MM.
Observation:
- A case of IgD MM complicated by LMM in a female patient is presented.
- The patient exhibited several high-risk markers for CNS disease.
- These markers include IgD-lambda MM, stage III myeloma burden, extramedullary disease, circulating plasma cells (some plasmablastic), and CD56-negative immunophenotype.
Findings:
- IgD MM is disproportionately represented in patients with LMM.
- Specific biological markers are associated with an increased risk of LMM.
- The combination of IgD MM and specific clinical/biological features may indicate a particularly high risk for CNS involvement.
Implications:
- This case underscores the importance of recognizing high-risk features for CNS disease in MM.
- Further studies are needed to confirm the LMM risk associated with these markers.
- Investigating prophylactic chemoradiotherapy for high-risk MM patients is warranted.

