Related Experiment Video
Updated: Jun 12, 2026

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Extensive (8 to 12 cm2) noncircumferential endoscopic mucosal resection for early esophageal cancer
Philippe Monnier1, Yves Jaquet, Alexandre Radu
1Otolaryngology, Head and Neck Surgery Department, University Hospital Centre Hospitalier Universitaire Vaudois, Lausanne, Switzerland. philippe.monnier@chuv.ch

Background:
Endoscopic mucosal resection (EMR) is an appealing method for treating intramucosal esophageal cancer but must comply with the following stringent requirements: proper preoperative staging, complete resection of the lesion, obtaining a resected specimen for histologic analysis of safety margins, and squamous reepithelialization without stricture formation.
Methods:
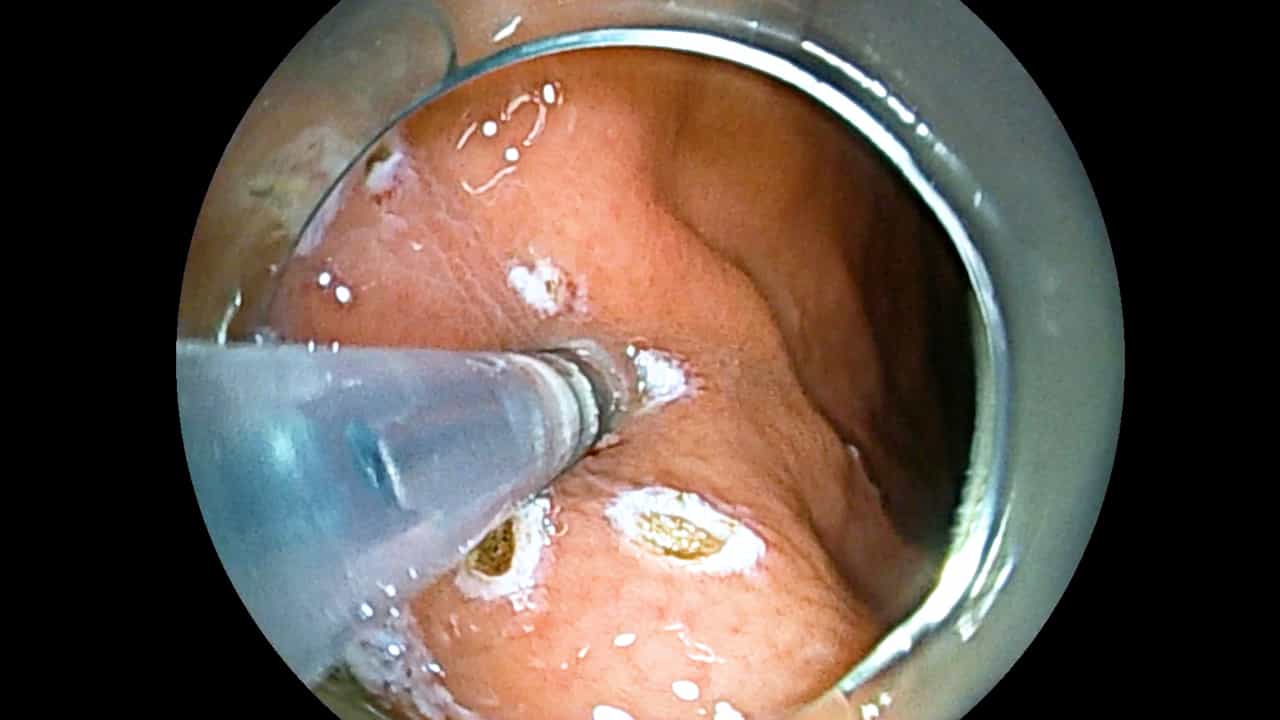
A rigid esophagoscope was created to resect up to 12 cm(2) of esophageal mucosa in a single specimen and at a constant depth through the submucosa. Under visual control, the esophageal mucosa is sucked into a transparent window and resected with a thin diathermy wire loop in 10 seconds. After extensive preclinical studies in a sheep model, this article reports our early experience in humans.
Results:
Twenty-one hemi-circumferential EMRs were performed for 11 dysplastic Barrett's esophagi and 10 early squamous cell carcinomas with no perforation, one hemorrhage controlled by embolization of the left gastric artery, and one incomplete resection. Deep safety margins were clear in 19 of 21 resected specimens (2 patients, unfit for operations, had submucosal invasion of squamous cell carcinoma and adenocarcinoma, respectively). Lateral margins were not clear by definition in 7 circumferential Barrett's esophagi, but were clear in 4 incomplete Barrett's esophagi and 10 early squamous cell carcinomas.
Conclusions:
Large EMRs of 12 cm(2) can safely be performed at the submucosal level in the esophagus. Although feasible in one session, circumferential EMR in humans is not yet advisable because of the risk of stricture formation during the healing phase. The rate of complications of this series of 21 EMRs in humans is acceptable.