Related Experiment Video
Updated: Jun 12, 2026
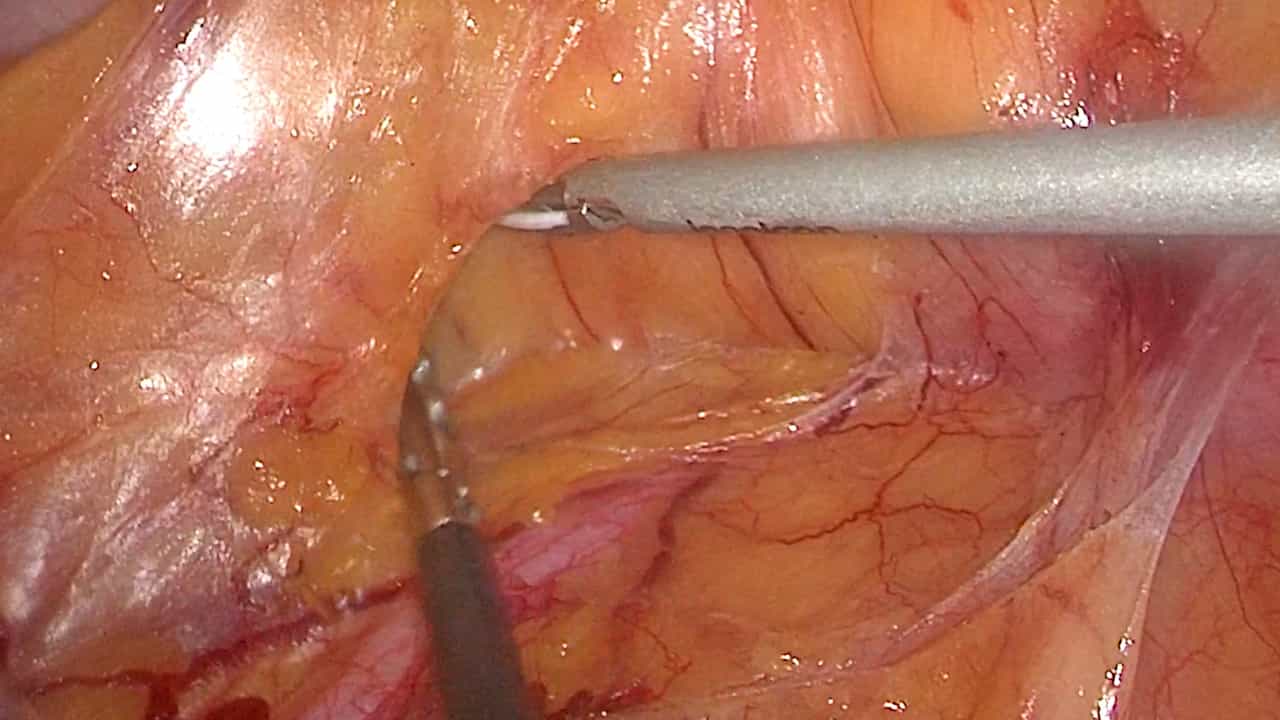

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Combined pancreaticoduodenectomy and extended right hemicolectomy: outcomes and indications
Eric T Kimchi1, Mehrdad Nikfarjam, Niraj J Gusani
1Department of Surgery, Penn State Milton S. Hershey Medical Center, Penn State College of Medicine Hershey, PA, USA.

Background:
Pancreaticoduodenectomy (PD) combined with an en bloc extended right hemicolectomy is required to achieve complete oncological resection of various malignancies. Information regarding the indications and outcomes of this procedure is limited.
Study Design:
Patients requiring PD combined with extended right hemicolectomy for primary tumours from 2002 to 2008 were identified.
Results:
PD combined with an en bloc extended right hemicolectomy was required in 14 patients, constituting 8% of pancreaticoduodenal resections. Pancreatic adenocarcinoma (8), retroperitoneal sarcoma (2) and colon cancer (2) were the main primary tumours resected. The indication for an extended right hemicolectomy was extensive tumour involvement of the transverse mesentery in seven patients. Clear tumour margins were achieved in 11 individuals. The median operating time was 10 h with intra-operative transfusions required in three patients. One or more complications were noted in eight, with delayed gastric emptying and pancreatic fistula the most common. The median length of hospital stay was 8 days. The overall 2-year survival in this series was 37%, with a median survival of 20 months in pancreatic cancer patients.
Conclusions:
This series suggests that PD combined with an en bloc extended right hemicolectomy is feasible and can achieve complete tumour clearance with acceptable morbidity.