Related Experiment Video
Updated: Jun 12, 2026


Isolated Pancreatic Islet Treatment and Apoptosis Measurement
Published on: May 2, 2025
Streptozotocin causes pancreatic beta cell failure via early and sustained biochemical and cellular alterations
E Adeghate1, R S Hameed, A S Ponery
1Department of Anatomy, Faculty of Medicine and Health Sciences, United Arab Emirates University, Al Ain, United Arab Emirates. eadeghate@uaeu.ac.ae

Abstract:
The morphological and biochemical changes that occur in the early phase of streptozotocin (STZ)-induced beta cell failure have not been characterized. The pancreas and plasma of rats treated with STZ were processed for morphological and biochemical parameters 1-24 h and 4 weeks after STZ treatment. Marked reduction in body weight was observed as early as 3 h post STZ treatment and hyperglycemia coupled with hypoinsulinaemia appeared in rats 1 h after treatment with STZ. Hyperglycemia, hyperglucagonemia and hypoinsulinemia became permanent 24 h after STZ treatment. The number of insulin-positive cells decreased significantly (p<0.05) at 24 h after STZ treatment with a concomitant increase in the number of glucagon-immunoreactive cells. Electron microscopy showed coalescing of beta cell granules 18 h after STZ treatment. A near to complete degranulation of beta cells settled at 21 h after STZ administration. The pancreatic tissue and plasma levels of adrenaline and noradrenaline increased significantly (p<0.004: pancreatic tissue; p<0.04: plasma) 3 h after STZ treatment and remained high after a reduction at 6 h post STZ treatment. The pancreatic tissue and plasma levels of 5-HIAA decreased significantly (p<0.002 pancreatic tissue; p<0.04: plasma) 1 h after STZ treatment and remained low after a reduction at 6-9 h post STZ treatment. STZ elicited significant dose-dependent increases in insulin secretion from the isolated pancreas. The early changes in catecholamine level may be used in screening and follow-up studies on diabetes mellitus.
Insights
Early changes in rat pancreatic beta cells after streptozotocin (STZ) treatment include rapid weight loss, hyperglycemia, and hypoinsulinemia. Catecholamine levels rise, while insulin-positive cells decrease, indicating early diabetes development.
Area of Science:
- Endocrinology
- Cell Biology
- Metabolic Research
Background:
- The early mechanisms of beta cell failure in streptozotocin (STZ)-induced diabetes are not well understood.
- Characterizing these initial changes is crucial for understanding diabetes pathogenesis.
Purpose of the Study:
- To investigate the early morphological and biochemical alterations in pancreatic beta cells following STZ administration.
- To establish a timeline of key events leading to beta cell dysfunction and diabetes.
Main Methods:
- Rats were treated with STZ, and pancreatic and plasma samples were analyzed at various time points (1-24 hours, 4 weeks).
- Morphological changes were assessed using electron microscopy.
- Biochemical parameters including insulin, glucagon, catecholamines, and 5-HIAA levels were measured.
Main Results:
- Hyperglycemia and hypoinsulinemia were observed as early as 1 hour post-STZ, becoming permanent by 24 hours.
- Significant reduction in insulin-positive cells and increase in glucagon-immunoreactive cells occurred by 24 hours.
- Beta cell degranulation was evident by 18-21 hours, with significant early increases in pancreatic and plasma catecholamines and decreases in 5-HIAA.
Conclusions:
- STZ rapidly induces hyperglycemia and hypoinsulinemia, preceding significant beta cell loss.
- Early alterations in catecholamine and 5-HIAA levels accompany beta cell dysfunction.
- These early biochemical changes may serve as valuable markers for diabetes screening and monitoring.

Related Concept Videos
 01:24
Type II Diabetes II: Pathophysiology
 01:26
Type I Diabetes II: Pathophysiology
 01:25
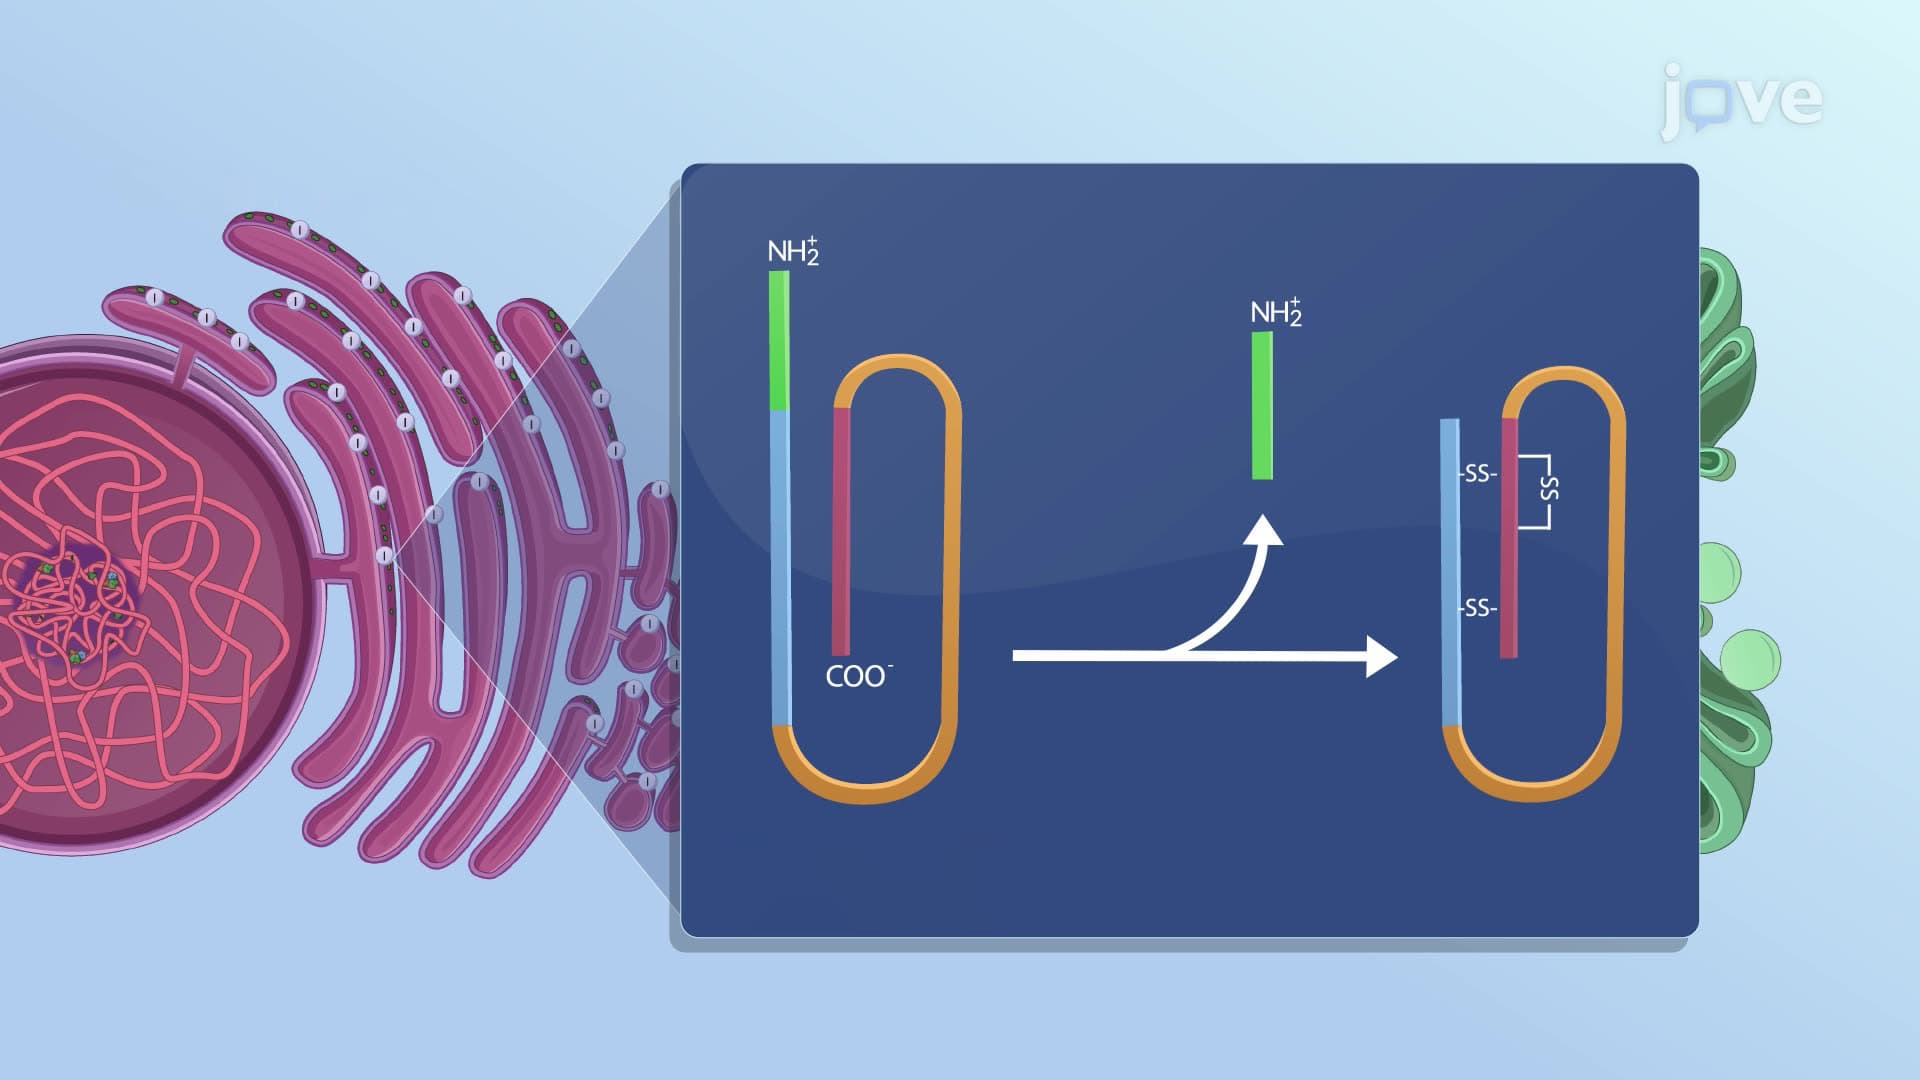
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:05
Insulin Secretory Vesicles
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...