Related Experiment Video
Updated: Jun 12, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Peak bone mass from longitudinal data: implications for the prevalence, pathophysiology, and diagnosis of
Claudie Berger1, David Goltzman, Lisa Langsetmo
1CaMos Methods Centre, McGill University, Montreal, Quebec, Canada.

Abstract:
We estimated peak bone mass (PBM) in 615 women and 527 men aged 16 to 40 years using longitudinal data from the Canadian Multicentre Osteoporosis Study (CaMos). Individual rates of change were averaged to find the mean rate of change for each baseline age. The age range for PBM was defined as the period during which bone mineral density (BMD) was stable. PBM was estimated via hierarchical models, weighted according to 2006 Canadian Census data. Lumbar spine PBM (1.046 ± 0.123 g/cm(2)) occurred at ages 33 to 40 years in women and at 19 to 33 years in men (1.066 ± 0.129 g/cm(2)). Total hip PBM (0.981 ± 0.122 g/cm(2)) occurred at ages 16 to 19 years in women and 19 to 21 years in men (1.093 ± 0.169 g/cm(2)). Analysis of Canadian geographic variation revealed that the levels of PBM and of mean BMD in those over age 65 sometimes were discordant, suggesting that PBM and subsequent rates of bone loss may be subject to different genetic and/or environmental influences. Based on our longitudinally estimated PBM values, the estimated Canadian prevalences of osteoporosis (T-score < -2.5) were 12.0% (L(1)-L(4)) and 9.1% (total hip) in women aged 50 years and older and 2.9% (L(1)-L(4)) and 0.9% (total hip) in men aged 50 years and older. These were higher than prevalences using cross-sectional PBM data. In summary, we found that the age at which PBM is achieved varies by sex and skeletal site, and different reference values for PBM lead to different estimates of the prevalence of osteoporosis. Furthermore, lack of concordance of PBM and BMD over age 65 suggests different determinants of PBM and subsequent bone loss.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 01:31
Osteoclasts in Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:17
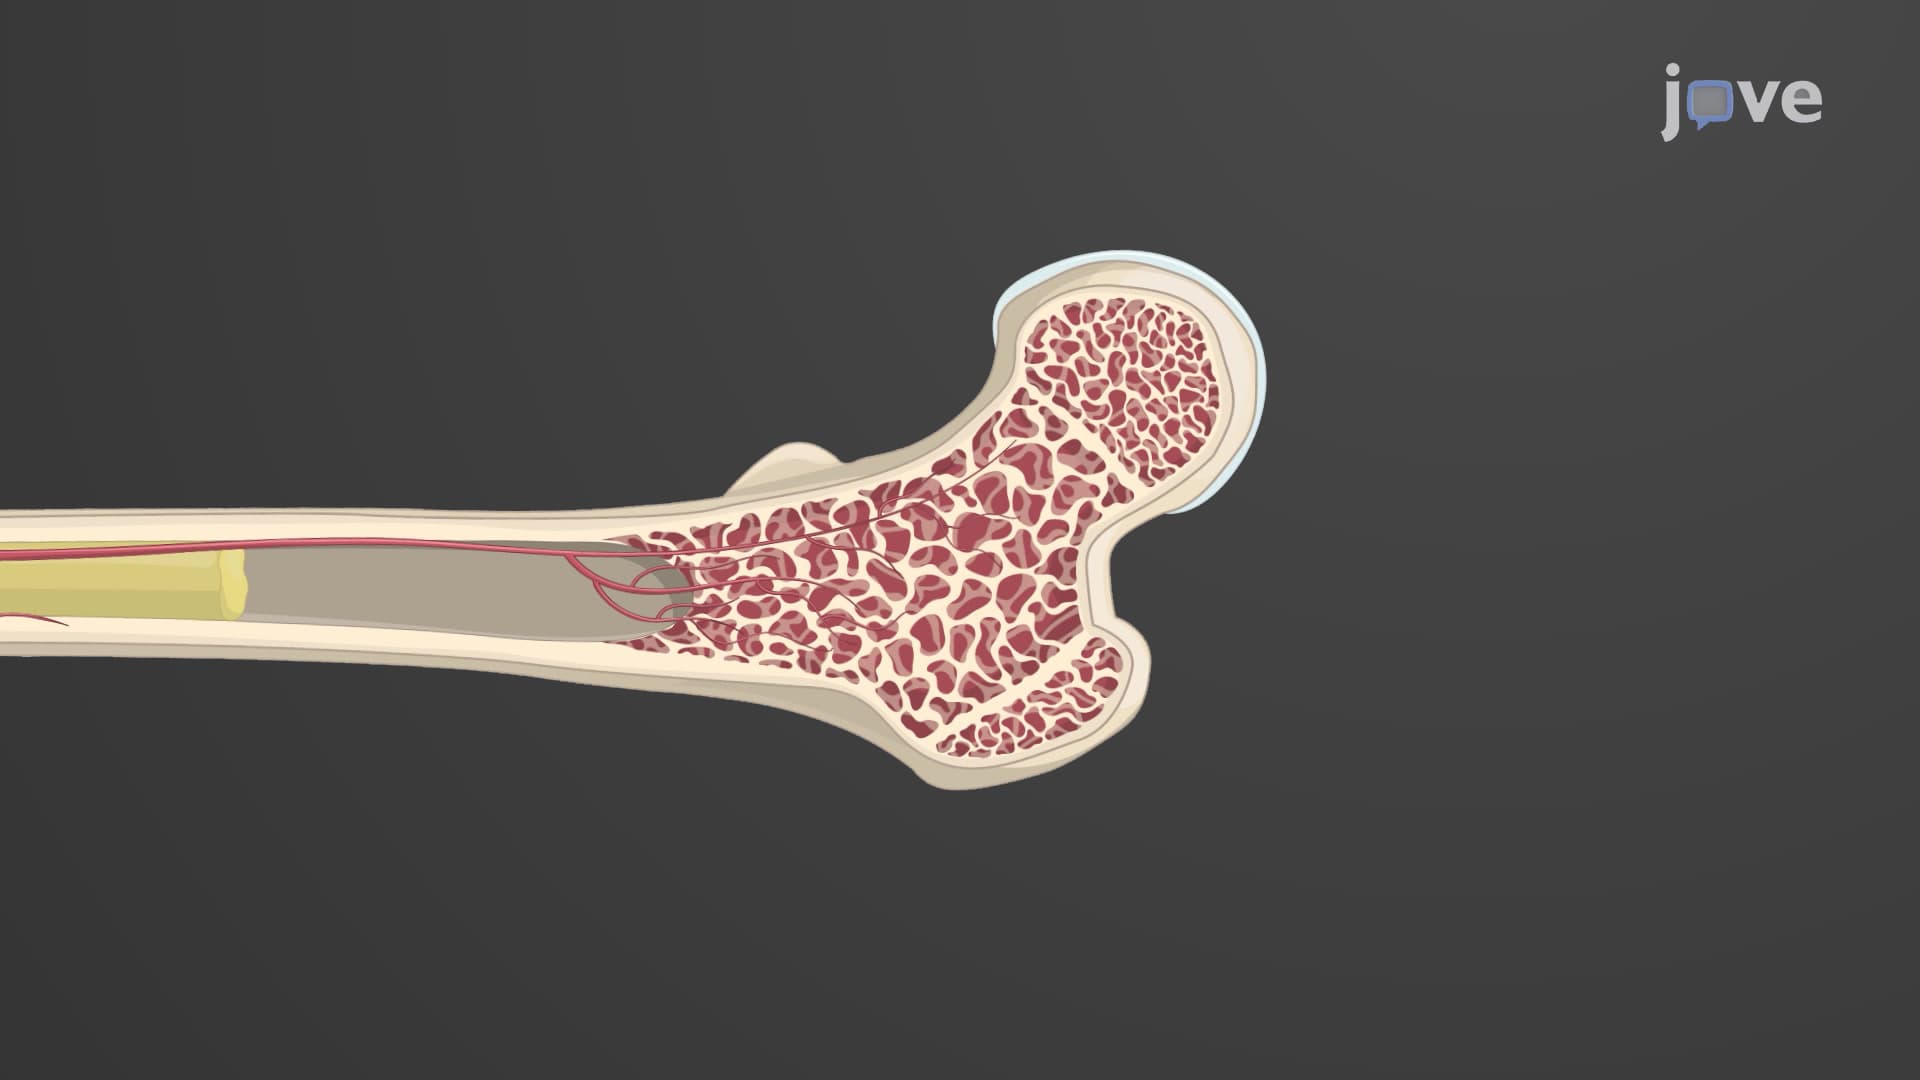
Gross Anatomy of Bone
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in adults, it...