Related Experiment Video
Updated: Jun 12, 2026
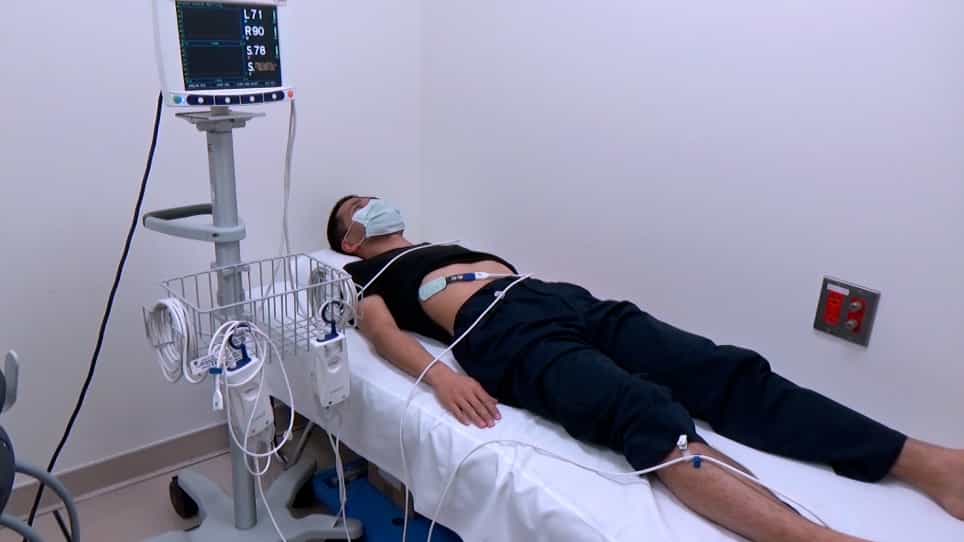
Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
[Kt calculation as a quality indicator of haemodialysis adequacy]
M Molina Núñez1, S Roca Meroño, R M de Alarcón Jiménez
1Servicio de Nefrología, Hospital Universitario Santa María del Rosell, Cartagena, Murcia. manuel.molina4@carm.es

The haemodialysis dose is a good marker of dialysis adequacy, and we usually monitor it with Kt/V measure. The dialysis dose monitored with Kt allows a better discrimination, detecting a percentage of the patients that perhaps do not get an adequate dose for their gender or body surface area after treatment with a minimum recommended dose of Kt/V. The objective of this study was to evaluate Kt as a clinical indicator referred to dialysis adequacy in the haemodialysis population. The aim was that more than 85% of the patients would achieve the recommended Kt target for their gender (at least 50 litres in men and 45 litres in women), or their body surface area. In each of the patients (mean 129) the Kt mean value was determined for three consecutive dialysis sessions, one every two months, during the follow-up period (14 months). At the beginning, the Kt/V value was on target (> 1.3) in 93.2% of the patients, but only in 58% according to Kt measure for their gender. After 4 months, we observed that 85% of patients' Kt target increased for their gender, but only 68% did if we used the Kt individualised for their body surface area. From month 6 to the end of the follow-up period, more than 85% of patients obtained an adequate Kt for their body surface area (p < 0.001). A significant increase of Kt mean (5.4 litres) was observed at the end of the study (p < 0.001). The usual dialysis prescription parameters were modified increasing blood flow rate (34.14 ml/min, p < 0.001), session effective duration (8.04 minutes, p < 0.001), dialyser surface area (24.1% of patients changed from helixone 1.3 to 1.6 m2, p < 0.001) and haemodialysis modality (56.8% of patients changed from conventional haemodialysis to on-line haemodiafiltration, p < 0.001). We conclude that monitoring dialysis dose with Kt is a good clinical measure of adequacy, and using it as a quality indicator can be done in line with the more demanding quality standards.
The haemodialysis dose is a good marker of dialysis adequacy, and we usually monitor it with Kt/V measure. The dialysis dose monitored with Kt allows a better discrimination, detecting a percentage of the patients that perhaps do not get an adequate dose for their gender or body surface area after treatment with a minimum recommended dose of Kt/V. The objective of this study was to evaluate Kt as a clinical indicator referred to dialysis adequacy in the haemodialysis population. The aim was that more than 85% of the patients would achieve the recommended Kt target for their gender (at least 50 litres in men and 45 litres in women), or their body surface area. In each of the patients (mean 129) the Kt mean value was determined for three consecutive dialysis sessions, one every two months, during the follow-up period (14 months). At the beginning, the Kt/V value was on target (> 1.3) in 93.2% of the patients, but only in 58% according to Kt measure for their gender. After 4 months, we observed that 85% of patients' Kt target increased for their gender, but only 68% did if we used the Kt individualised for their body surface area. From month 6 to the end of the follow-up period, more than 85% of patients obtained an adequate Kt for their body surface area (p < 0.001). A significant increase of Kt mean (5.4 litres) was observed at the end of the study (p < 0.001). The usual dialysis prescription parameters were modified increasing blood flow rate (34.14 ml/min, p < 0.001), session effective duration (8.04 minutes, p < 0.001), dialyser surface area (24.1% of patients changed from helixone 1.3 to 1.6 m2, p < 0.001) and haemodialysis modality (56.8% of patients changed from conventional haemodialysis to on-line haemodiafiltration, p < 0.001). We conclude that monitoring dialysis dose with Kt is a good clinical measure of adequacy, and using it as a quality indicator can be done in line with the more demanding quality standards.
Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis I: Introduction
 01:30
Continuous Renal Replacement Therapy
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy