Related Experiment Video
Updated: Jun 12, 2026


Studying Adipose Endothelial Cell/Adipocyte Cross-Talk in Human Subcutaneous Adipose Tissue
Published on: April 5, 2024
Plasma concentrations of adipocyte fatty acid binding protein in patients with Cushing's syndrome
1Third Department of Medicine, First Faculty of Medicine, Charles University and General University Hospital, Prague, Czech Republic.

Abstract:
Serum adipocyte fatty acid-binding protein (FABP-4) concentrations are linked to human obesity and other features of metabolic syndrome. Patients with Cushing´s syndrome (CS) develop numerous features of metabolic syndrome due to chronic cortisol excess. Here we tested the hypothesis that chronically increased cortisol levels in CS patients may alter circulating levels of FABP-4. Fourteen patients with CS, 19 patients with simple obesity (OB) and 36 healthy control subjects (C) were included in the study. Serum FABP-4 concentrations were significantly higher in both CS and OB patients relative to C group, but they did not differ between CS and OB groups. In a combined population of all groups, serum FABP-4 levels correlated positively with BMI, body fat content, serum glucose, triglycerides, HbA1c and HOMA index and were inversely related to HDL-cholesterol, resting energy expenditure and freeT3 levels. We conclude that FABP-4 levels are significantly increased in both patients with simple obesity and obese patients with Cushing´s syndrome. We suggest that increased FABP-4 concentrations in CS patients are rather due to their excessive fat accumulation and related metabolic abnormalities than due to a direct effect of cortisol on FABP-4 production.
Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:29
Drug Distribution: Plasma Protein Binding
 01:25
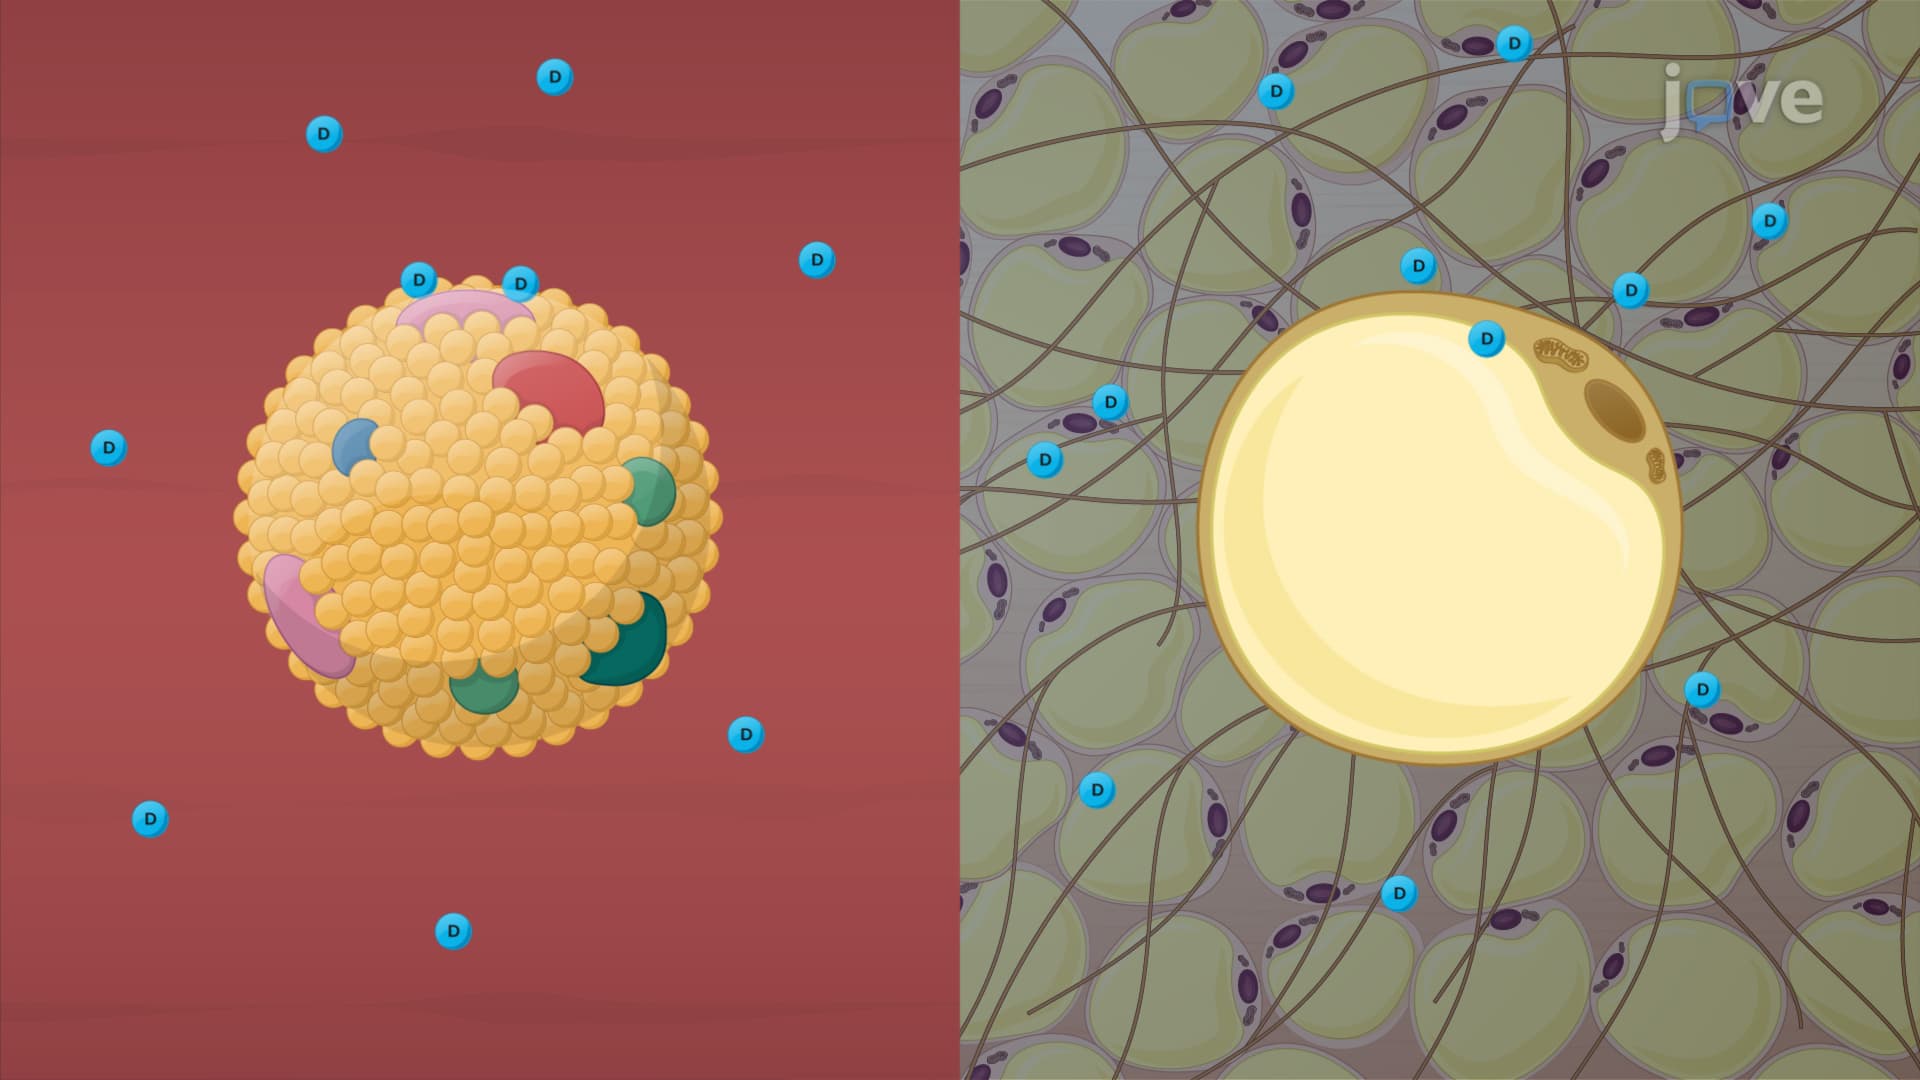
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:29
Cholesterol: Significance and Regulation
Considering cholesterol and...
 01:20
Factors Affecting Protein-Drug Binding: Protein-Related Factors
The physicochemical properties of a drug play a significant role in its ability to bind to proteins. Lipophilic drugs, which dissolve in fats, oils, and lipids, can be bound by...