Related Experiment Video
Updated: Jun 12, 2026

Biochemical Measurement of Neonatal Hypoxia
Published on: August 24, 2011
Oxidant balance markers at birth in relation to glycemic and acid-base parameters
Johan Verhaeghe1, Rita van Bree, Erik Van Herck
1Department of Obstetrics and Gynecology, Health Sciences Campus Gasthuisberg, Katholieke Universiteit Leuven, 3000 Leuven, Belgium. johan.verhaeghe@uz.kuleuven.be

Insights
Maternal diabetes during pregnancy does not directly impact newborn oxidative stress markers. However, newborn glucose and acid-base levels acutely influence these markers, suggesting immediate metabolic factors are key.
Area of Science:
- Perinatal Medicine
- Endocrinology
- Biochemistry
Background:
- Suboptimal glycemic control in diabetic pregnancies is linked to adverse fetal outcomes like acidemia and stillbirth.
- The intrauterine environment in diabetic pregnancies, characterized by hyperglycemia and hyperinsulinemia, may promote oxidative stress in the fetus.
- Understanding these mechanisms is crucial for improving neonatal outcomes.
Purpose of the Study:
- To investigate the association between maternal pregestational diabetes and oxidative stress markers in newborns.
- To explore the influence of the diabetic intrauterine milieu on fetal oxidative balance.
- To determine if markers of oxidative damage and antioxidant status differ between newborns of diabetic and non-diabetic mothers.
Main Methods:
- Studied 70 newborns from mothers with pregestational diabetes and 71 controls.
- Assayed umbilical vein plasma for protein carbonyls (PCs), malondialdehyde, and 8-hydroxy-2'deoxyguanosine as markers of oxidative damage.
- Measured glutathione peroxidase-3 (GPx3) as a circulating antioxidant enzyme.
Main Results:
- Newborns of diabetic mothers exhibited higher birth weight, relative hyperglycemia, hyperinsulinemia, and respiratory acidemia, despite generally good maternal glycemic control.
- No significant differences in oxidant balance marker concentrations were found between the groups at the P < .05 level.
- In the overall sample, higher glucose levels correlated with lower GPx3 and higher PCs; lower pH or greater base deficit correlated with higher PCs and 8-hydroxy-2'deoxyguanosine.
Conclusions:
- Maternal diabetes and long-term glycemic control do not appear to significantly alter newborn oxidant balance markers at birth.
- Newborn oxidative stress markers are acutely sensitive to immediate metabolic conditions, including glucose levels and acid-base status.
- These findings highlight the dynamic interplay between the neonatal metabolic environment and oxidative stress indicators.
Abstract:
In diabetic pregnancies, suboptimal glycemic control is a risk factor for fetal acidemia and stillbirth. We hypothesized that the diabetic intrauterine milieu (hyperglycemia, hyperinsulinemia, changes in acid-base status) might predispose to oxidative stress. We studied 70 newborns whose mothers had pregestational diabetes (58 with type 1 diabetes mellitus) and 71 control newborns from nondiabetic mothers. Protein carbonyls (PCs), malondialdehyde, and 8-hydroxy-2'deoxyguanosine were measured in umbilical vein plasma as a reflection of protein, lipid, and DNA oxidative damage, respectively; glutathione peroxidase-3 (GPx3), an important circulating antioxidant enzyme, was also assayed. Despite satisfactory glycemic control in the majority of diabetic mothers, their newborns showed higher birth weight and relative hyperglycemia, hyperinsulinemia, and respiratory acidemia. The oxidant balance marker concentrations were not different at the P < .05 level between the 2 groups, and there was no relationship to maternal hemoglobin A(₁C) levels in the diabetic group. However, in the entire sample, increasing glucose levels at birth were related to lower GPx3 and higher PC concentrations; and GPx3 and PC concentrations were inversely correlated. In addition, a depressed pH or larger base-deficit at birth was related to higher PC and 8-hydroxy-2'deoxyguanosine concentrations. In conclusion, oxidant balance markers at birth are not affected by maternal diabetes per se and its long-term glycemic control, yet some markers are acutely tuned to metabolic cues including glucose and the acid-base environment.

Related Concept Videos
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are produced, leading to a...
 01:29
Renal Regulation of Acid-Base Balance
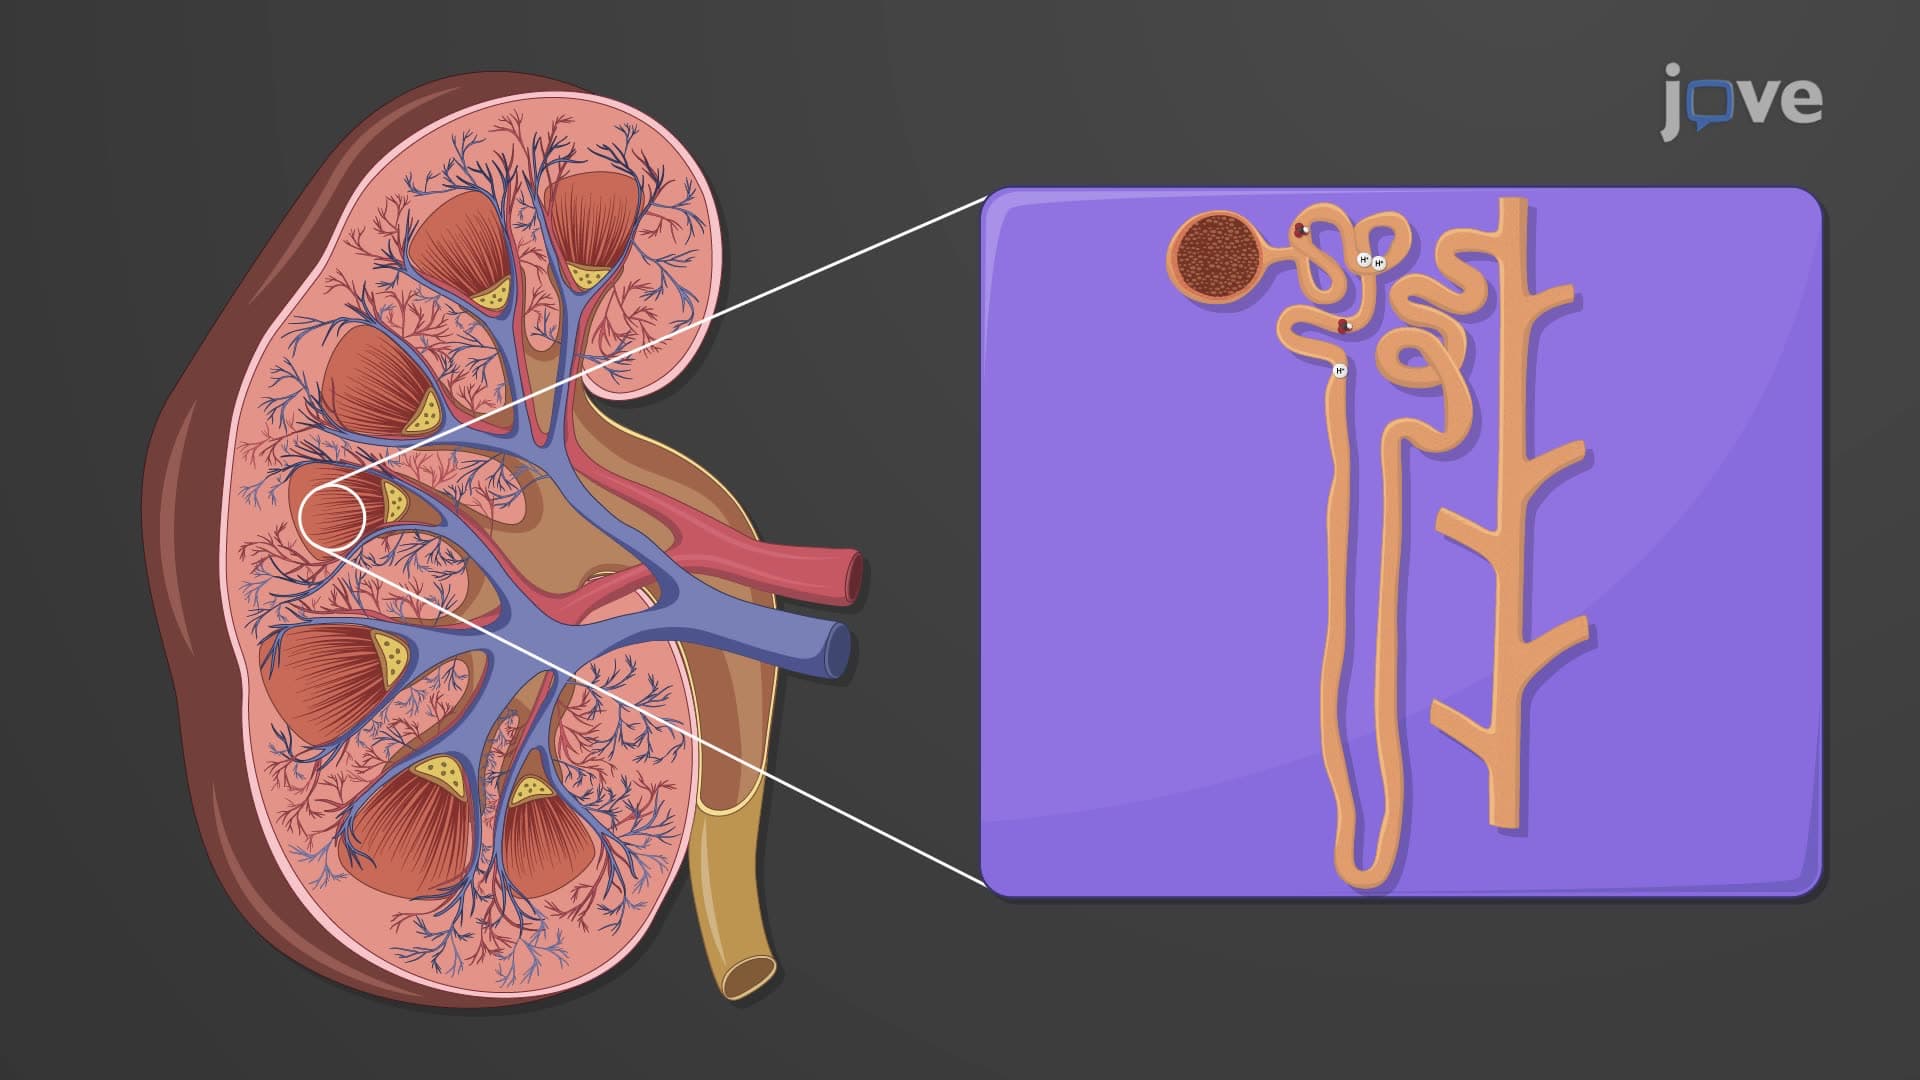
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:26
Blood Studies I: ABG and VBG
Arterial Blood Gas (ABG)
Arterial Blood Gas (ABG) studies are crucial for assessing the lungs' ability to supply oxygen and remove carbon dioxide, reflecting the patient's ventilation status. They also help understand the kidneys' capacity to reabsorb or...