Related Experiment Video
Updated: Jun 12, 2026
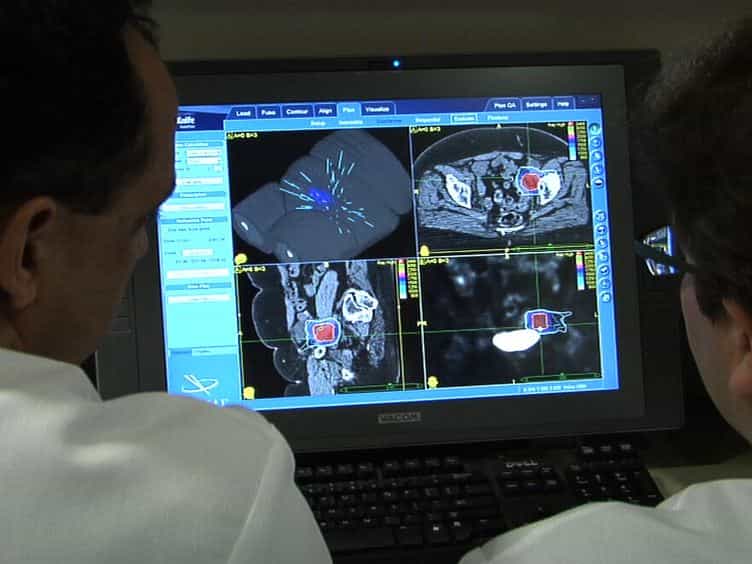

Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Hospice enrollment for terminally ill patients with gynecologic malignancies: impact on outcomes and interventions
Erin A Keyser1, Beverly G Reed, William J Lowery
1Division of Gynecologic Oncology, Brooke Army Medical Center, Ft. Sam Houston, TX 78234, USA.

Objective:
To determine survival and interventions for patients with non-curative gynecologic malignancies based on supportive care enrollment.
Methods:
An IRB approved retrospective review identified patients with recurrent/persistent gynecologic cancers from 2002 to 2008. Demographics, therapy, clinicopathologic data, hospice utilization, surgical/invasive procedures and survival were collected. Patients were considered hospice enrollees if they enrolled following recommendation from their provider (HOSPICE); however, patients that declined hospice when recommended were considered (NO HOSPICE), regardless if they ultimately received supportive care. Standard statistical tests including: t-test and Kaplan-Meier with Log Rank were used.
Results:
Eighty-one patients were identified: 29 patients (36%) NO HOSPICE and 52 (64%) HOSPICE. Mean age was 61. Most patients had ovarian cancer (54.3%), were white (61.7%) and had disease recurrence (72%). Patients utilized a median of 3 anti-neoplastic therapies (range 0-10) for recurrent or progressive/persistent disease. Median time receiving hospice care was 1week for NO HOSPICE patients versus 8weeks HOSPICE patients (p<0.0005). In a subset of patients with recurrent disease, median overall survival for NO HOSPICE patients was 9months (95% CI 5.9-12.1months) versus 17months (95% CI 11.1-22.9months) for HOSPICE patients (p=0.002). NO HOSPICE patients were more likely to have a procedure performed (55% vs. 31%) within 4weeks of their death, including the administration of chemotherapy OR 2.4 (95% CI 1.1-7.1, p=0.036).
Conclusions:
While retrospective reviews evaluating hospice are challenging, our data suggest no detrimental impact on survival for hospice patients. Continued evaluation for patients at the end-of-life is necessary in order to optimize resource utilization.
Related Concept Videos
 01:25
Continuing Care
 01:27
Nursing Ethical Principles II
Consider the following scenario, which illustrates how these principles are applied in the care of Mr. John, a fifty-year-old teacher diagnosed with metastatic liver cancer.
Initially, Mr. John's cancer...
 01:27
Ethical Issues
Ethical Concerns in Healthcare:
 01:21
Cancer Survival Analysis
 02:56
Treatment Resistant Cancers