Related Experiment Video
Updated: Jun 12, 2026

Evaluation of Cerebral Blood Flow Autoregulation in the Rat Using Laser Doppler Flowmetry
Published on: January 19, 2020
Cerebrovascular regulation during transient hypotension and hypertension in humans
Yu-Chieh Tzeng1, Chris K Willie, Greg Atkinson
1Cardiovascular Systems Laboratory, Physiological Rhythms Unit, Department of Surgery and Anesthesia, University of Otago, Wellington, Wellington South, New Zealand. shieak.tzeng@otago.ac.nz

The cerebrovasculature dilates or constricts in response to acute blood pressure changes to stabilize cerebral blood flow across a range of blood pressures. It is unclear, however, whether such dynamic cerebral autoregulation (dCA) is equally effective in responding to falling versus rising blood pressure. In this study we applied a pharmacological approach to evaluate dCA gain to transient hypotension and hypertension and compared this method with 2 established indices of dCA that do not explicitly differentiate between dCA efficacy and falling versus rising blood pressure. Middle cerebral arterial velocity and blood pressure recordings were made in 26 healthy volunteers randomized to 2 protocols. In 10 subjects, dCA gain to transient hypotension induced with intravenous nitroprusside was compared with dCA gain to transient hypertension induced with intravenous phenylephrine. In 16 subjects, dCA gain to transient hypotension induced with intravenous nitroprusside was compared with the rate of regulation and autoregulatory index derived from transient hypotension induced with the thigh cuff deflation technique. dCA gain to transient hypotension induced with intravenous nitroprusside was unrelated to dCA gain to transient hypertension induced with intravenous phenylephrine (r=0.06; P=0.87) and was consistently greater than dCA gain to transient hypertension induced with intravenous phenylephrine (0.57+/-0.16 versus 0.31+/-0.20 cm/s per millimeter of mercury; P<0.01). However, dCA gain to transient hypotension induced with intravenous nitroprusside was inversely related to the rate of regulation (r=-0.52; P=0.037) and autoregulatory index (r=-0.66; P=0.005). These data indicate that, under our laboratory conditions, dCA appears to be inherently nonlinear with disparate efficacy against rising and falling blood pressure, and dCA gain derived from pharmacologically induced transient hypotension correlates with established nonpharmacological indices of dCA.
The cerebrovasculature dilates or constricts in response to acute blood pressure changes to stabilize cerebral blood flow across a range of blood pressures. It is unclear, however, whether such dynamic cerebral autoregulation (dCA) is equally effective in responding to falling versus rising blood pressure. In this study we applied a pharmacological approach to evaluate dCA gain to transient hypotension and hypertension and compared this method with 2 established indices of dCA that do not explicitly differentiate between dCA efficacy and falling versus rising blood pressure. Middle cerebral arterial velocity and blood pressure recordings were made in 26 healthy volunteers randomized to 2 protocols. In 10 subjects, dCA gain to transient hypotension induced with intravenous nitroprusside was compared with dCA gain to transient hypertension induced with intravenous phenylephrine. In 16 subjects, dCA gain to transient hypotension induced with intravenous nitroprusside was compared with the rate of regulation and autoregulatory index derived from transient hypotension induced with the thigh cuff deflation technique. dCA gain to transient hypotension induced with intravenous nitroprusside was unrelated to dCA gain to transient hypertension induced with intravenous phenylephrine (r=0.06; P=0.87) and was consistently greater than dCA gain to transient hypertension induced with intravenous phenylephrine (0.57+/-0.16 versus 0.31+/-0.20 cm/s per millimeter of mercury; P<0.01). However, dCA gain to transient hypotension induced with intravenous nitroprusside was inversely related to the rate of regulation (r=-0.52; P=0.037) and autoregulatory index (r=-0.66; P=0.005). These data indicate that, under our laboratory conditions, dCA appears to be inherently nonlinear with disparate efficacy against rising and falling blood pressure, and dCA gain derived from pharmacologically induced transient hypotension correlates with established nonpharmacological indices of dCA.

Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:26
Transient Ischemic Attack l: Introduction
 01:30
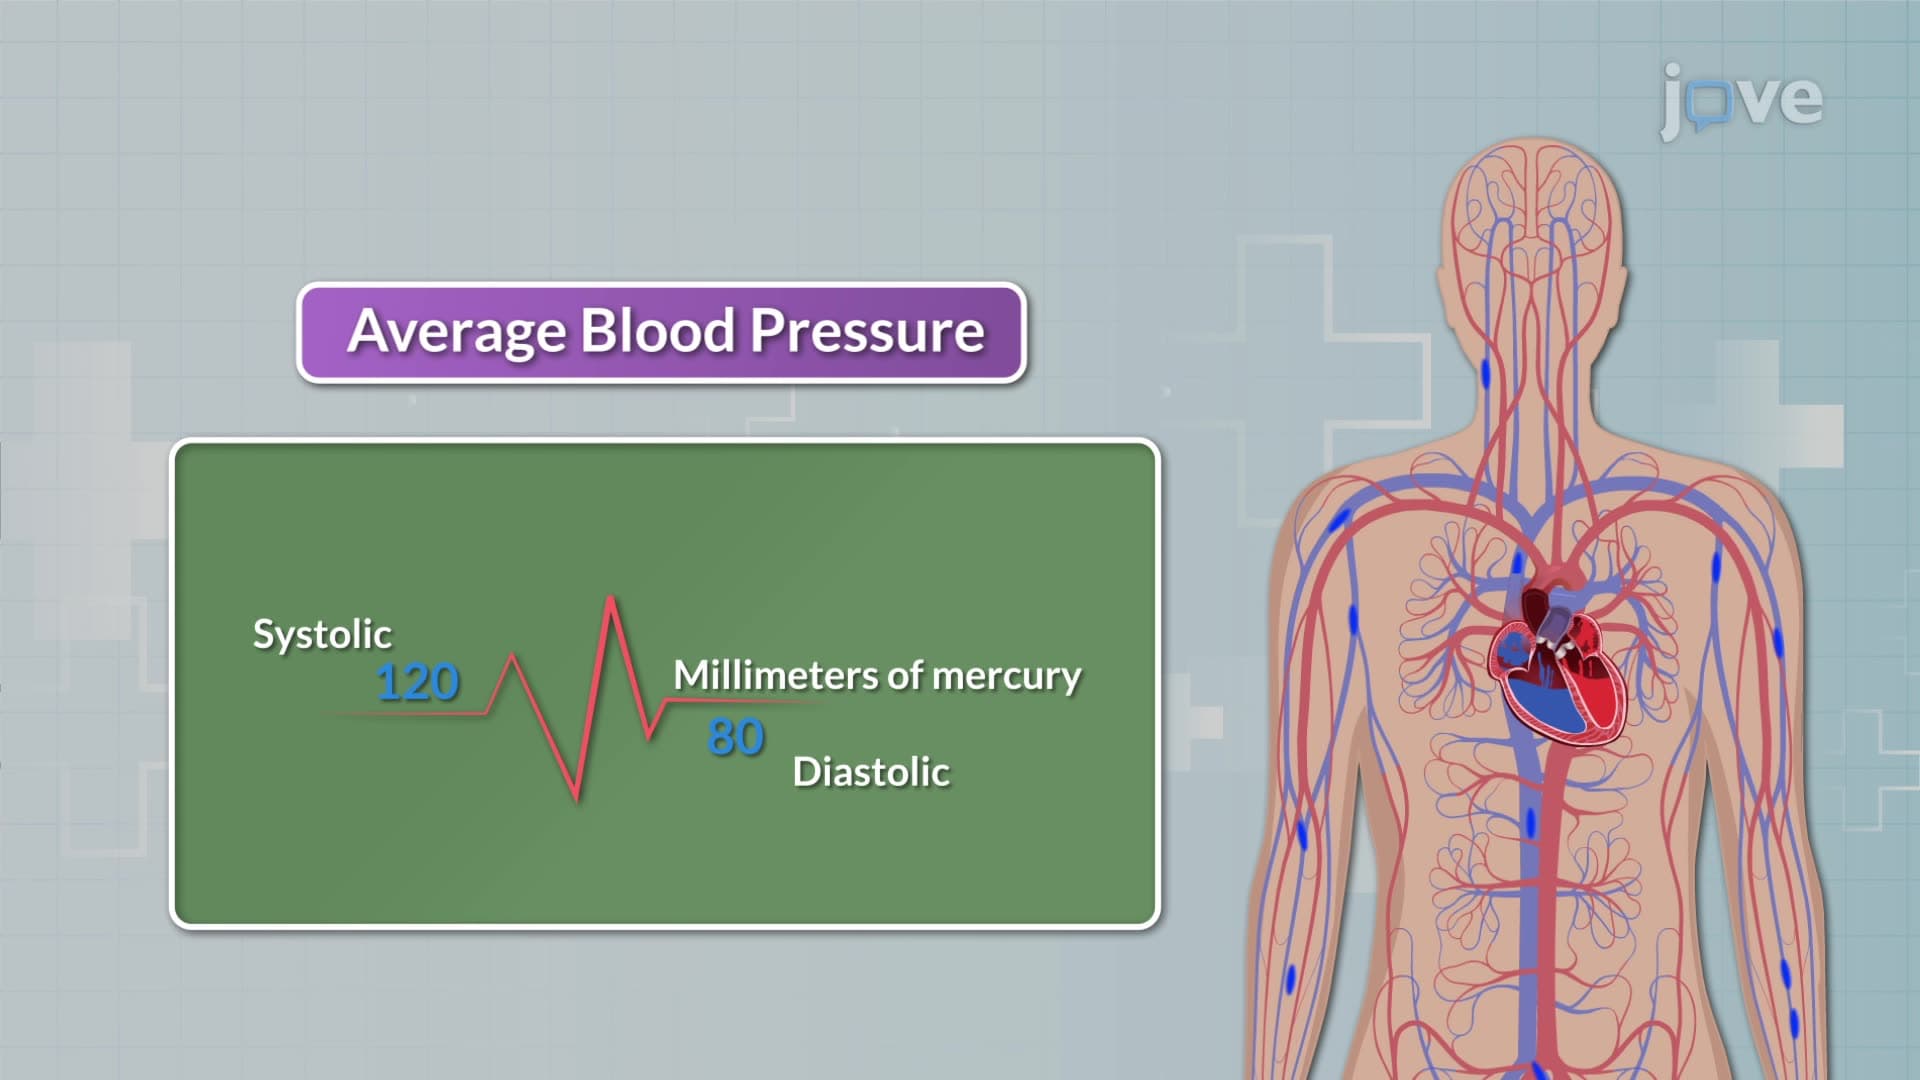
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...