Related Experiment Video
Updated: Jun 12, 2026


The Isolation and Culture of Primary Epicardial Cells Derived from Human Adult and Fetal Heart Specimens
Published on: April 24, 2018
Epicardial versus endocardial permanent pacing in adults with congenital heart disease
Christopher John McLeod1, Christine H Attenhofer Jost, Carole A Warnes
1Division of Cardiovascular Diseases, Mayo Clinic, 200 First Street SW, Rochester, MN 55905, USA.

Insights
Permanent pacing in congenital heart disease (CHD) patients often requires repeat interventions, particularly due to lead failure. Epicardial systems show higher lead failure rates and lower durability compared to endocardial systems in this population.
Area of Science:
- Cardiology
- Pediatric Cardiology
- Cardiac Electrophysiology
Background:
- Permanent pacing (PM) in congenital heart disease (CHD) presents unique challenges.
- Long-term outcomes of PM in CHD patients are not well-established.
Purpose of the Study:
- To evaluate long-term outcomes and complications of permanent pacing in patients with congenital heart disease.
- To compare the durability and complication rates of epicardial versus endocardial pacing systems in CHD.
Main Methods:
- A retrospective review of pacemaker complications and reinterventions over a 38-year period.
- Data grouped by epicardial or endocardial pacing approaches.
- Analysis of 106 patients and 259 PM procedures.
Main Results:
- Lead failure was the primary driver for reintervention (49%).
- Epicardial pacing was more common in patients with complex CHD, cyanosis, residual shunts, or Ebstein's anomaly.
- Epicardial systems demonstrated significantly higher lead failure rates and lower durability compared to endocardial systems.
Conclusions:
- Permanent pacing in CHD is associated with significant morbidity and a high need for repeat interventions.
- Patients with Ebstein's anomaly and those with epicardial pacing systems face a higher risk of lead failure.
- Endocardial pacing systems offer greater durability in the long term for CHD patients.
Background:
Permanent pacing (PM) in patients with congenital heart disease (CHD) presents unique challenges-with little known about the long-term outcomes.
Methods:
Pacemaker complications and reinterventions were reviewed over a 38-year period and were grouped by epicardial or endocardial approaches.
Results:
The average age at intervention was 37 ± 19 years for 106 patients and 259 PM procedures were performed (2.4 ± 2 per patient). From the first PM procedure, patients were followed for 11.6 ± 14 years. The most common indications for initial PM intervention were heart block (25%) and sinus node dysfunction (20%), yet reintervention was driven primarily by lead failure (49%). Endocardial systems were initially implanted in 73 patients (67%). Epicardial pacing was more common in patients with complex CHD (p = 0.006), cyanosis (p < 0.001), residual shunts (0.01), or Ebstein's anomaly (p = 0.01). Fifty-one devices (28%) developed lead or generator complications. Epicardial systems were most likely to develop lead failure (p < 0.0001), predominantly in the ventricular lead (p < 0.0001). Endocardial systems were found to be more durable than the epicardial systems (p = 0.023), and Ebstein's anomaly or an epicardial system was an independent predictor of lead failure.
Conclusions:
Permanent pacing in CHD is associated with considerable morbidity and the need for repeat intervention, especially in those with Ebstein's anomaly. Epicardial pacing systems appear to have a higher incidence of lead failure and are significantly less durable in this group.
Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:19
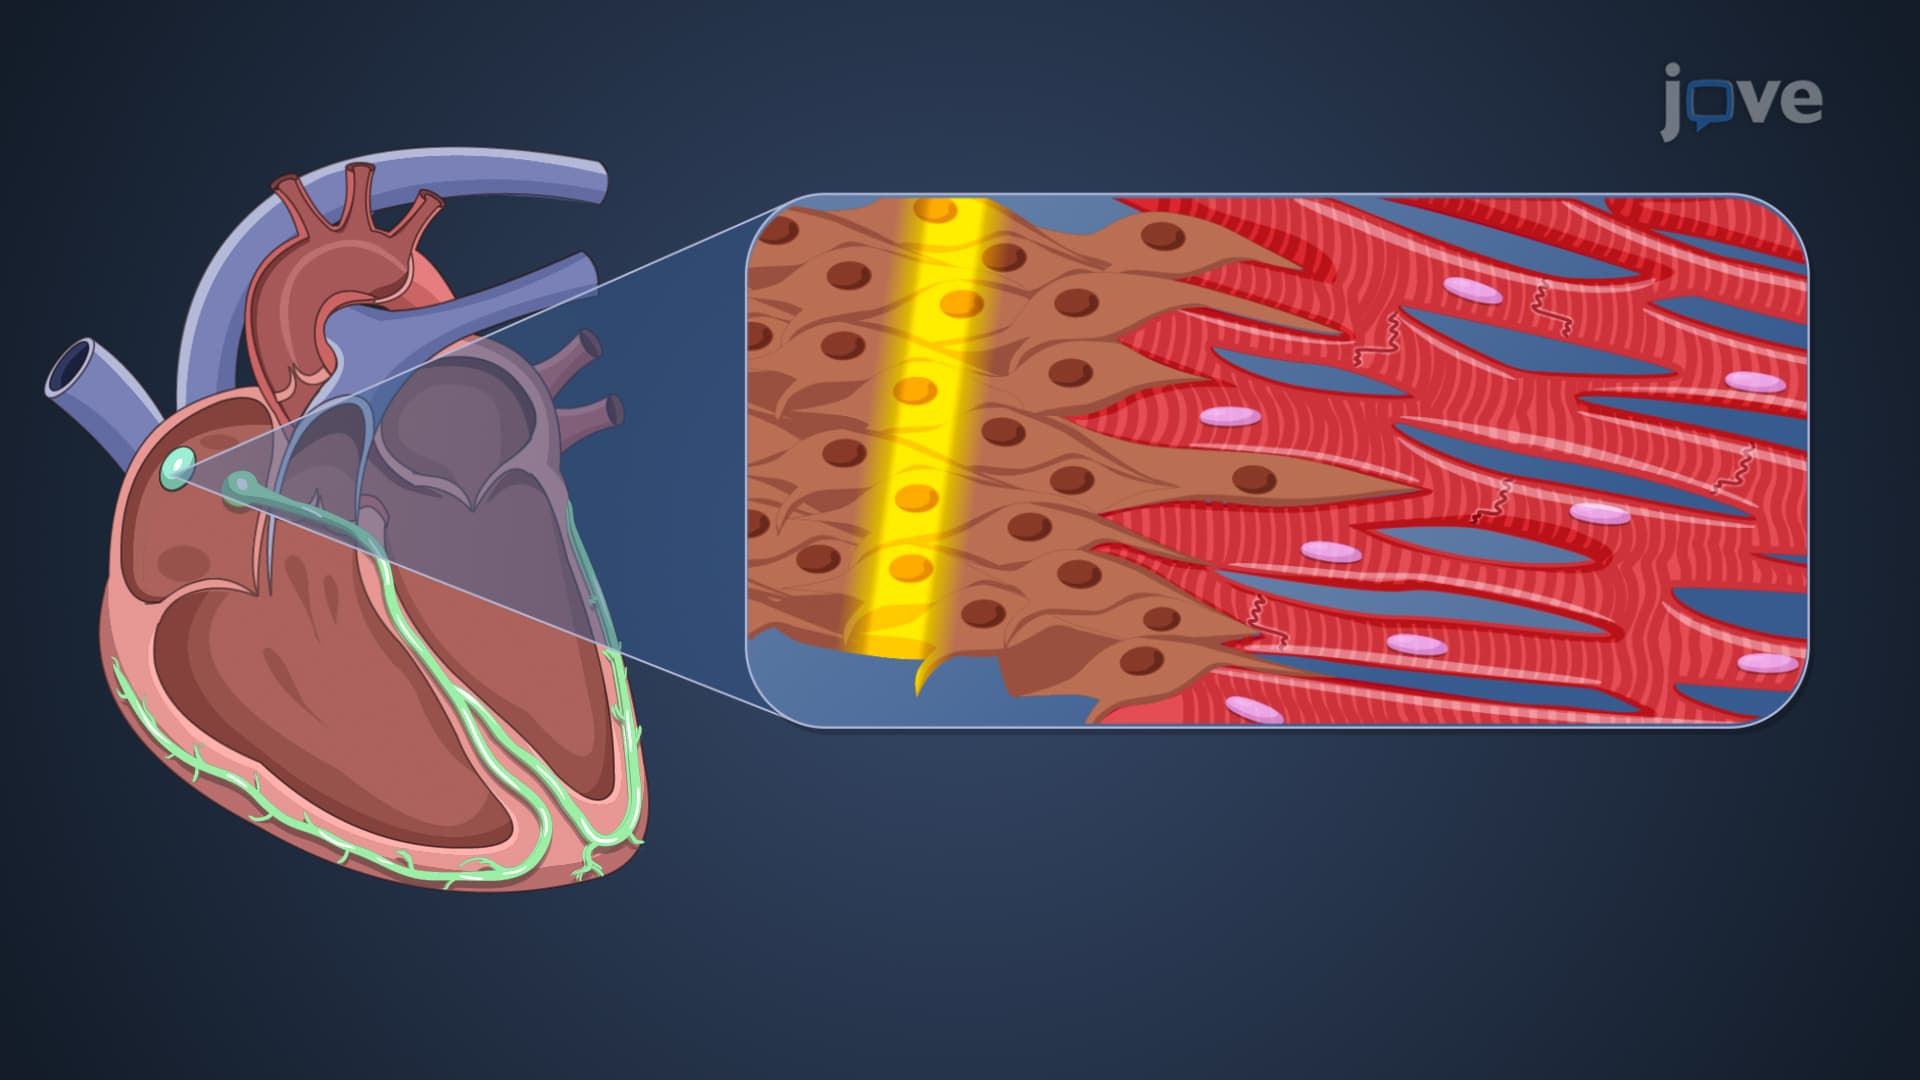
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac muscle...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:19
Electrophysiology of Normal Cardiac Rhythm