Related Experiment Video
Updated: Jun 12, 2026
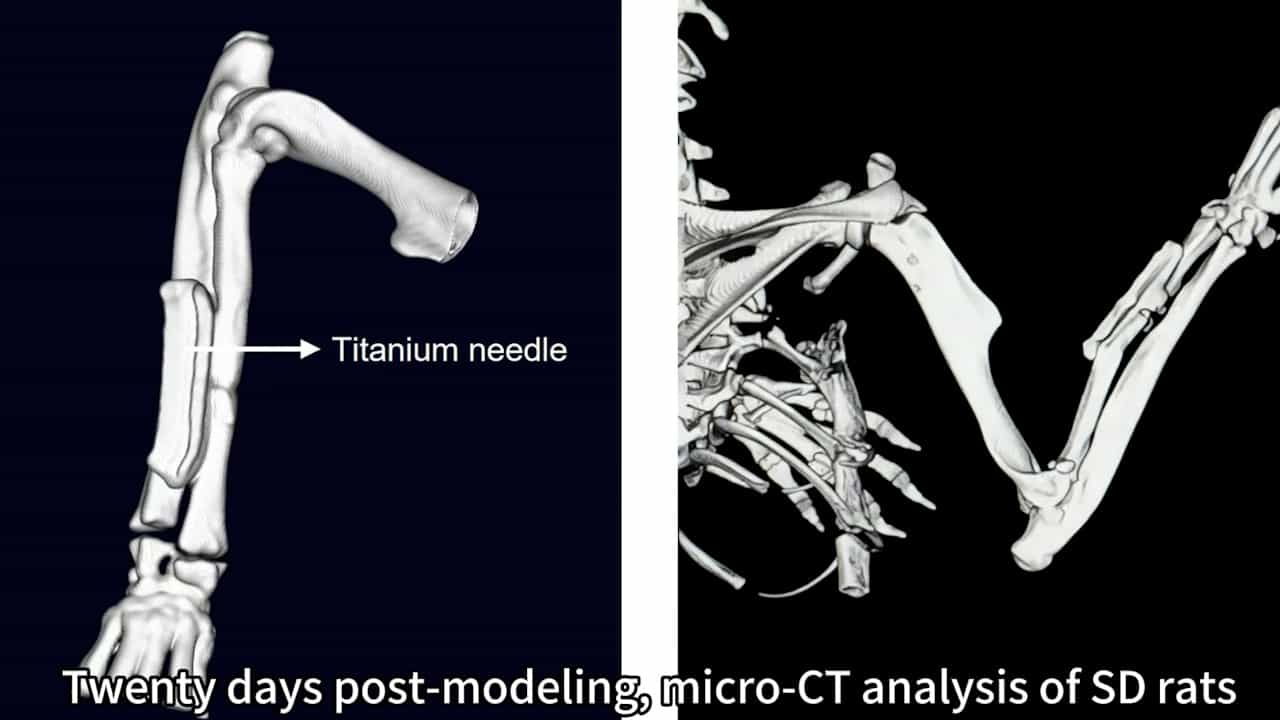

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Greenstick fractures of the middle third of the forearm. A prospective multi-centre study
T Schmuck1, S Altermatt, P Büchler
1District Hospital Langenthal, Department of Orthopaedics, Langenthal, Switzerland.

Background:
Greenstick fractures suffered during growth have a high risk for refracture and posttraumatic deformity, particularly at the forearm diaphysis. The use of a preemptive completion of the fracture by manipulation of the concave cortex is controversial and data supporting this approach are few.
Aim:
Aim of this study was to determine the factors which predispose to refracture and deformities, and to define therapeutic strategies.
Methods:
We prospectively gathered clinical and radiographic data over a period of one year on greenstick fractures of the middle third of the forearm in children as part of a multi-centre study. Endpoint was a follow-up visit at one year. Radiographic deformity, state of consolidation at resumption of physical activities and refracture rate were analysed statistically (ANOVA, Student's t-test and Pearson's chi-square test) with regard to patient age, gender, fracture type, therapy and time in plaster.
Results:
We collected the data of 103 patients (63 boys, 40 girls), average age 6.6 years (1.3-14.5 years), the vast majority of whom had a combined greenstick fracture of the radius and ulna. 6.7% of the patients sustained a refracture within 49 days (29-76) after plaster removal. They were significantly older (p=0.017) with a significantly higher incidence of manual completion of the fracture with radiographic signs of partial consolidation (p=0.025). Residual deformities were significantly smaller after completion of the fracture compared to reduction without completion (p=0.019) or plaster fixation alone (p<0.005).
Conclusions:
Completion of a greenstick fracture does not prevent refracture. Nevertheless, it diminishes the extent of secondary deformities in cases where the primary angulation exceeds the remodelling capacity. Prevention of refracture should include a routine radiographic follow-up 4-6 weeks after injury with continuation of plaster fixation in cases of partial consolidation.

Related Concept Videos
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a short...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:19
Bones of the Upper Limb: Humerus