Related Experiment Video
Updated: Jun 11, 2026
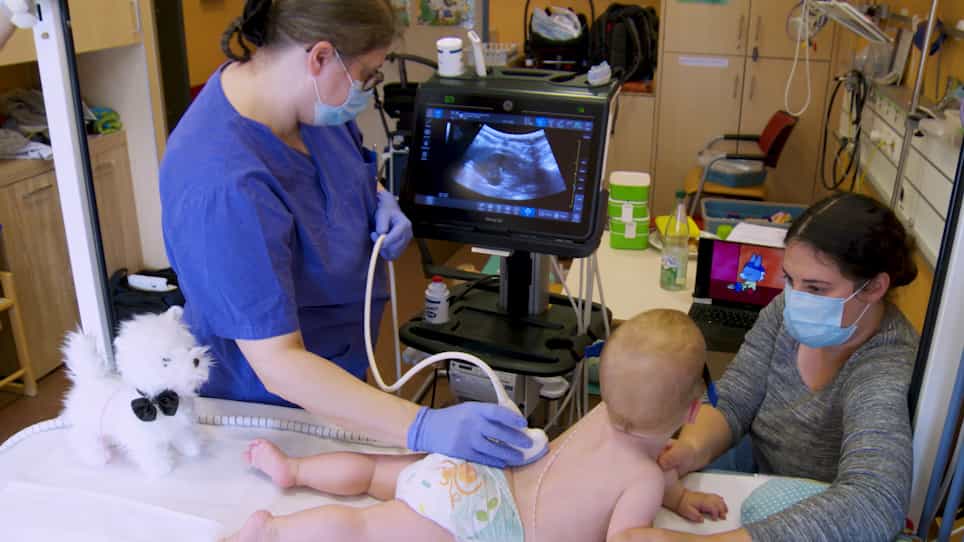

How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Is cerebral oxygen supply compromised in preterm infants undergoing surgical closure for patent ductus arteriosus?
Petra M A Lemmers1, Mirella C Molenschot, Jola Evens
1Department of Neonatology, University Medical Center/Wilhelmina Children's Hospital, Utrecht, The Netherlands. p.lemmers@umcutrecht.nl

Insights
Surgical closure of patent ductus arteriosus (PDA) in preterm infants may decrease cerebral oxygenation. This study monitored cerebral oxygen saturation and brain activity, finding a risk of further oxygenation compromise after PDA ligation.
Area of Science:
- Neonatalogy
- Pediatric Surgery
- Neurocritical Care
Background:
- A hemodynamically significant patent ductus arteriosus (PDA) is a known risk factor for brain injury in preterm infants.
- Previous research indicated lower regional cerebral oxygen saturation (rScO2) in infants with PDA, which improved after indomethacin treatment.
- However, surgical PDA ligation may carry a higher risk of neurodevelopmental impairment.
Purpose of the Study:
- To assess the impact of surgical PDA closure on cerebral oxygenation and brain activity in preterm infants.
- Investigate changes in regional cerebral oxygen saturation (rScO2) and cerebral fractional tissue oxygen extraction (cFTOE) using near-infrared spectroscopy.
- Evaluate brain activity using amplitude-integrated electro-encephalography (aEEG) before, during, and after PDA ligation.
Main Methods:
- Monitoring of blood pressure, arterial saturation, rScO2, cFTOE, and aEEG in 20 preterm infants (gestational age 24.7-30.4 weeks).
- Measurements were taken before, during, and up to 24 hours after surgical PDA closure.
- Analysis focused on changes in physiological parameters and brain activity related to the surgical intervention.
Main Results:
- A significant drop in rScO2 was observed in 13 infants during surgery, accompanied by decreased aEEG amplitude.
- Twelve infants had intraoperative rScO2 values below 50%, with five below 40%.
- Twenty-four hours post-surgery, rScO2 levels were significantly higher, and cFTOE values were lower compared to pre-clipping measurements.
Conclusions:
- Surgical ligation of PDA in preterm infants carries a risk of further compromising cerebral oxygenation.
- The findings highlight the potential for reduced cerebral oxygenation during and immediately after PDA ligation.
- Close monitoring of cerebral oxygenation and brain activity is crucial in preterm infants undergoing PDA surgery.
Background:
A haemodynamically important patent ductus arteriosus (PDA) is a risk factor for brain damage in preterm infants. The authors previously reported lower regional cerebral oxygen saturation (rScO(2)) in infants with PDA, which recovered after administration of indomethacin. However, PDA ligation has been reported to pose an even higher risk of neurodevelopmental impairment.
Objective:
To investigate the impact of surgical closure of PDA on rScO(2) and cerebral fractional tissue oxygen extraction (cFTOE), measured by near-infrared spectroscopy, and on amplitude-integrated electro-encephalography (aEEG) measured brain activity.
Design/Methods:
In 20 preterm infants (gestational age 24.7-30.4 weeks; birth weight 630-1540 g), blood pressure, arterial saturation, rScO(2), cFTOE and aEEG were monitored before, during and up to 24 h after surgery.
Results:
Before surgery, median (range) rScO(2) was 53% (41-68%), and during surgery, but before ductal clipping, it was 46% (31-89%). Eleven infants showed a drop in blood pressure and 13 infants a drop in rScO(2) during surgery (range 2-21%), accompanied by a decrease in aEEG amplitude. Twelve infants had rScO(2) values below 50% during surgery, with five being below 40%. Only at 24 h after surgery was rScO(2) higher (61% (36-85%), p<0.05) and cFTOE values lower (0.38 (0.09-0.61); p<0.05) compared with preclipping values.
Conclusion:
Ductal ligation poses a risk for a further decrease in already compromised cerebral oxygenation in preterm infants.


