Related Experiment Video
Updated: Jun 11, 2026
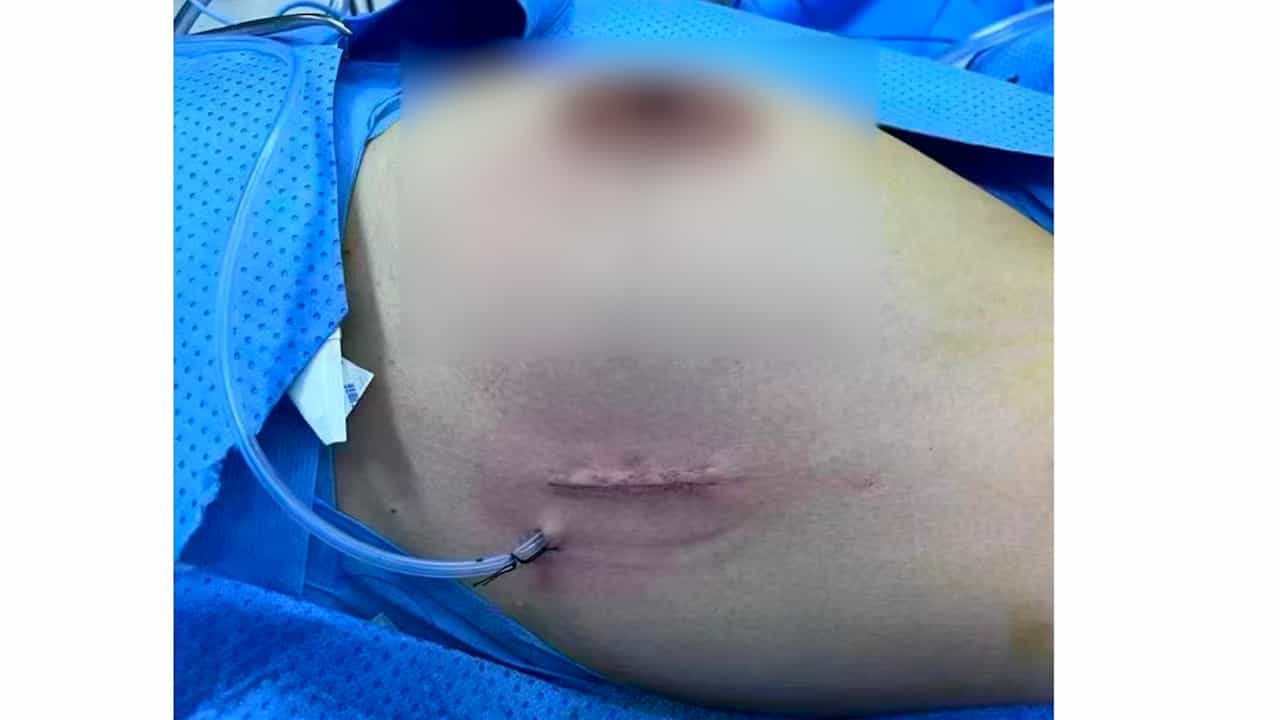
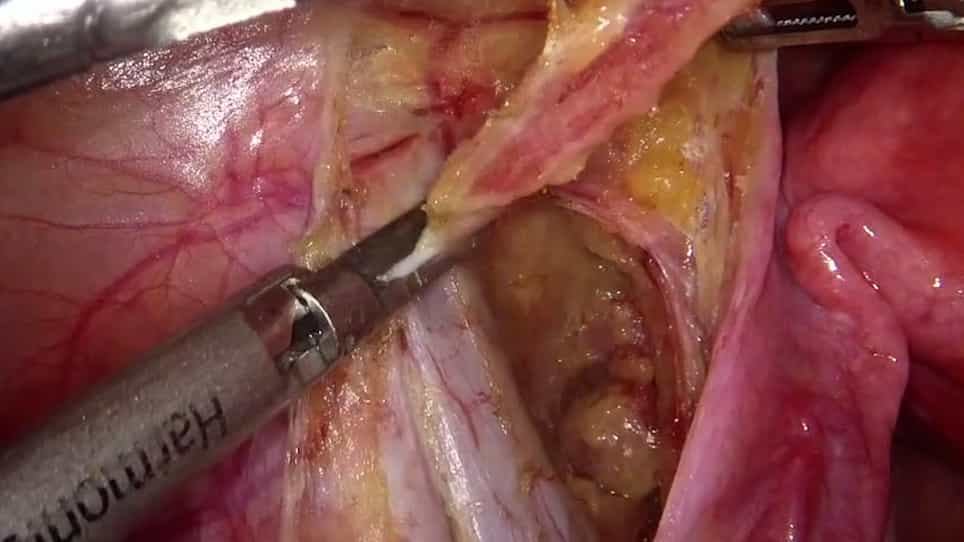
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Intra-operative evaluation of the sentinel lymph node for T1-N0 breast-cancer patients: always or never? A
G Canavese1, P Bruzzi, A Catturich
1Advanced Surgical Senology Unit, National Cancer Research Institute, Genoa, Italy.

Aim:
To investigate whether omitting intra-operative staging of the sentinel lymph node (SLN) in T1-N0 breast-cancer patients is feasible and convenient because it could allow a more efficient management of human and logistic resources without leading to an unacceptable increase in the rate of delayed axillary lymph node dissection (ALND).
Methods:
According to the experimental procedure, T1a-T1b-patients were to not receive any intra-operative SLN evaluation on frozen sections (FS). In all T1c-patients, the SLN was macroscopically examined; if the node appeared clearly free of disease, no further intra-operative assessment was performed; if the node was clearly metastatic or presented a dubious aspect, the pathologist proceeded with analysis on FS. T2-patients, enrolled in the study as reference group, were treated according to the institutional standard procedure; they all received SLN staging on FS.
Results:
The study included 395 T1-N0-patients. Among the 118 T1a-T1b-patients whose SLN was not analyzed at surgery, 12 (10.2%) were recalled for ALND. In the group of 258 T1c-patients, 112 received SLN analysis on FS and 146 did not. An SLN falsely negative either at macroscopic or FS examination was found in 33 (12.8%) cases. Overall, the rate of recall for ALND was 11.6% as compared to 8.4% in T2-patients. Using the experimental protocol, the institution reached a 9.6% cost saving, as compared to the standard procedure.
Conclusions:
Omission of SLN intra-operative staging in T1-N0-patients is rather safe. It provides the institution with both management and economical advantages.