

Tachyarrhythmias, bradyarrhythmias and acute coronary syndromes
1Department of Cardiology and Angiology, University of Bochum, Germany.

Insights
Bradyarrhythmias occur in 0.3-18% of acute coronary syndrome (ACS) patients, often resolving spontaneously. Treatment varies, with atropine effective for many, while pacemaker needs differ based on myocardial infarction type.
Area of Science:
- Cardiology
- Electrophysiology
- Internal Medicine
Background:
- Bradyarrhythmias, including sinus node dysfunction and atrioventricular blocks, affect 0.3% to 18% of patients with acute coronary syndrome (ACS).
- These arrhythmias can stem from various conduction system disturbances and may be transient or persistent.
Purpose of the Study:
- To review the incidence, causes, and management of bradyarrhythmias in acute coronary syndrome (ACS) patients.
- To differentiate treatment strategies based on the type and location of myocardial infarction (MI).
Main Methods:
- Literature review of studies on bradyarrhythmias in ACS.
- Analysis of diagnostic criteria and treatment outcomes for various bradyarrhythmic conditions.
Main Results:
- First-degree atrioventricular block is common (4-13%) and often transient. Third-degree atrioventricular blocks are transient in inferior MI but often permanent in anterior MI.
- Intravenous atropine is effective in 70-80% of ACS patients with bradyarrhythmia. Pacemaker stimulation is frequently required for anterior MI but less so for inferior MI.
- Ventricular arrhythmias (VTA) in ACS are best treated with amiodarone, with defibrillation and advanced life support being crucial for ventricular flutter/fibrillation.
Conclusions:
- Bradyarrhythmias in ACS have varied etiologies and prognoses.
- Management requires individualized approaches, considering MI location and arrhythmia type.
- Prompt intervention with medications like atropine or amiodarone, and judicious use of pacemakers or defibrillation, are key to improving outcomes.
Abstract:
The incidence of bradyarrhythmias in patients with acute coronary syndrome (ACS) is 0.3% to 18%. It is caused by sinus node dysfunction (SND), high-degree atrioventricular (AV) block, or bundle branch blocks. SND presents as sinus bradycardia or sinus arrest. First-degree AV block occurs in 4% to 13% of patients with ACS and is caused by rhythm disturbances in the atrium, AV node, bundle of His, or the Tawara system. First- or second-degree AV block is seen very frequently within 24 h of the beginning of ACS; these arrhythmias are frequently transient and usually disappear after 72 h. Third-degree AV blocks are also frequently transient in patients with infero-posterior myocardial infarction (MI) and permanent in anterior MI patients. Left anterior fascicular block occurs in 5% of ACS; left posterior fascicular block is observed less frequently (incidence <0.5%). Complete bundle branch block is present in 10% to 15% of ACS patients; right bundle branch block is more common (2/3) than left bundle branch block (1/3). In patients with bradyarrhythmia, intravenous (IV) atropine (1-3 mg) is helpful in 70% to 80% of ACS patients and will lead to an increased heart rate. The need for pacemaker stimulation (PS) is different in patients with inferior MI (IMI) and anterior MI (AMI). Whereas bradyarrhythmias are frequently transient in patients with IMI and therefore do not need permanent PS, there is usually a need for permanent PS in patients with AMI. In these patients bradyarrhythmias are mainly caused by septal necrosis. In patients with ACS and ventricular arrhythmias (VTA) amiodarone is the drug of choice; this drug is highly effective even in patients with defibrillation-resistant out-of-hospital cardiac arrest. There is general agreement that defibrillation and advanced life support is essential and is the treatment of choice for patients with ventricular flutter/fibrillation. If defibrillation is not available in patients with cardiac arrest due to VTA, cardiopulmonary resuscitation is mandatory.
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:29
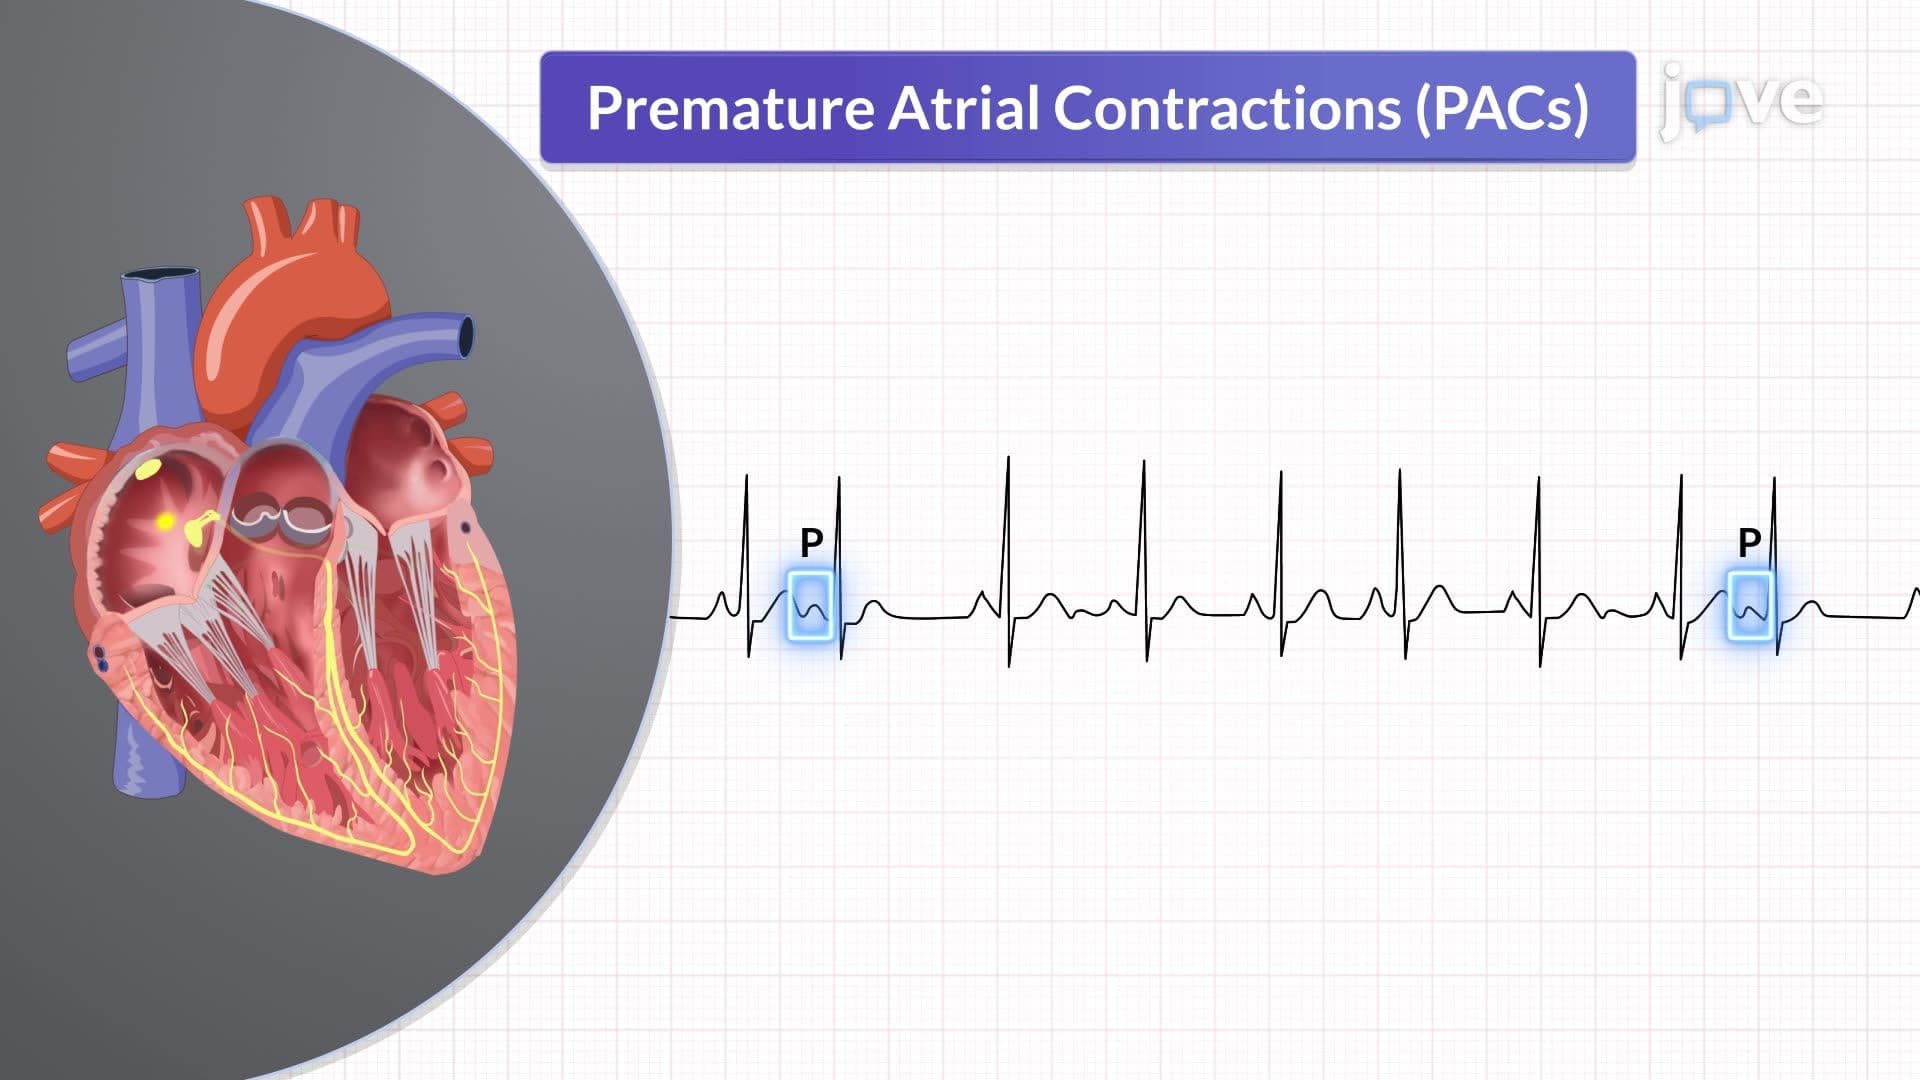
Dysrhythmias III: Characteristics of Dysrhythmias
 01:28
Mechanism of Cardiac Arrhythmias
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism, and...