Case reports of insulinoma and nesidioblastosis in Ethiopia

Moges Kibebew1, Seifu Bacha, Yeweyenharge Feleke

  • 1Department of Internal Medicine, Faculty of Medicine, Addis Ababa University.

Related Concept Videos

Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations
Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Insulin: Biosynthesis, Chemistry, and Preparation01:25

Insulin: Biosynthesis, Chemistry, and Preparation

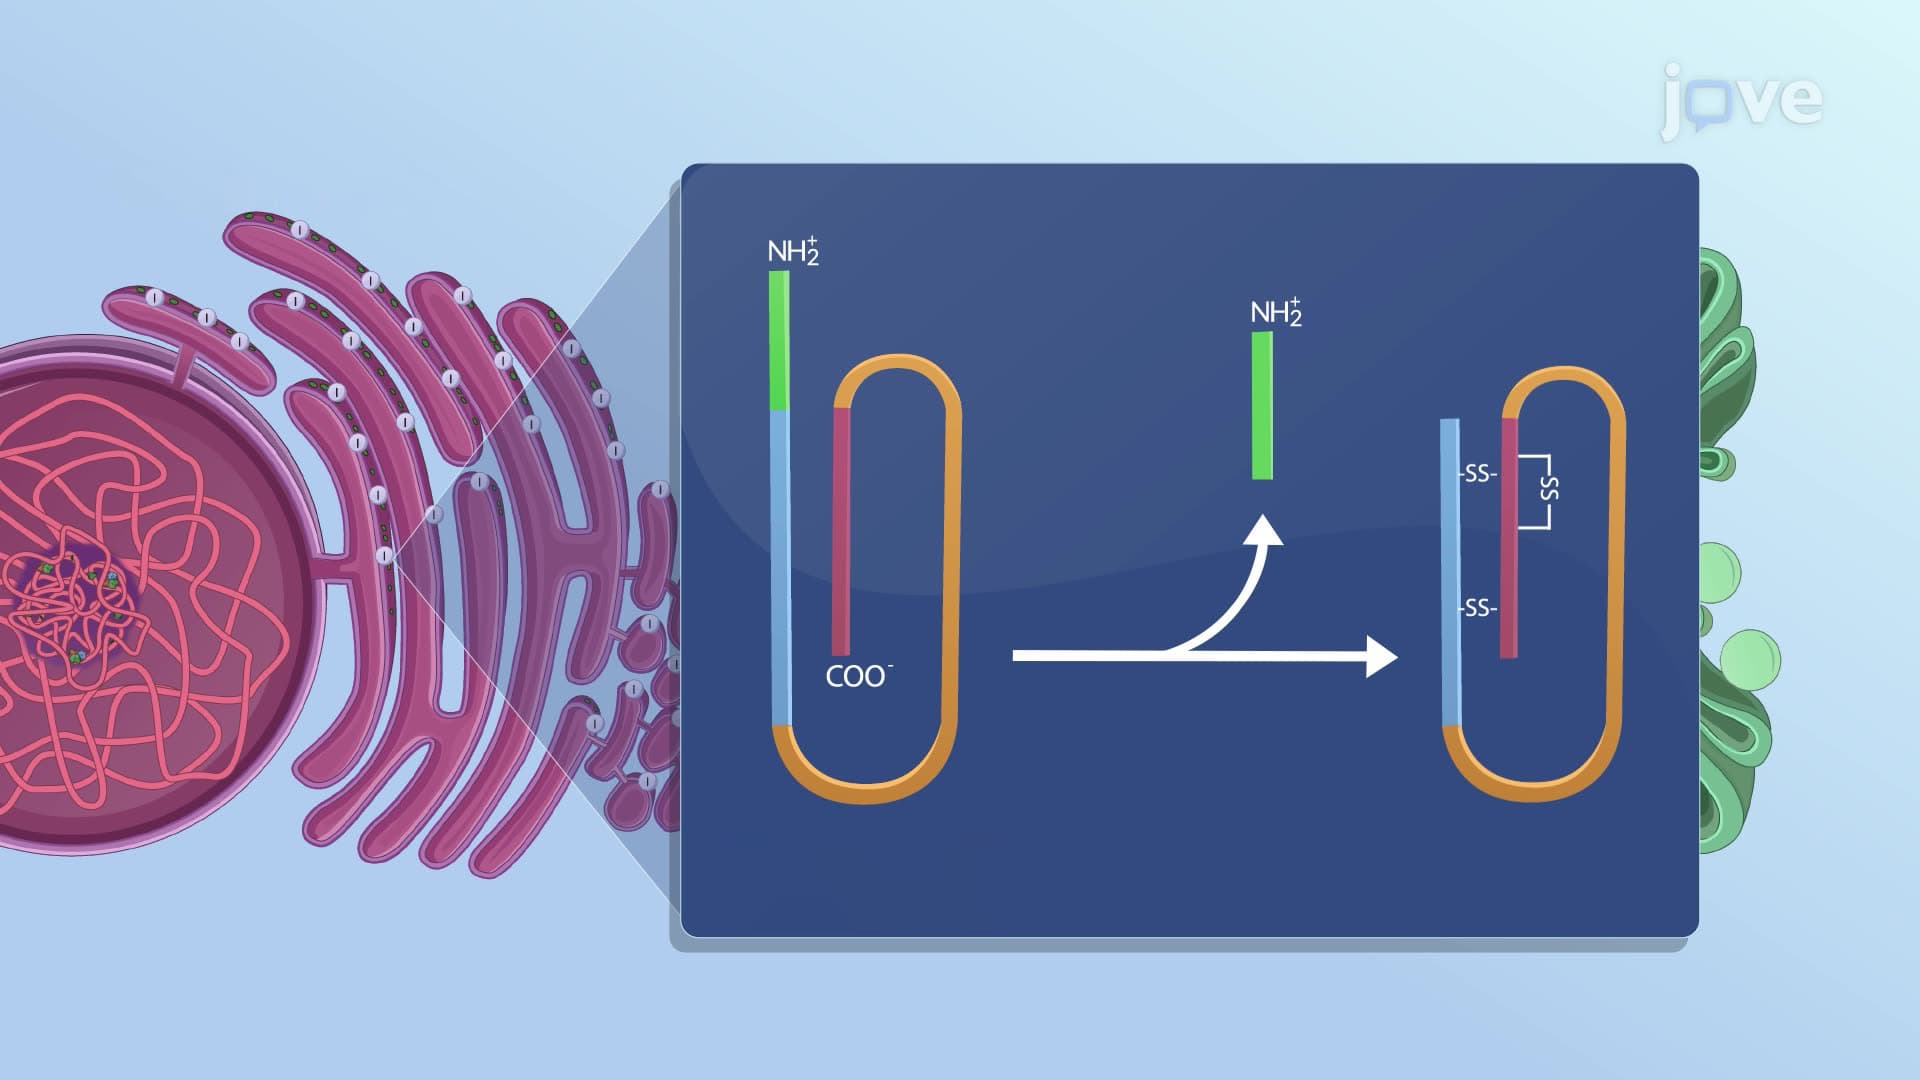
The endoplasmic reticulum (ER) of pancreatic β-cells synthesizes preproinsulin, which consists of a signal peptide, A and B chains, and a C-peptide. Preproinsulin is then cleaved and folded into proinsulin, which translocates to the Golgi apparatus for sorting and packaging into secretory granules. In these granules, enzymatic clipping generates insulin and C-peptide.
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
Insulin Secretory Vesicles01:05

Insulin Secretory Vesicles

Insulin secretory vesicles release insulin to stimulate blood glucose uptake and regulate carbohydrate metabolism. When the blood glucose levels increase, glucose enters the pancreatic β-islet cells through glucose transporters. Once inside, glucose is metabolized through glycolysis, the citric acid cycle, and the electron transport chain, producing ATP. This increase in ATP concentration closes ATP-sensitive potassium channels, leading to depolarization of the membrane and the opening of...
Hypoglycemia and Glucagon01:15

Hypoglycemia and Glucagon

Without prolonged fasting, healthy individuals maintain blood glucose levels above 3.5 mM due to a well-adapted neuroendocrine counterregulatory system that effectively prevents acute hypoglycemia, a potentially life-threatening condition. The primary clinical scenarios for hypoglycemia encompass diabetes treatment, inappropriate production of endogenous insulin or insulin-like substances by tumors, and the use of glucose-lowering agents in non-diabetic individuals. Notably, hypoglycemia in the...
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis01:25

Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis

Type 2 diabetes mellitus develops gradually and is often asymptomatic in early stages.Clinical ManifestationsWhen symptoms appear, they include fatigue, blurred vision, pruritus, delayed wound healing, and recurrent infections, particularly candidal infections. Peripheral neuropathy may present as numbness or tingling in the extremities. Classic hyperglycemia symptoms—polyuria, polydipsia, and polyphagia—are less common. Most patients are overweight and frequently have associated hypertension...
Diabetes Mellitus: Type 2 and Gestational01:22

Diabetes Mellitus: Type 2 and Gestational

Type 2 diabetes, characterized by insulin resistance, arises when the insulin receptors on cells lose responsiveness to insulin, diminishing the cell's capacity to take up glucose, resulting in elevated blood glucose levels. To receive a diagnosis of Type 2 diabetes, a series of blood glucose tests are necessary to assess whether the blood glucose falls within normal parameters. If the result is out of the normal range, a patient may be diagnosed as prediabetic or diabetic, depending on the...