Related Experiment Video
Updated: Jun 11, 2026
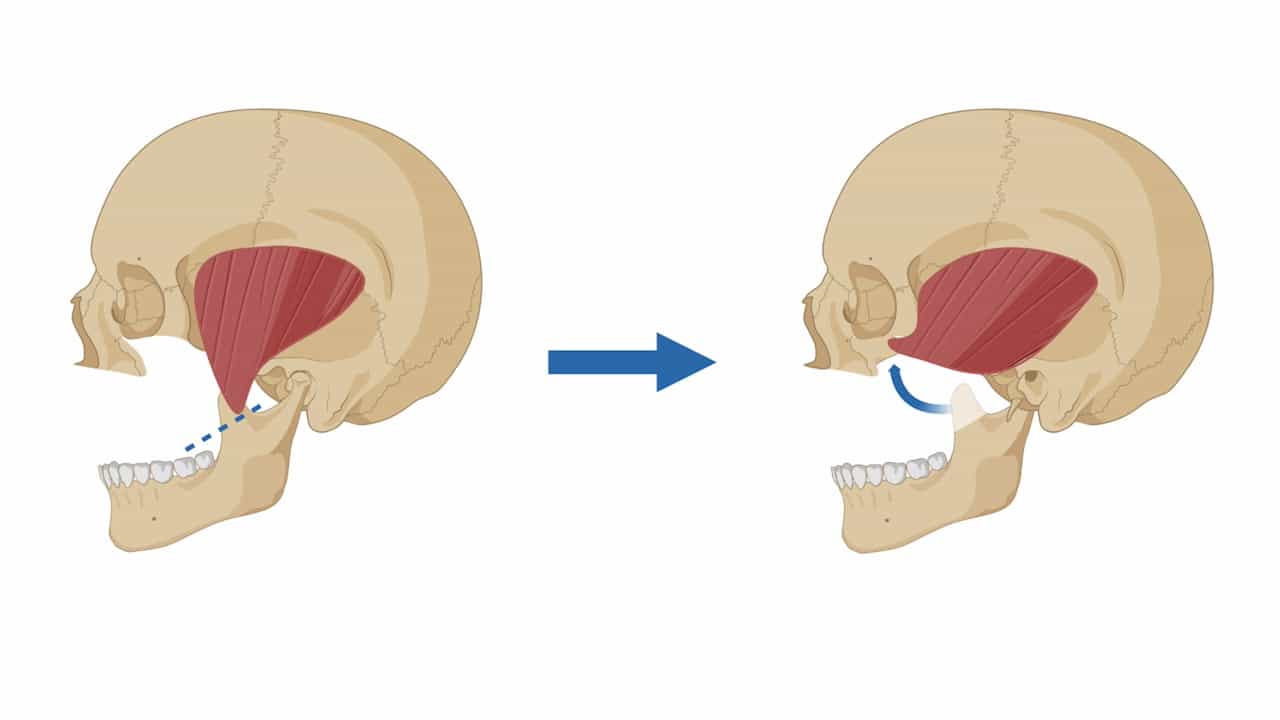

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Facial trauma in Operation Iraqi Freedom casualties: an outcomes study of patients treated from April 2006 through
Nathan L Salinas1, Jeffrey A Faulkner
1Department of Otolaryngology Head and Neck Surgery, Brooke Army Medical Center, Fort Sam Houston, Texas 78234, USA. Nathan.salinas@us.army.mil

Abstract:
This study investigates the postoperative complication rate in American military members treated for fractures of the facial skeleton with either immediate fixation in the Operation Iraqi Freedom combat theater or delayed fixation after transport out of the combat theater. Based on an army head and neck surgeon's case log, retrospective chart review was performed on 21 American active-duty patients evaluated for facial fractures in Balad, Iraq, between April 16, 2006, and October 30, 2006. Follow-up standardized patient interviews and review of electronic medical records were conducted to assess the postoperative clinical course and identify postoperative complications. Facial fractures involved the mandible (62%), the orbit (62%), nasal bones (48%), the midface (38%), the frontal bone (29%), the zygoma (24%), and the temporal bone (5%). Fourteen patients (67%) with facial fractures were treated definitively with open reduction and internal fixation surgery in Balad. Seven patients (33%) had delayed treatment. Overall, the major complication rate was 7% in the immediate fixation group, compared with 57% in the delayed treatment group (P < 0.04). Infectious complications occurred in 1 patient (7%) from the immediate fixation group requiring removal of exposed hardware, whereas 3 patients (43%) from the delayed treatment group experienced infectious complications requiring reoperation (P < 0.09). Although major complications were associated with both immediate and delayed definitive treatment, major complications were more likely to be associated with delayed treatment. The deployed surgeon should use clinical judgment in repairing facial fractures in theater. If treatment is delayed, every effort should be made to affect a timely repair of the fractures.
