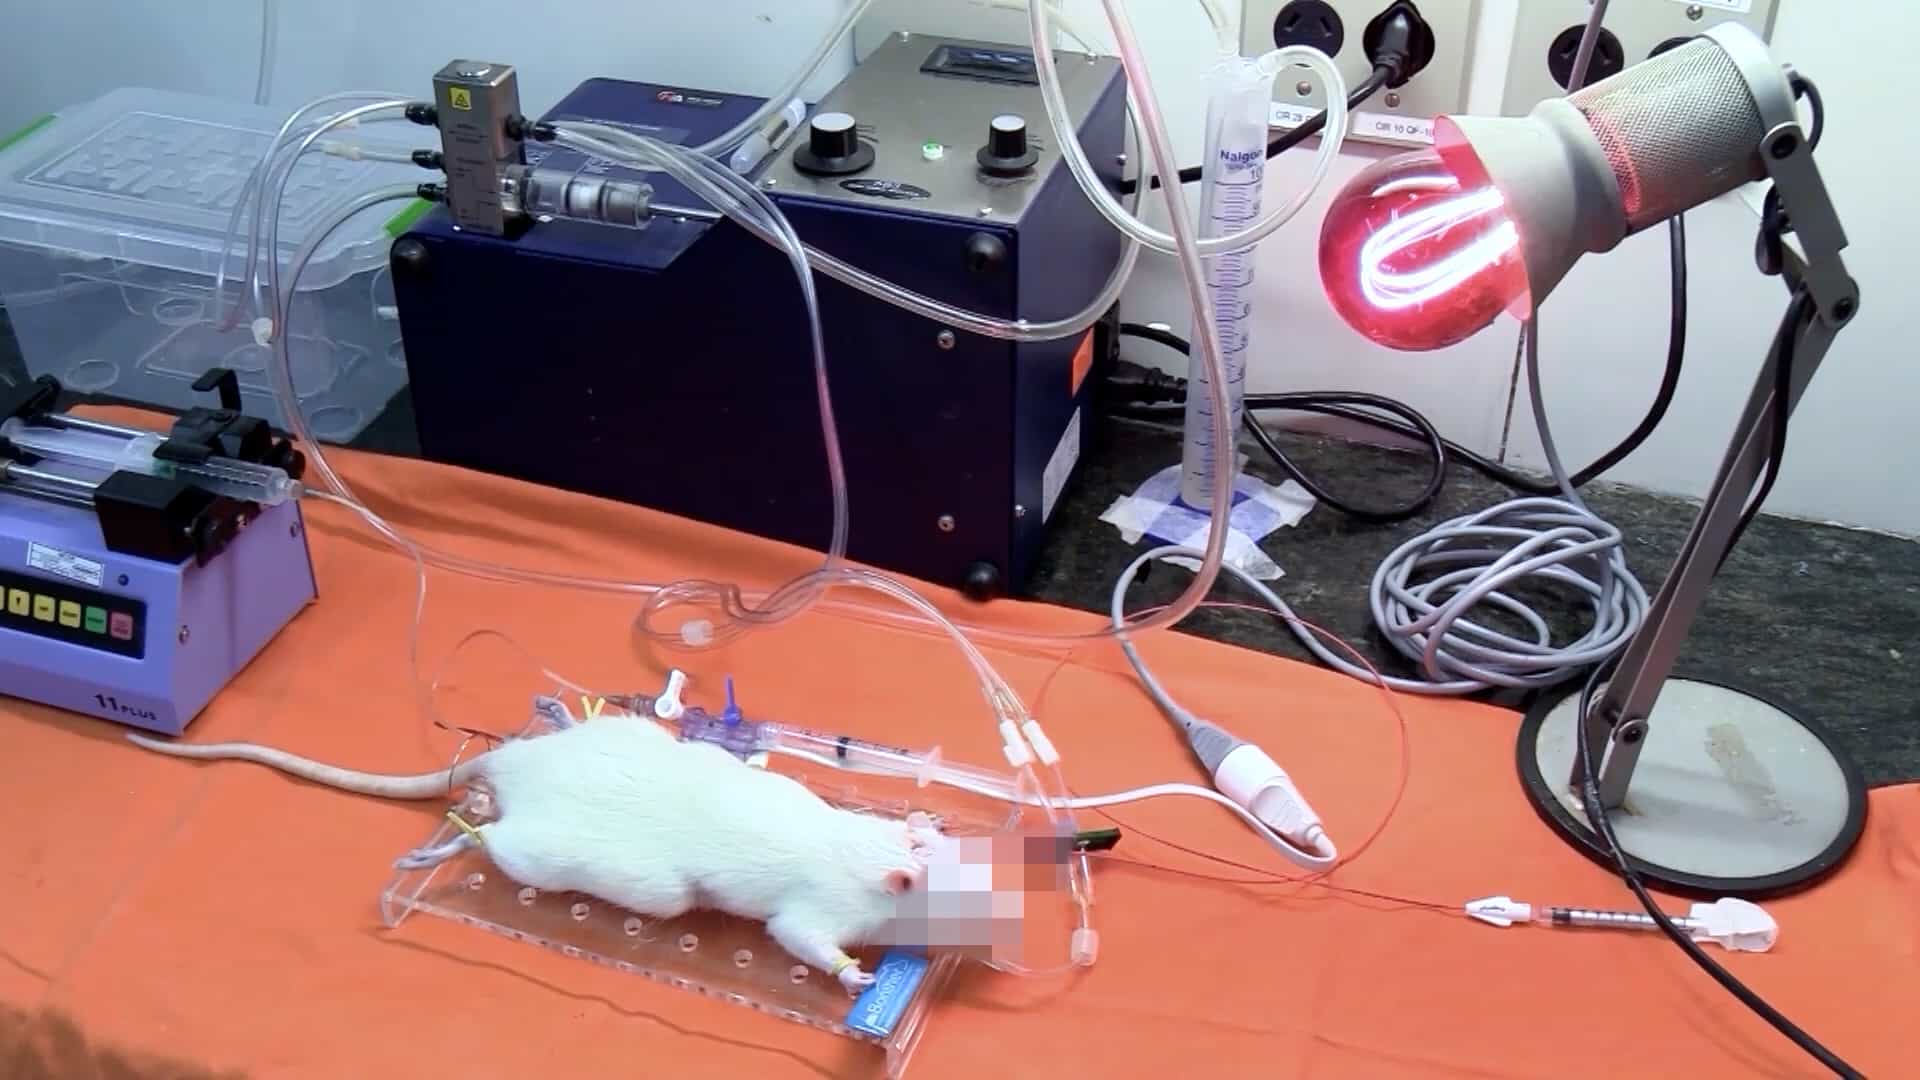
Related Experiment Video
Updated: Jun 11, 2026


Lung Rapid Recovery Procurement Combined with Abdominal Normothermic Regional Perfusion in Controlled Donation after Circulatory Death
Published on: August 15, 2022
Treatment of the brain-dead lung donor with aprotinin and nitric oxide
Vassilios S Avlonitis1, Christopher H Wigfield, John A Kirby
1Applied Immunology and Transplant Research Group, Institute of Cellular Medicine, Medical School, Newcastle University, Newcastle upon Tyne, United Kingdom. avlonitis@hotmail.com

Background:
It has been previously shown that donor treatment with aprotinin or inhaled nitric oxide reduces reperfusion injury after lung transplantation in animals. These studies used living donors with normal lungs. However, the main source of lungs for transplantation is brain-dead donors. Brain death causes systemic inflammatory response and lung injury, rendering the organ susceptible to reperfusion injury after transplantation. We hypothesized that treatment with aprotinin or inhaled nitric oxide after brain death would improve the donor inflammatory response and reduce lung reperfusion injury after transplantation.
Methods:
Brain death was induced in 24 rats by intracranial balloon inflation. Subsequently, the animals received intravenous aprotinin (n = 8), inhaled nitric oxide (n = 7), or no treatment (n = 9) for 5 hours. The lungs were retrieved and reperfused for 2 hours using recipient rats.
Results:
After brain death, oxygenation deteriorated earlier and significantly more in rats that received treatment, especially with nitric oxide. Treatment did not reduce the donor systemic inflammatory response as assessed by serum levels of proinflammatory cytokines. Oxygenation, airway pressure, pulmonary vascular resistance, lung water index and bronchoalveolar lavage cytokine levels were similar after reperfusion of grafts from all three groups of donors.
Conclusions:
Donor treatment with aprotinin or inhaled nitric oxide does not improve lungs that have been injured by brain death.