Related Experiment Videos
Nonadherence to clinical practice guidelines and medications for multiple chronic conditions in a California Medicaid
Michael B Nichol1, Tara K Knight, Julie L Priest
1Department of Clinical Pharmacy and Pharmaceutical Economics and Policy, School of Pharmacy, University of Southern California, Los Angeles, USA. mnichol@usc.edu

Insights
Quality of care for California Medicaid patients with chronic conditions was suboptimal, showing significant nonadherence to medication guidelines. Poorer adherence rates were linked to younger age, Medicaid-only insurance, and Black/other race demographics.
Area of Science:
- Health Services Research
- Public Health
- Chronic Disease Management
Background:
- California Medicaid beneficiaries with chronic conditions experience variable quality of care.
- Assessing adherence to clinical practice guidelines is crucial for evaluating care quality.
Purpose of the Study:
- To assess and profile the quality of care for California Medicaid beneficiaries with chronic conditions.
- To identify factors associated with nonadherence to clinical practice guidelines.
Main Methods:
- Retrospective cohort study utilizing eligibility and claims data from California (2002-2004).
- Included 1,123,577 beneficiaries with dyslipidemia, hypertension, coronary artery disease (CAD), heart failure, or diabetes.
- Quality of care assessed via nonadherence to recommended medications and guideline-based tests; Chi-square analysis used.
Main Results:
- High medication nonadherence observed across conditions, ranging from 41% (diabetes) to 69% (hypertension).
- Significant gaps in recommended testing for diabetes patients, including glycosylated hemoglobin (78%), LDL cholesterol (62%), and eye exams (50%).
- Younger age, Medicaid-only status, and Black/other race were associated with poorer adherence rates.
Conclusions:
- Quality of care for California Medicaid patients with chronic conditions is suboptimal.
- Targeted programs for patients and providers, alongside policy reforms addressing patient characteristics and insurance eligibility, are needed to improve guideline adherence.
Objectives:
To assess and profile quality of care in California Medicaid beneficiaries with chronic conditions.
Design:
Retrospective cohort study.
Setting:
California from 2002 to 2004.
Patients:
1,123,577 beneficiaries.
Intervention:
Eligibility and claims data (2002-2004) were used to identify beneficiaries with dyslipidemia, hypertension, coronary artery disease (CAD), heart failure, or diabetes.
Main Outcome Measures:
Quality of care was based on nonadherence with clinical practice guidelines including recommended medications. Chi-square was used to evaluate nonadherence and patient characteristics.
Results:
The proportion of patients without a prescription fill for recommended medications varied by disease (43% hypertension, 40% dyslipidemia and CAD, and 25% diabetes and heart failure). For Medicaid-only beneficiaries with diabetes, 78% lacked glycosylated hemoglobin tests, 62% lacked low-density lipoprotein cholesterol tests, and 50% lacked eye exams. Medication nonadherence was high (69% hypertension, 64% CAD, 57% heart failure, 48% dyslipidemia, 41% diabetes). Overall, younger age, Medicaid-only status, and black/other race were associated with poorer rates.
Conclusion:
Quality of care was suboptimal, with nonadherence varying by condition. Programs targeting both patients and providers and addressing patient-related characteristics (e.g., age, race) and policy reform addressing alterable factors (e.g., insurance eligibility) should be developed to improve guideline adherence.
Related Concept Videos
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic illness...
 01:15
Drug Dosing: Geriatric Patients
 01:28
Drug Therapy
Antianxiety Medications
 01:30
Guidelines for Nursing Documentation I
Factual:
The following points emphasize the significance of upholding accurate and unbiased documentation in healthcare.
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:24
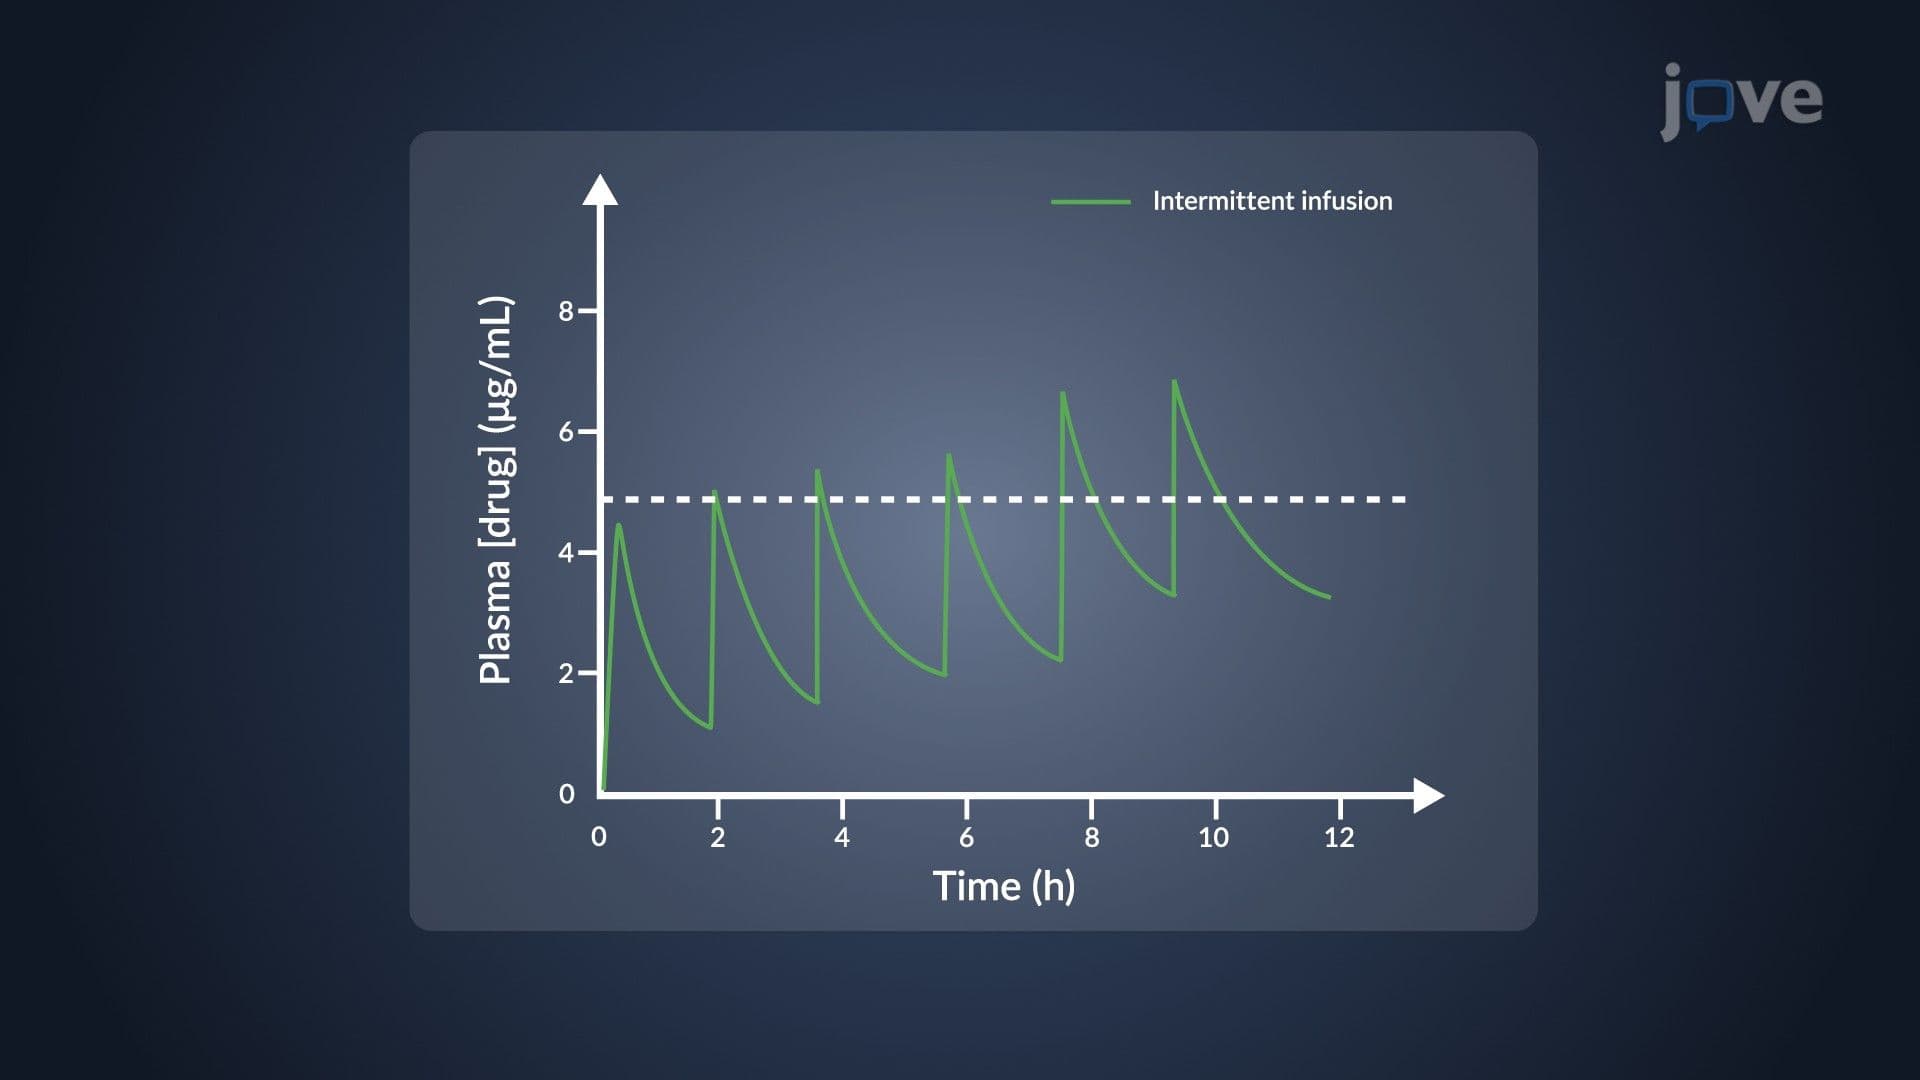
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions