Related Experiment Video
Updated: Jun 11, 2026
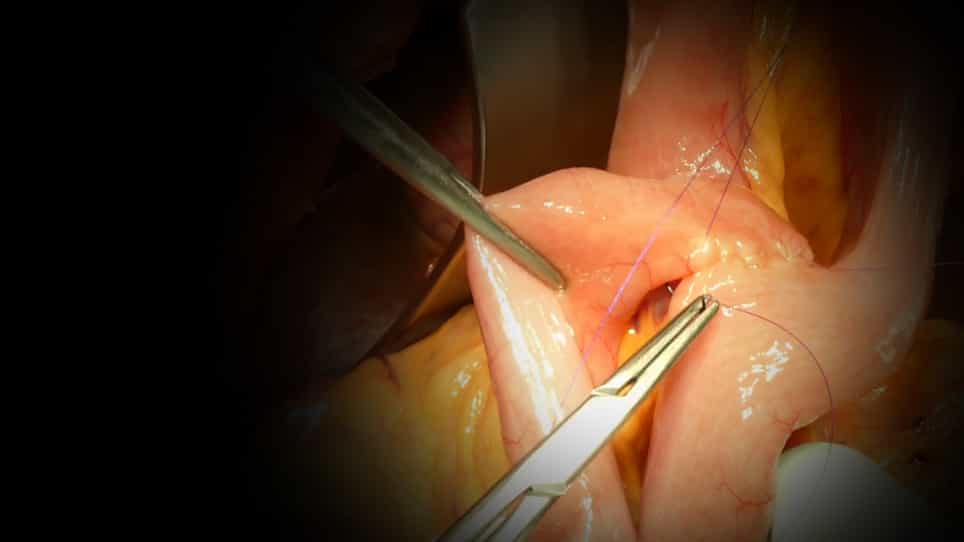
Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Early versus late drain removal after standard pancreatic resections: results of a prospective randomized trial
Claudio Bassi1, Enrico Molinari, Giuseppe Malleo
1Department of Surgery, G.B. Rossi Hospital, University of Verona, Verona, Italy. claudio.bassi@univr.it

Summary Of Background Data:
The role of surgically placed intra-abdominal drainages after pancreatic resections has not been clearly established. In particular, their effect on morbidity rates and the optimal timing for their removal remains controversial.
Methods:
A total of 114 eligible patients who underwent standard pancreatic resections and at low risk of postoperative pancreatic fistula according to our institutional protocol (amylase value in drains < or =5000 U/L on postoperative day [POD] 1) were randomized on POD 3 to receive either early (POD 3) or standard drain removal (POD 5 or beyond). The primary end point of the study was the incidence of pancreatic fistula. Secondary endpoints included abdominal complications, pulmonary complications, in-hospital stay, and perioperative mortality. Cost-analysis between the 2 groups was also made.
Results:
Early drain removal was associated with a decreased rate of pancreatic fistula (P = 0.0001), abdominal complications (P = 0.002), and pulmonary complications (P = 0.007). Median in-hospital stay was shorter (P = 0.018), and hospital costs decreased (P = 0.02). Mortality was nil. A significant association with pancreatic fistula was found for timing of drain removal (P < 0.001), unintentional weight decrease before surgery (P = 0.022), type of pancreas texture (P = 0.015), serum amylase levels on POD 1 (P = 0.001), and albumin levels on POD 1 (P = 0.039). Multivariate analysis showed that timing of drain removal (P = 0.0003) and unintentional weight decrease before surgery (P = 0.02) were independent risk factors of pancreatic fistula.
Conclusions:
In patients at low risk of pancreatic fistula, intra-abdominal drains can be safely removed on POD 3 after standard pancreatic resections. A prolonged period of drain insertion is associated with a higher rate of postoperative complications with increased hospital stay and costs. The manuscript is a randomized trial, registered in the NLM database as NCT00931554.
