Related Experiment Video
Updated: Jun 10, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Effect of parathyroidectomy for primary hyperparathyroidism on bone mineral density in postmenopausal women
A Sitges-Serra1, L García, R Prieto
1Endocrine Surgery Unit, Department of Surgery, Institut Municipal d'Investigació Mèdica, Barcelona, Spain. asitges@imas.imim.es

Background:
The bone mineral density (BMD) response to parathyroidectomy is heterogeneous and difficult to predict. Available data come from mixed populations of men and women, of different age and degrees of disease severity, and preoperative BMD loss.
Methods:
This was a longitudinal, prospective cohort study of 103 postmenopausal women with osteopenia or osteoporosis at the femoral neck site, successfully operated on for primary hyper parathyroidism. BMD and metabolic variables were recorded before and 1 year after parathyroidectomy.
Results:
After surgery, there was a 1.3 per cent increase in the median BMD at the femoral neck site (0.615 versus 0.623 g/cm(2); P = 0.001). Overall, positive responses were also observed at total hip (0.4 per cent) and lumbar spine (2.3 per cent) sites. Analysing the individual responses, however, only 45 (46 per cent) of 97 patients showed a significant (at least 3.7 per cent) increase in BMD at the femoral neck site compared with the preoperative value and 52 had a decreased (15) or unchanged (37) femoral neck BMD. Patients who gained BMD were younger, had more severe hyperparathyroidism and better renal function.
Conclusion:
Almost half of the postmenopausal women with hyperparathyroidism and low BMD have a significant remineralization response 1 year after parathyroidectomy. Differential mineralization responses of BMD after surgery appear to be related to severity of primary hyperparathyroidism, age and renal function.
Related Concept Videos
 01:40
Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 00:59
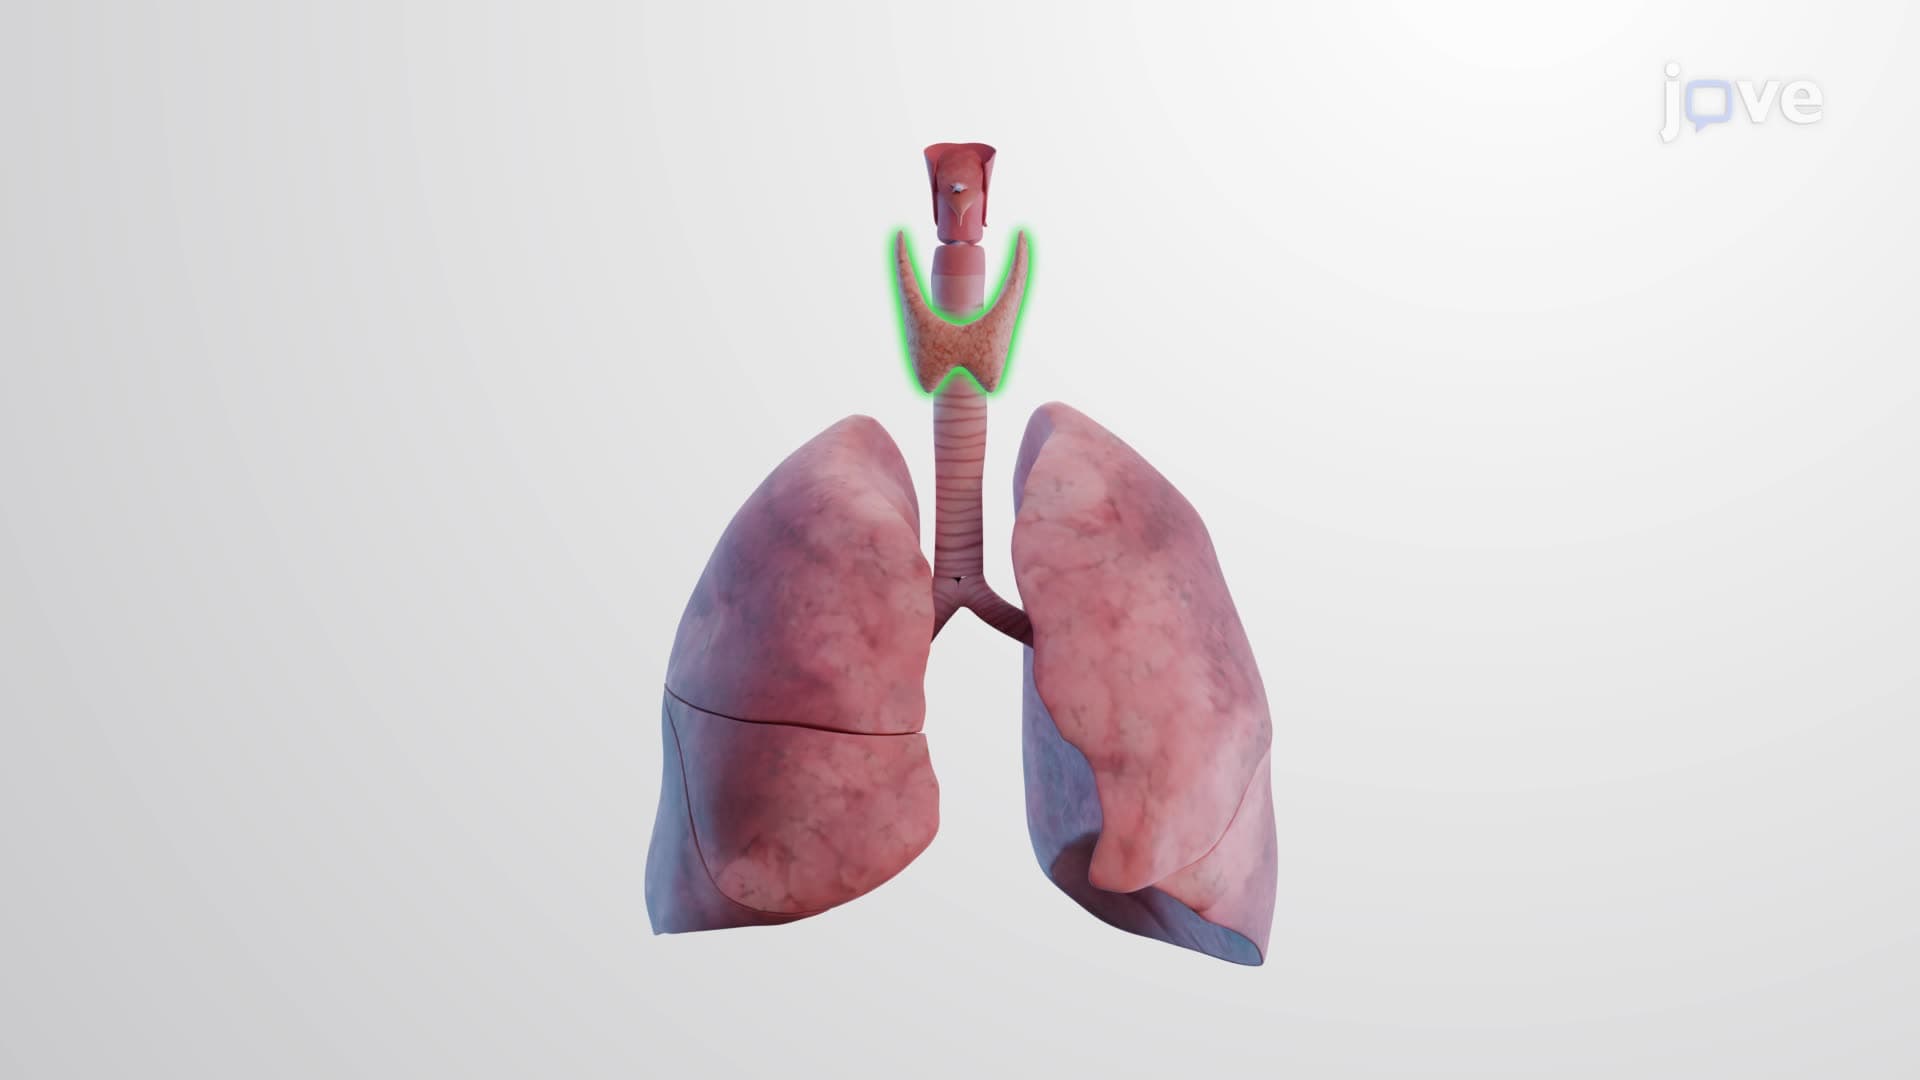
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:21
Skeleton and Calcium Homeostasis
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...