Related Experiment Video
Updated: Jun 10, 2026
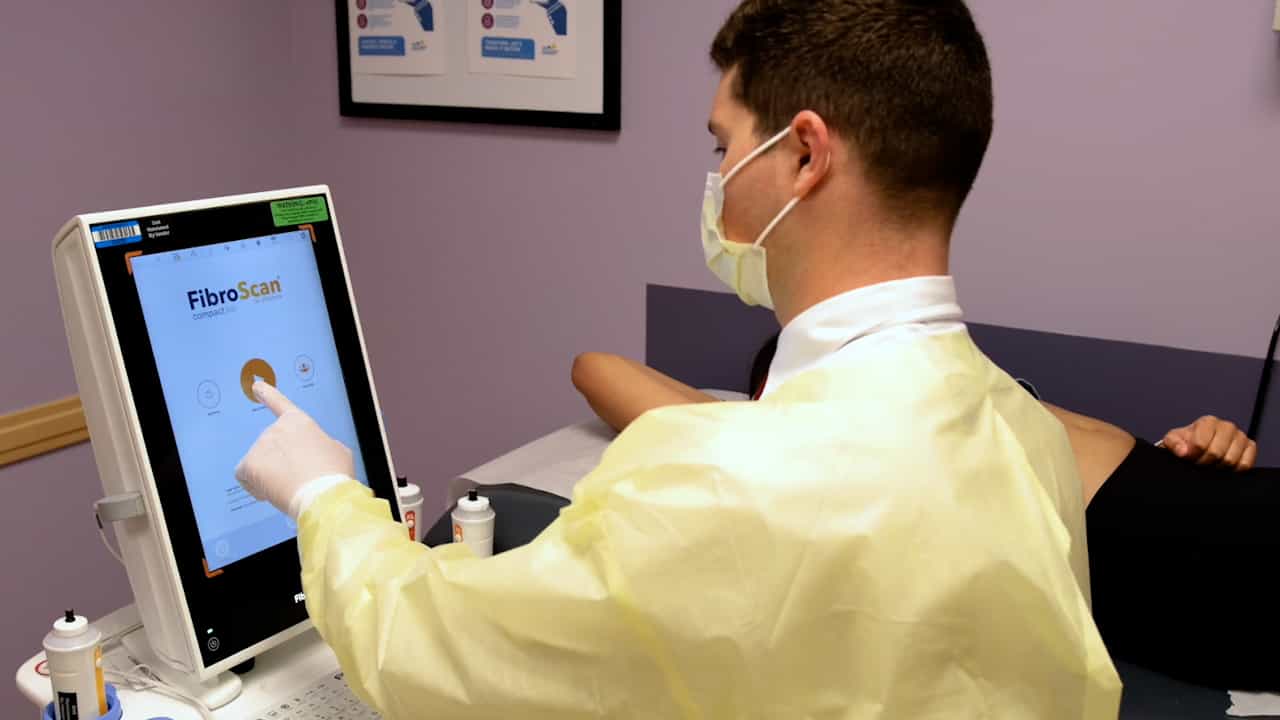

Implementation of Non-invasive Point of Care Transient Elastography for Evaluation of Liver Disease in Pediatric Populations with Cystic Fibrosis
Published on: August 29, 2025
[Over one year follow-up report for newly diagnosed pediatric Crohn's disease]
Xiang Gao1, Zhen-yu Shen, Min-hu Chen
1Department of Gastroenterology, First Affiliated Hospital, Sun Yat-sen University, Guangzhou 510080, China.

Insights
Pediatric Crohn's disease (CD) often presents with growth issues, but immunosuppressant therapy, like 6-MP/AZA, can lead to remission and improved growth. This treatment is safe with careful monitoring.
Area of Science:
- Pediatric Gastroenterology
- Inflammatory Bowel Disease Research
- Clinical Therapeutics
Context:
- Pediatric Crohn's disease (CD) presents unique challenges in diagnosis and management.
- Growth retardation is a significant concern in children diagnosed with CD.
- Understanding clinical characteristics and treatment responses is crucial for improving outcomes.
Purpose:
- To investigate the clinical features, treatment effectiveness, and outcomes of pediatric Crohn's disease (CD).
- To evaluate the impact of immunosuppressant therapy on disease activity and growth in pediatric CD patients.
- To assess the safety and efficacy of individualized treatment strategies.
Summary:
- A cohort of 20 pediatric CD patients (0.5-15 years) showed common symptoms including abdominal pain, fever, and diarrhea, with 50% experiencing growth retardation and 45% presenting with complicated disease behavior.
- Treatment with corticosteroids and 6-mercaptopurine/azathioprine (6-MP/AZA) led to complete remission in 82% of cases, with 40% achieving mucosal healing.
- At follow-up (mean 23 months), 75% achieved complete remission, and those who withdrew from corticosteroids showed catch-up growth, with 17% experiencing severe adverse effects from 6-MP/AZA.
Impact:
- Immunosuppressant therapy, particularly 6-MP/AZA, demonstrates potential to alter the natural history of pediatric CD.
- Early identification of growth retardation can serve as a diagnostic indicator for pediatric CD.
- Individualized treatment under close monitoring appears safe and effective for managing pediatric CD.
Objective:
To explore the clinical characteristics, therapeutic responses and outcomes of pediatric Crohn's disease (CD).
Methods:
From a hospital-derived incidence cohort, 20 Crohn's disease patients (aged 0.5 - 15 years old at diagnosis), diagnosed from 2003 to 2009, received a follow-up period of more than one year. The patients were phenotyped according to Montreal standards. PCDAI was introduced to assess the disease activity and the Hyams J rules adopted to evaluate the therapeutic efficacies. The treatment was individualized based on the overall evaluation of child.
Results:
Of these 20 patients, 55% were 7 - 12 years old at the diagnosis time. The male: female ratio was 1.5:1. At the time of diagnosis, the common manifestations included abdominal pain (95.0%), fever (80.0%) and diarrhea (80.0%). Growth retardation was detected in 50% of the cases. Complicated behavior was observed in 45% patients at diagnosis. The most frequent disease location at diagnosis was terminal ileum/colon (55%). Upper GI tract involvement was quite common in children (20%). Non-penetrating non-stricture (50%) behavior was most frequent at diagnosis. Ultimately, corticosteroids plus 6-MP/AZA treatment was administrated in 11 cases. Of these, 9 (82%) successfully withdrew the corticosteroids and maintained a complete remission. Colonoscopy was repeated in 6 complete remission cases and 4 of them achieved a complete mucosa healing. The mean follow-up period was 23 months (range: 12 - 59). At the endpoint of follow-up, 15 cases achieved a complete remission, 4 had a partial remission, 1 underwent operation and none of them died. The children who successfully withdrew from corticosteroids and achieved a complete remission could catch up the height of their age group. 6-MP/AZA associated severe adverse effects were reported at 17% in this group.
Conclusion:
Growth retardation is predominant in pediatric CD and it may provide diagnostic clues. Immunosuppressant therapy may improve the natural history of this disease. It is safe under close monitoring.
Related Concept Videos
 01:25
Inflammatory Bowel Disease III: Crohn's Disease
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:21
Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: