Optimizing blood pressure control in patients with chronic kidney disease
Related Experiment Video
Updated: Jun 10, 2026
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Biff F Palmer1, Andrew Z Fenves
1Department of Medicine, Division of Nephrology, University of Texas Southwestern Medical School, Dallas, Texas (Palmer); and Division of Nephrology, Department of Internal Medicine, Baylor University Medical Center at Dallas, Dallas, Texas (Fenves).

Insights
Strictly controlling hypertension in chronic kidney disease (CKD) patients to below 130/80 mm Hg is crucial. Fixed-dose combination therapy, particularly with a renin-angiotensin-aldosterone system (RAAS) inhibitor, effectively lowers blood pressure and improves adherence.
Area of Science:
- Nephrology
- Cardiology
- Pharmacology
Background:
- Hypertension is prevalent in chronic kidney disease (CKD) patients and accelerates kidney and cardiovascular disease progression.
- Stringent blood pressure control (<130/80 mm Hg) is essential for managing CKD and reducing cardiovascular risks.
- Renin-angiotensin-aldosterone system (RAAS) inhibitors are a cornerstone of antihypertensive therapy in CKD.
Purpose of the Study:
- To evaluate the efficacy of fixed-dose combination antihypertensive therapy in CKD patients.
- To compare fixed-dose combination therapy with stepped-care or sequential monotherapy.
- To explore optimal RAAS inhibitor-based combination strategies for cardiovascular risk reduction in high-risk CKD patients.
Main Methods:
- Analysis of clinical data comparing different antihypertensive treatment strategies.
- Focus on fixed-dose combinations involving RAAS inhibitors.
- Evaluation of patient adherence and achievement of target blood pressure levels.
Main Results:
- Fixed-dose RAAS inhibitor-based combinations significantly increase the likelihood of reaching target blood pressure levels compared to other strategies.
- Fixed-dose combinations can improve patient adherence by reducing pill burden and clinic visits.
- Emerging data suggest RAAS inhibitor plus dihydropyridine calcium channel blocker combinations may offer superior cardiovascular benefits over RAAS inhibitor plus diuretic combinations in high-risk patients.
Conclusions:
- Fixed-dose combination therapy, especially with RAAS inhibitors, is an effective strategy for hypertension management in CKD.
- This approach enhances treatment adherence and facilitates blood pressure control.
- Further research supports specific combination therapies, like RAAS inhibitor and dihydropyridine calcium channel blocker, for improved cardiovascular outcomes in high-risk CKD populations.
Abstract:
The majority of patients with chronic kidney disease have hypertension, which is an independent risk factor for progression of kidney disease and cardiovascular disease. Therefore, hypertension should be stringently controlled to a blood pressure level of <130/80 mm Hg. Achieving this goal, which usually requires two or more antihypertensive agents, slows the progression of kidney disease and reduces the risk of cardiovascular disease. All antihypertensive treatments for patients with chronic kidney disease should include a renin-angiotensin-aldosterone system (RAAS) inhibitor (an angiotensin-converting enzyme inhibitor or an angiotensin receptor blocker). Initial therapy with fixed-dose RAAS inhibitor-based combinations should be considered, because this approach has been shown to bring significantly more patients to target blood pressure levels, compared with stepped-care treatment or sequential monotherapy. Fixed-dose combination therapy may also improve patient adherence to treatment by reducing the number of pills taken daily and the number of office visits for dosage adjustments. Recent clinical data suggest that the combination of a RAAS inhibitor and a dihydropyridine calcium channel blocker may provide more cardiovascular benefit than the generally recommended combination of a RAAS inhibitor and a diuretic in patients at high risk for cardiovascular events.
Related Concept Videos
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:30
Blood Pressure
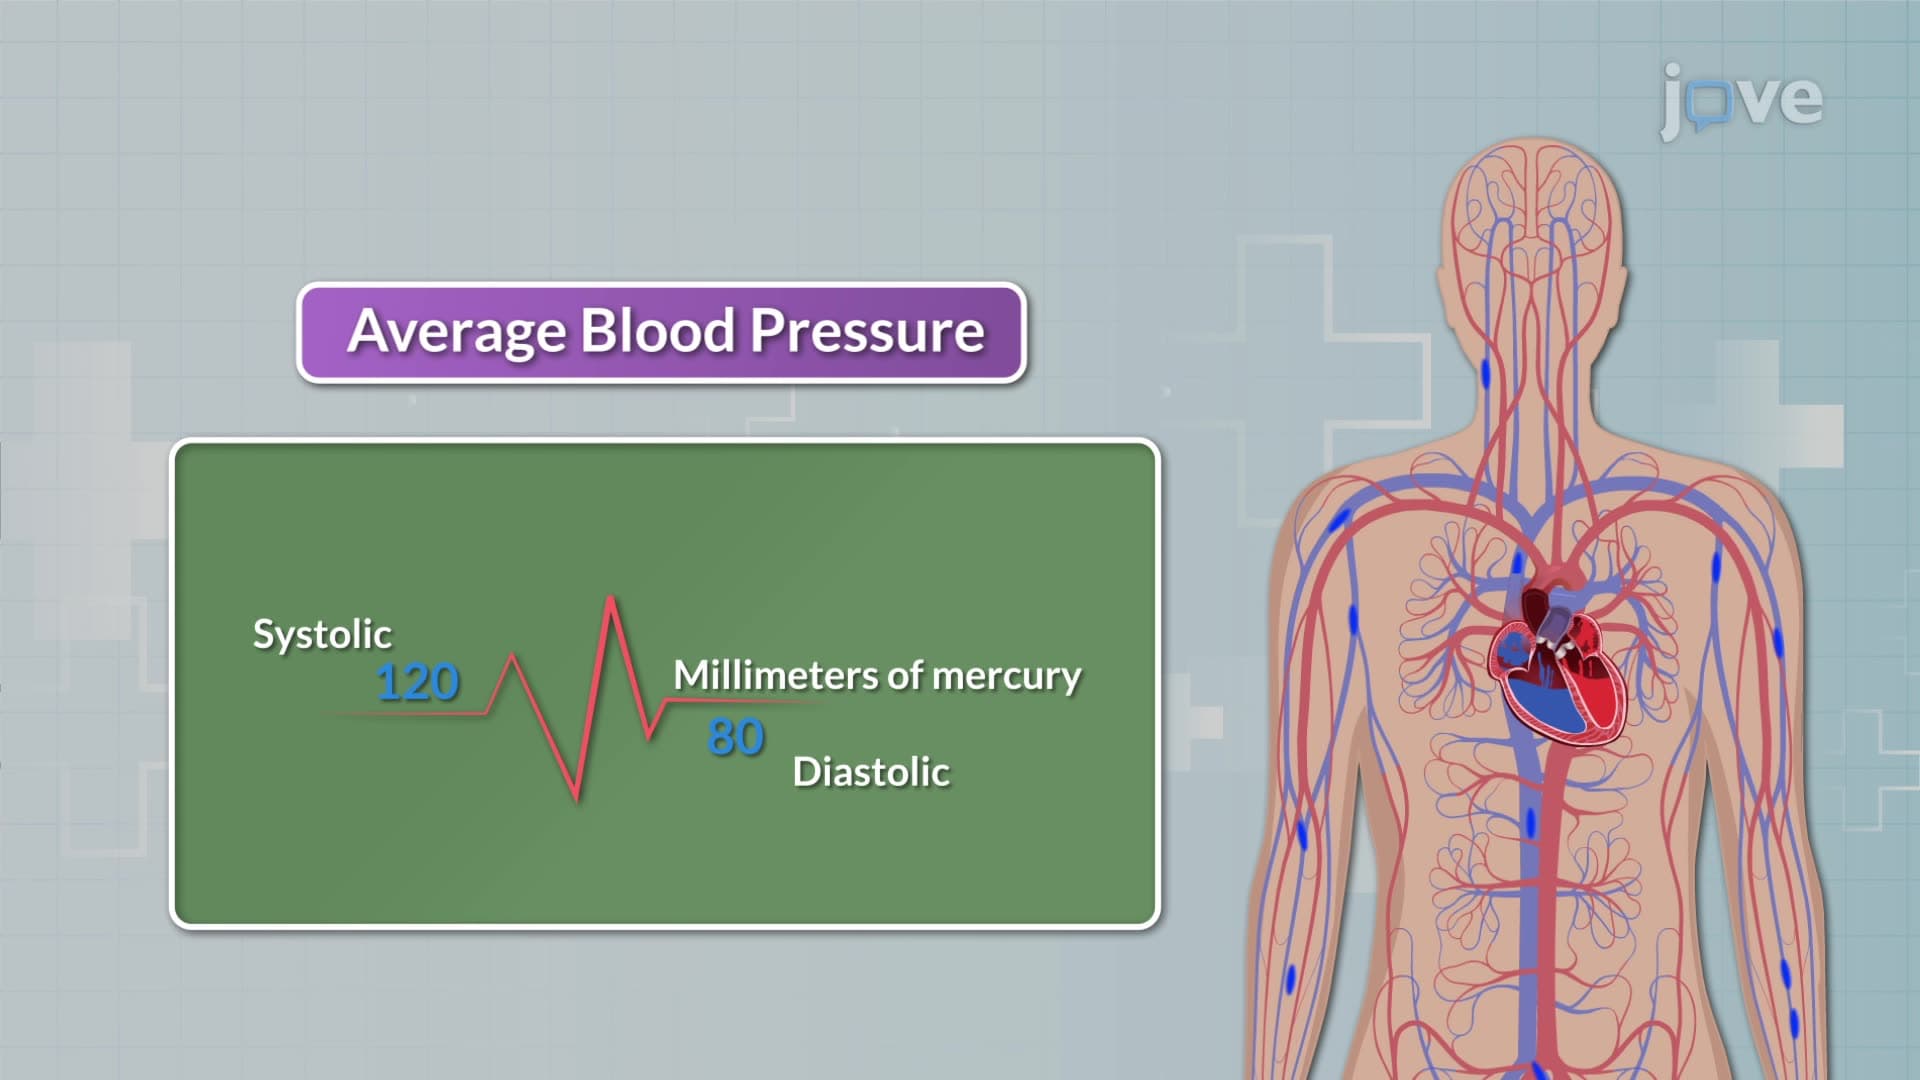
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:22
Acute Kidney Injury VI: Nursing Management
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications