Related Experiment Video
Updated: May 5, 2026
Mechanical Ventilation Boot Camp Curriculum
Published on: March 12, 2018
One-year trajectories of care and resource utilization for recipients of prolonged mechanical ventilation: a cohort
Mark Unroe1, Jeremy M Kahn, Shannon S Carson
1Duke University, Durham, North Carolina 27710, USA.

Background:
Growing numbers of critically ill patients receive prolonged mechanical ventilation. Little is known about the patterns of care as patients transition from acute care hospitals to postacute care facilities or about the associated resource utilization.
Objective:
To describe 1-year trajectories of care and resource utilization for patients receiving prolonged mechanical ventilation.
Design:
1-year prospective cohort study.
Setting:
5 intensive care units at Duke University Medical Center, Durham, North Carolina.
Participants:
126 patients receiving prolonged mechanical ventilation (defined as ventilation for >or=4 days with tracheostomy placement or ventilation for >or=21 days without tracheostomy), as well as their 126 surrogates and 54 intensive care unit physicians, enrolled consecutively over 1 year.
Measurements:
Patients and surrogates were interviewed in the hospital, as well as 3 and 12 months after discharge, to determine patient survival, functional status, and facility type and duration of postdischarge care. Physicians were interviewed in the hospital to elicit prognoses. Institutional billing records were used to assign costs for acute care, outpatient care, and interfacility transportation. Medicare claims data were used to assign costs for postacute care.
Results:
103 (82%) hospital survivors had 457 separate transitions in postdischarge care location (median, 4 transitions [interquartile range, 3 to 5 transitions]), including 68 patients (67%) who were readmitted at least once. Patients spent an average of 74% (95% CI, 68% to 80%) of all days alive in a hospital or postacute care facility or receiving home health care. At 1 year, 11 patients (9%) had a good outcome (alive with no functional dependency), 33 (26%) had a fair outcome (alive with moderate dependency), and 82 (65%) had a poor outcome (either alive with complete functional dependency [4 patients; 21%] or dead [56 patients; 44%]). Patients with poor outcomes were older, had more comorbid conditions, and were more frequently discharged to a postacute care facility than patients with either fair or good outcomes (P < 0.05 for all). The mean cost per patient was $306,135 (SD, $285,467), and total cohort cost was $38.1 million, for an estimated $3.5 million per independently functioning survivor at 1 year.
Limitation:
The results of this single-center study may not be applicable to other centers.
Conclusion:
Patients receiving prolonged mechanical ventilation have multiple transitions of care, resulting in substantial health care costs and persistent, profound disability. The optimism of surrogate decision makers should be balanced by discussions of these outcomes when considering a course of prolonged life support.
Primary Funding Source:
None.

Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:14
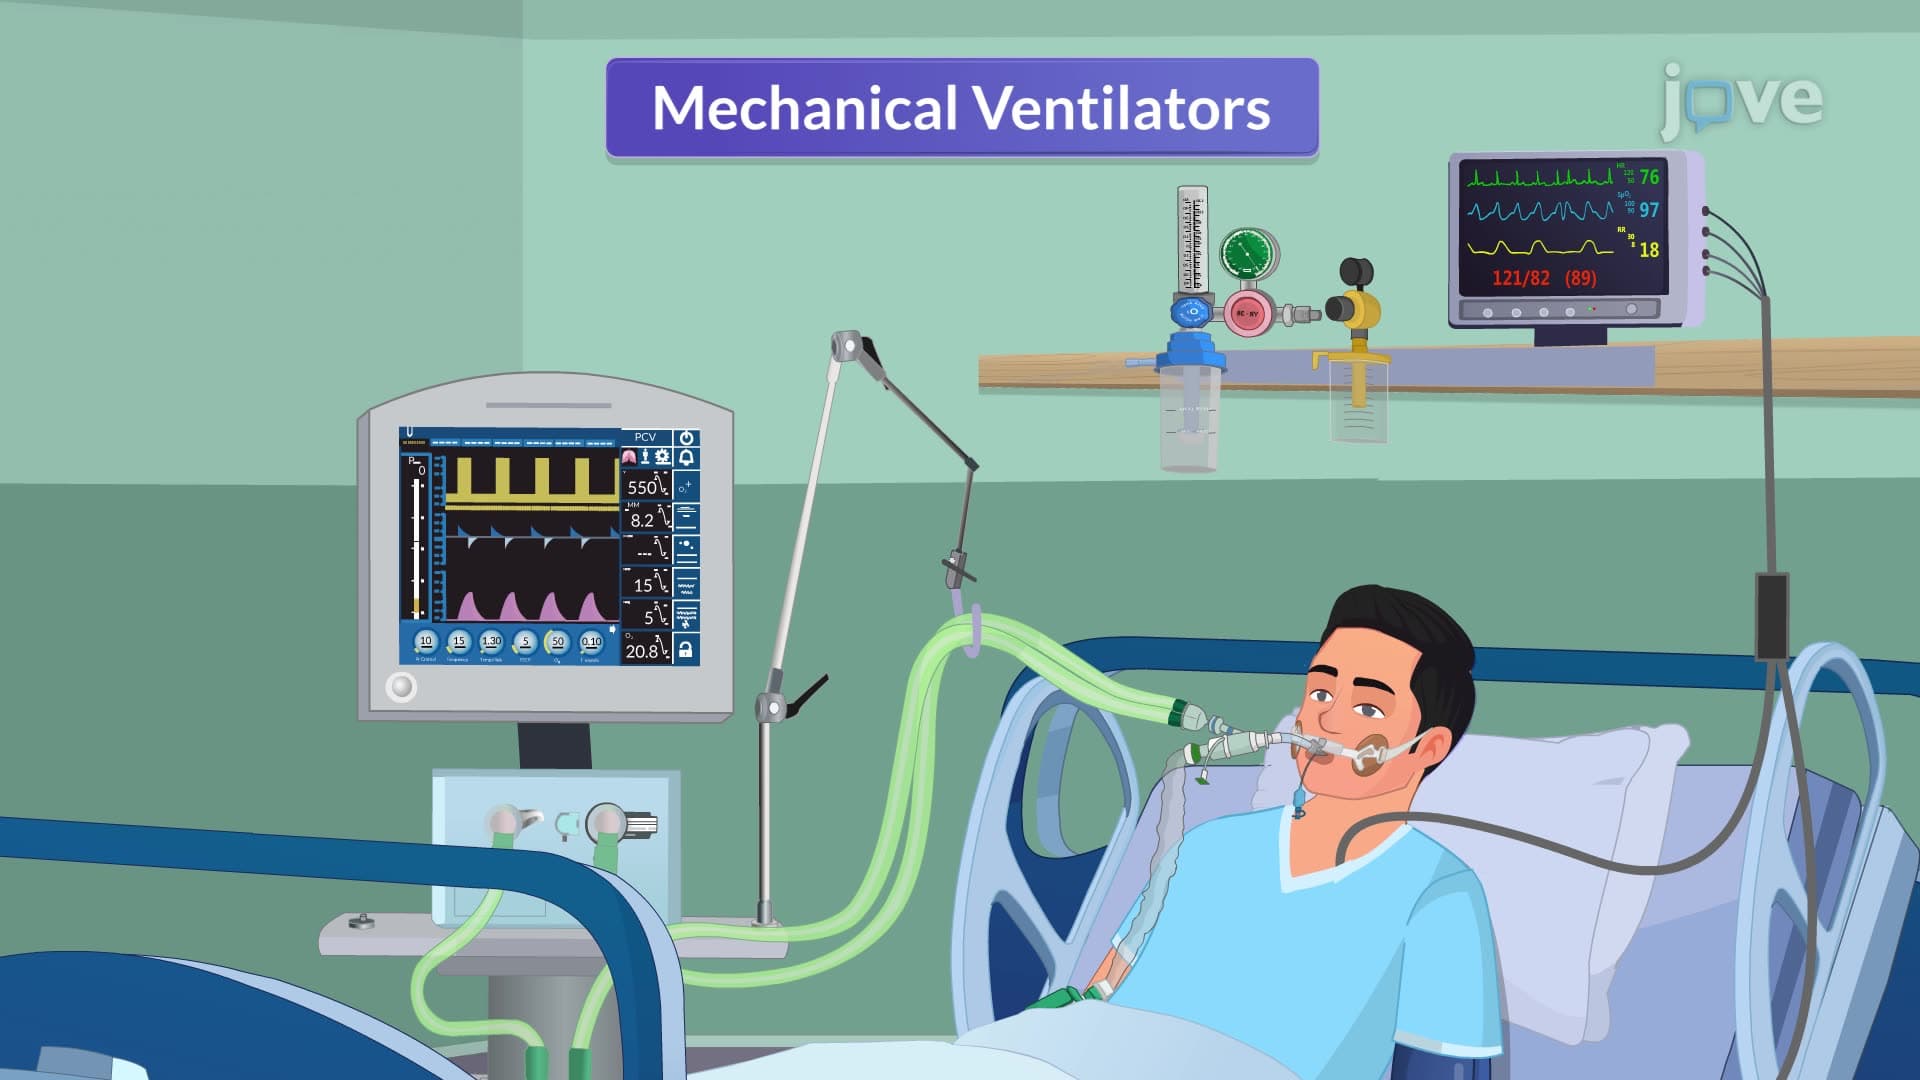
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...